



 PDF
 ePub
 Citation
 Print


Abstract
A 35-year-old woman visited the emergency department for a pedestrian traffic accident. Severe tenderness was noted at the posterior sacrum area, without open wound or initial neurologic deficit. Fracture of the left sacral ala extended to the S1 foramen, anterior acetabulum, and pubic ramus. Two weeks after the injury, she presented aggravating radiculopathy with the weakness of the left great toe plantar flexion. The S1 nerve root was compressed by the fracture fragments in the left S1 foramen. Decompressive S1 foraminotomy was performed. The postoperative follow-up computed tomography scan showed successful decompression of the encroachment, and the patient recovered well from the radiculopathy with motor weakness. She was able to resume her daily routine activity. We suggest that early decompressive sacral foraminotomy could be a useful additional procedure in selective sacral zone II fractures that are accompanied by radiculopathy with a motor deficit.
Figures and Tables
Fig. 1
This schematic drawing of the sacrum shows a classification of sacral fractures according to Denis et al.1) 1: Zone I-ala region; 2: Zone II-foramina region; 3: Zone III-central sacral canal region.
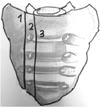
Fig. 2
A, B) Anteroposterior pelvic radiograph and 3-dimensional computed tomography (CT) shows a fracture at the left sacral ala, sacral foramina (white arrows) anterior acetabulum, and pubic ramus. Coronal (C), and axial (D) view of the CT image show S1 left foraminal encroachment by the fracture fragment (arrows).

Fig. 3
(A, B) T2-weighted axial images show an enlarged S1 nerve root with increased signal intensity, suggesting nerve root injury (arrow heads and arrow).
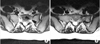
Fig. 4
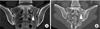
(A-C) Decompressive S1 foraminotomy was performed. The S1 foramen was explored under an image intensifier with a penfield probe. We used a Kerrison punch (2 mm, 3 mm) in the foraminotomy, under a loupe magnification. The foraminal encroachment and nerve root release were identified with a nerve hook probe.

References
1. Denis F, Davis S, Comfort T. Sacral fractures: an important problem Retrospective analysis of 236 cases. Clin Orthop Relat Res. 1988; 227:67–81.
2. Young JW, Burgess AR, Brumback RJ, Poka A. Lateral compression fractures of the pelvis: the importance of plain radiographs in the diagnosis and surgical management. Skeletal Radiol. 1986; 15:103–109.

3. Kim MY, Reidy DP, Nolan PC, Finkelstein JA. Transverse sacral fractures: case series and literature review. Can J Surg. 2001; 44:359–363.
4. Hersche O, Isler B, Aebi M. Follow-up and prognosis of neurologic sequelae of pelvic ring fractures with involvement of the sacrum and/or the iliosacral joint. Unfallchirurg. 1993; 96:311–318.
5. Roy-Camille R, Saillant G, Gagna G, Mazel C. Transverse fracture of the upper sacrum. Suicidal jumpers fracture. Spine (Phila Pa 1976). 1985; 10:838–845.
6. Schnaid E, Eisenstein SM, Drummond-Webb J. Delayed posttraumatic cauda equina compression syndrome. J Trauma. 1985; 25:1099–1101.
7. Schmidek HH, Smith DA, Kristiansen TK. Sacral fractures. Neurosurgery. 1984; 15:735–746.
8. Fountain SS, Hamilton RD, Jameson RM. Transverse fractures of the sacrum A report of six cases. J Bone Joint Surg Am. 1977; 59:486–489.
9. Phelan ST, Jones DA, Bishay M. Conservative management of transverse fractures of the sacrum with neurological features A report of four cases. J Bone Joint Surg Br. 1991; 73:969–971.
10. Zelle BA, Gruen GS, Hunt T, Speth SR. Sacral fractures with neurological injury: is early decompression beneficial? Int Orthop. 2004; 28:244–251.
 XML Download