

Journal List > Blood Res > v.61 > 1516096205

Lee, Lee, Kim, Huh, Lee, Oh, Kim, and Lee: Infectious complications after CAR T‑cell therapy: mechanisms, risk stratification, and prevention

Abstract

Chimeric antigen receptor (CAR) T-cell therapy is an established treatment for relapsed or refractory B-cell malignancies. Despite therapeutic success, infectious complications remain a major contributor to non-relapsed morbidity and mortality. The risk of infection reflects a prolonged and multifactorial state of immunosuppression resulting from lymphodepleting chemotherapy, treatment-related cytopenia, sustained CD4+ T-cell lymphopenia, B-cell aplasia with hypogammaglobulinemia, and the use of corticosteroids or cytokine-directed therapies for the management of immune effector cell-associated toxicities (i.e., cytokine-release syndrome and immune effector cell–associated neurotoxicity). The spectrum of infections has evolved over time. Bacterial infections are observed most frequently in the early post-infusion period, whereas viral and opportunistic infections become more prominent later, particularly in patients with delayed immune recovery. Infection risk is also influenced by the underlying malignancy, prior exposure to treatment, and the type of CAR T-cell product used. For example, BCMA-directed CAR T-cell therapy has been associated with a higher infection burden, likely related to profound plasma cell depletion and sustained impairment of humoral immunity. Preventing infections in this setting requires a structured and individualized approach. Common strategies include antiviral and Pneumocystis jirovecii pneumonia prophylaxis, the selective use of antibacterial and antifungal prophylaxis during periods of severe or prolonged cytopenia, immunoglobulin replacement in patients with clinically significant hypogammaglobulinemia, and vaccination schedules guided by immune recovery. Therefore, coordinated and risk-adapted prevention is essential to minimize infectious complications and to improve long-term outcomes after CAR-T cell therapy. This review summarizes the current evidence and major recommendations of international guidelines to provide an updated overview of infection mechanisms, risk stratification, and preventive strategies for patients receiving CAR T-cell therapy.

Introduction: CAR T‑cell therapy and emerging infectious challenges

Chimeric antigen receptor (CAR) T-cell therapy has transformed the treatment landscape of hematological malignancies and is now widely used for several high-risk and relapsed diseases. It was first approved for patients with relapsed or refractory large B-cell lymphoma (LBCL) and B-cell acute lymphoblastic leukemia (B-ALL) and has since been expanded to include multiple myeloma (MM). In heavily pretreated patients, CAR T-cell therapy has substantially improved response and survival rates [17]. As indications continue to expand and eligibility criteria are broadened to include older and more comorbid patients, the global use of CAR T-cell therapy continues to grow [810].
With improved survival, non-relapse mortality (NRM) has emerged as a critical outcome [11, 12]. Although early attention was focused on disease control and acute toxicities, such as cytokine release syndrome (CRS) and immune effector cell–associated neurotoxicity syndrome (ICANS), longer follow-up has clarified that infections are a major contributor to NRM [1113]. A recent metaanalysis reported that infections accounted for approximately half of non-relapse deaths after CAR T-cell therapy, exceeding mortality attributable to CRS, ICANS, and immune effector cell–associated hemophagocytic syndrome (IEC-HS) [11]. Treatment-related mortality in clinical trials generally ranges from 0 to 6%, whereas real-world NRM rates may reach 5% to 10%, highlighting infection as a key determinant of outcomes after CAR T-cell therapy [3, 11, 12]. Importantly, infectious complications occur across distinct temporal phases that reflect evolving immune dysfunction resulting from lymphodepletion, CAR T-cell activity, and immunosuppressive therapies [3, 14, 15].
This review provides an overview of infectious complications following CAR T-cell therapy, focusing on temporal risk patterns, underlying mechanisms, and evidence-based strategies for screening, antimicrobial prophylaxis, viral monitoring, immunoglobulin replacement, and vaccination [16, 17].

Burden of infection after CAR T‑cell therapy: incidence, timing and clinical impact

Infectious complications are common after CAR T-cell therapy and remain important contributors to morbidity and NRM. Across trials and real-world cohorts, reported infection rates range from approximately 15% to 50%, reflecting differences in patient populations, CAR T-cell constructs, follow-up duration, and supportive care practices [14, 15, 18, 19]. Infection-related mortality accounts for approximately 2–4% of deaths and is a significant component of NRM [11, 18, 19]. NRM also varies according to disease type, with higher rates reported in mantle cell lymphoma (10.6%) and MM (8.0%) than in LBCL (6.1%) or indolent lymphoma (5.7%) [11].
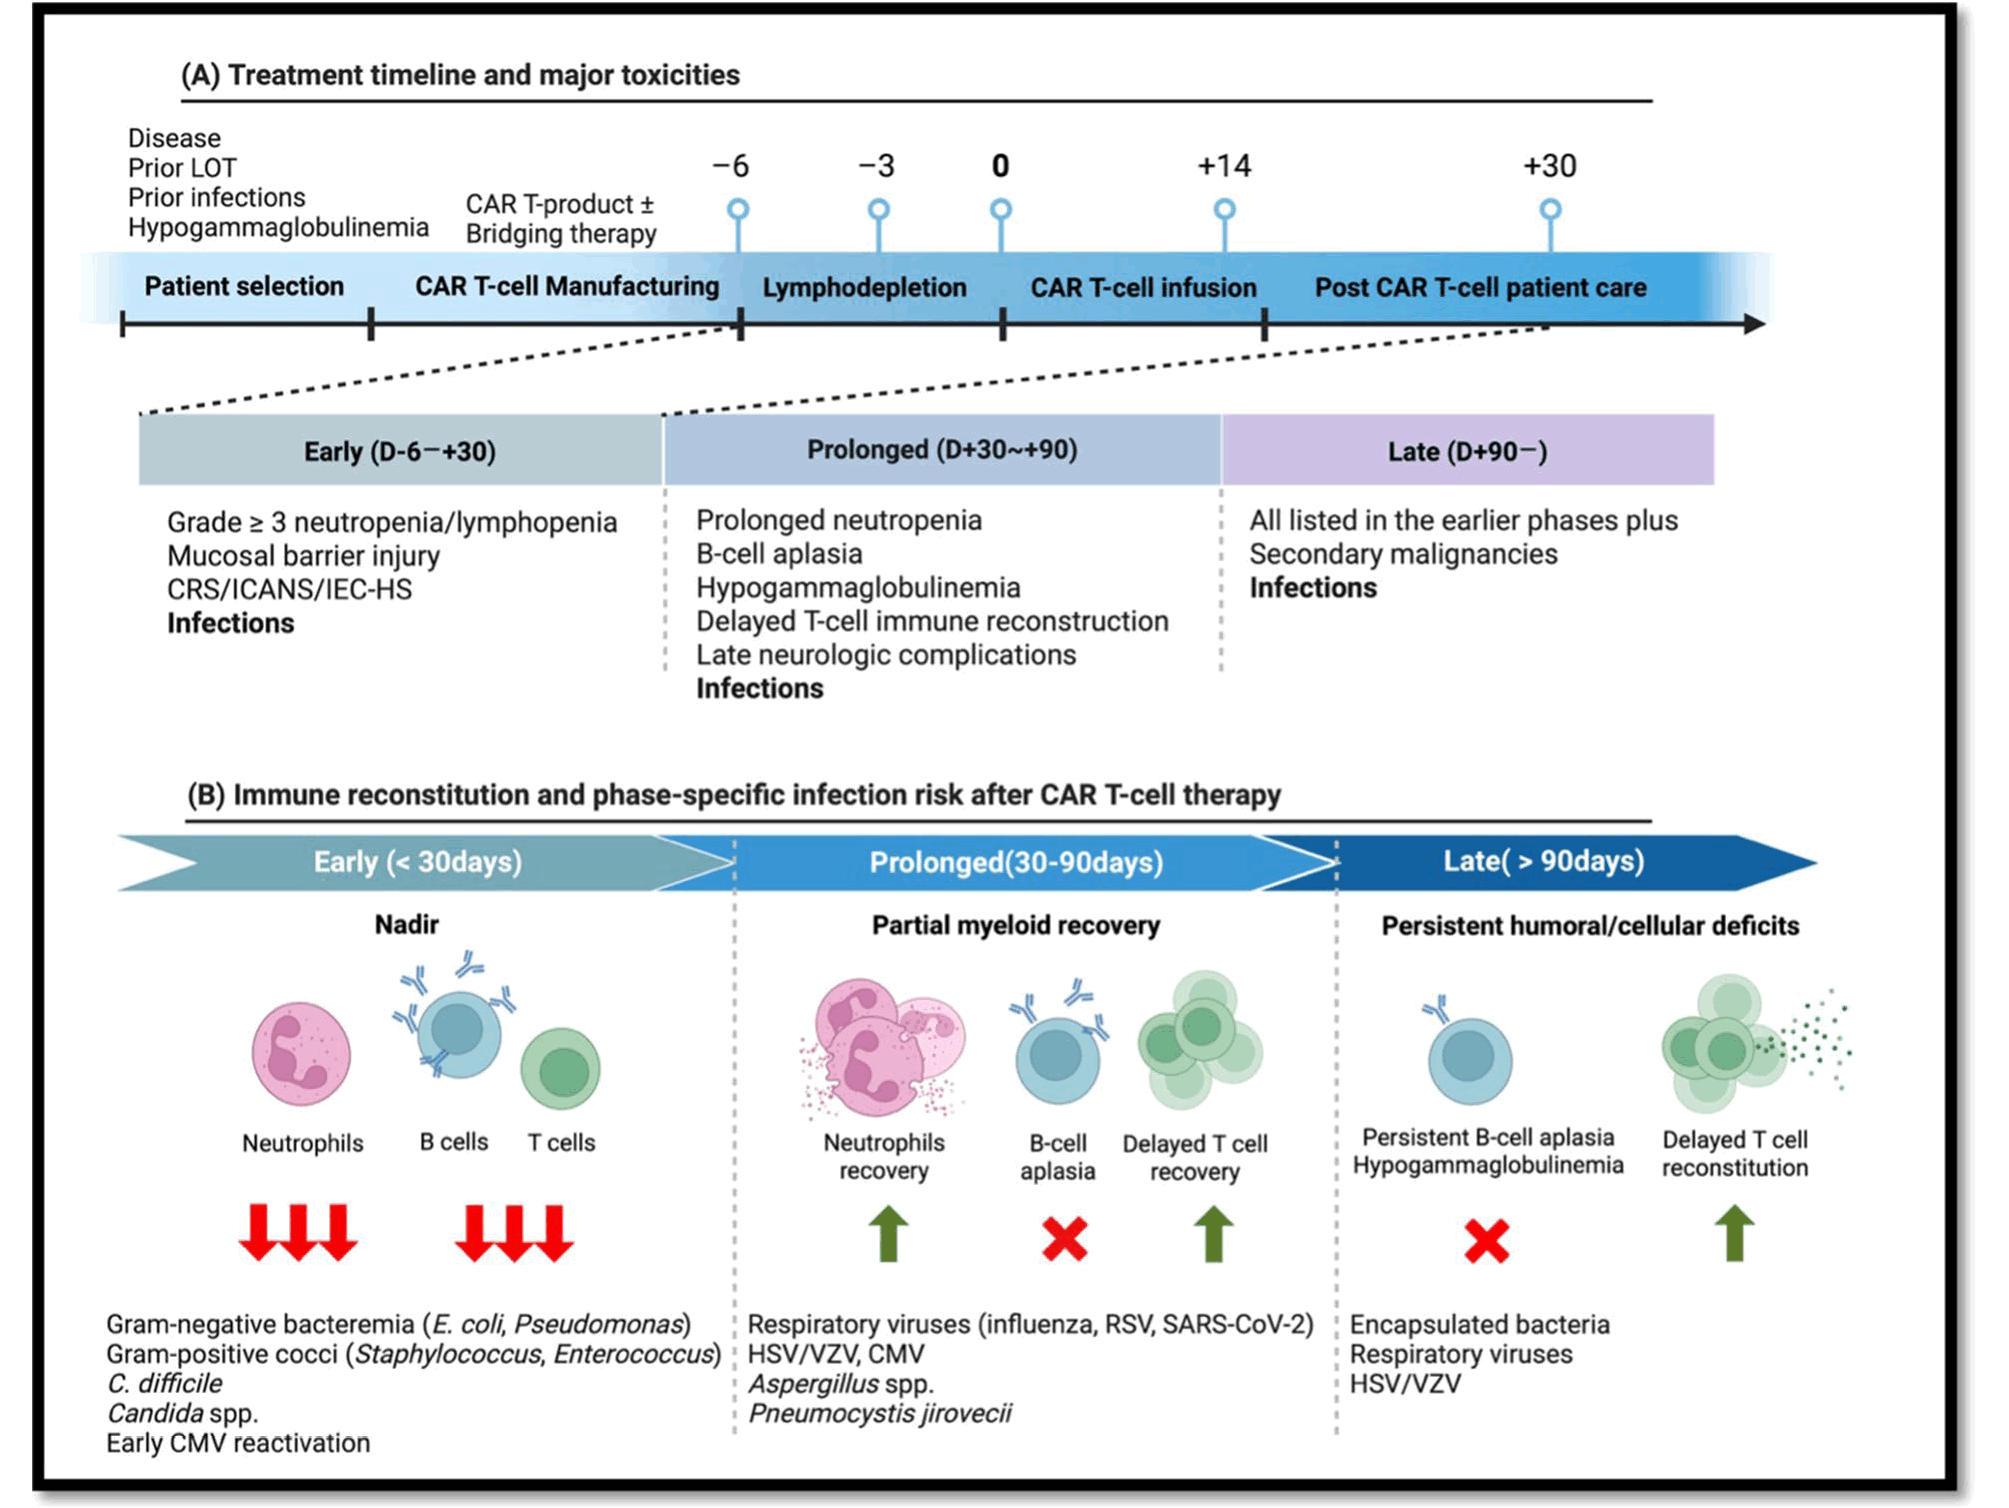
The infection risk is time-dependent and closely linked to the evolving immune dysfunction that follows CAR T-cell therapy. Three clinical phases are commonly described: early (< 30 days), prolonged (30–90 days), and late (> 90 days) [1416]. This temporal framework can help guide strategies for infection surveillance, antimicrobial prophylaxis, and vaccination.
During the early phase (days 0–30), patients experienced a hematologic nadir following lymphodepleting chemotherapy and CAR T-cell infusion. Profound neutropenia and lymphopenia are nearly universal and represent the major drivers of the risk of early infection [3, 16]. Neutrophil recovery typically begins within 2–4 weeks, although recovery kinetics vary widely [2022]. Some patients demonstrate a prompt and sustained recovery, whereas others develop delayed or biphasic cytopenia characterized by secondary decline after initial improvement [23]. These patterns may reflect bone marrow suppression, inflammatory signaling associated with CAR T-cell expansion, or limited marrow reserves from previous therapies [20, 21, 24]. Prolonged neutropenia is strongly associated with an increased risk of bacterial and invasive fungal infections (IFI) [14, 16].
Clinically, bacterial infections predominate in the early phases and are the leading cause of infectious morbidity [3, 15]. Gram-negative bacteremia, including Escherichia coli and Pseudomonas aeruginosa, as well as gram-positive infections, such as Staphylococcus and Enterococcus species, are commonly reported. These infections are often present as bloodstream pneumonia or catheterassociated infections [19]. Frequent exposure to antibiotics and gastrointestinal toxicity also increase the probability of Clostridioides difficile (C. difficile) infection, which should be considered in patients with similar symptoms. Early fungal infections are less common but may occur in patients with prolonged neutropenia or prior extensive immunosuppression, with Candida species being the most frequently reported [3, 25]. Viral infections are less prominent in the early phase but may emerge in patients who require high-dose corticosteroids or cytokine-directed therapy for severe CRS or ICANS [26, 27]. Reactivation of cytomegalovirus (CMV) infection has been described in selected high-risk populations within the first two to three weeks of infusion [26].
Several clinical factors contribute to delayed hematologic recovery and increased risk of infection after CAR T-cell therapy. High disease burden at infusion, extensive exposure to prior chemotherapy, previous autologous or allogeneic hematopoietic stem cell transplantation (HSCT), and baseline cytopenia are consistently associated with a diminished bone marrow reserve [20, 22, 28]. Severe CRS has also been associated with prolonged cytopenias, likely mediated by cytokinedriven marrow suppression and endothelial activation [20, 29]. Additionally, elevated levels of inflammatory markers such as ferritin and CRP further support the idea that systemic inflammation contributes to bone marrow dysfunction and delayed hematologic recovery after CAR T-cell therapy [21]. Persistent anemia and thrombocytopenia are often accompanied by neutropenia, which contributes to transfusion dependence, recurrent healthcare encounters, and cumulative immunological stress.
During the prolonged phase (days 30–90), neutrophil counts frequently recover but adaptive immune dysfunction persists. B-cell aplasia, hypogammaglobulinemia, and delayed CD4+ T-cell reconstitution continue to impair host defenses [3, 30, 31]. Consequently, viral and opportunistic infections have become increasingly prevalent [15, 16]. Respiratory viral infections, including influenza, respiratory syncytial virus, parainfluenza, and SARS-CoV-2, are the main sources of morbidity during this period and may require hospitalization [3, 15]. Herpes simplex virus (HSV) and varicella-zoster virus (VZV) infections can occur in the absence of antiviral prophylaxis [27]. CMV infections may persist or develop during this phase, particularly in patients receiving prolonged immunosuppressive therapy [26].
Fungal infections during the prolonged phase are less frequent than bacterial infections seen earlier after infusion, but cause substantial mortality when they occur [25]. Invasive mold infections, including Aspergillus species, are most commonly observed in patients with prolonged cytopenia, prior allogeneic hematopoietic cell transplantation, or exposure to high-dose corticosteroids [3, 25]. Pneumocystis jirovecii (PJP) has also emerged as a clinically relevant opportunistic infection during this window, particularly in patients who have not received adequate prophylaxis or with delayed T-cell recovery [16, 32].
Beyond 90 days after CAR T-cell therapy, the infection risk decreases but does not resolve completely [14, 30]. Late infections are largely driven by persistent humoral and cellular immune dysfunction rather than cytopenia [30, 33]. Persistent B-cell aplasia and hypogammaglobulinemia predispose patients to recurrent sinopulmonary infections, often caused by encapsulated bacteria [17, 30]. These infections may be repetitive and tend to contribute more to chronic morbidity than to acute mortality [30]. Viral susceptibility also persists in the late phase with an ongoing risk of respiratory viral infections and herpes virus reactivation [3, 30]. Vaccine responses are frequently suboptimal in this population, further complicating infection prevention efforts [30]. Opportunistic infections such as PJP or invasive fungal disease are rare, but may occur in patients with sustained immunosuppression or delayed immune reconstitution [30].
Together, these temporal patterns highlight that the risk of infection after CAR T-cell therapy is dynamic and closely related to the pace of immune recovery [14, 15]. Therefore, a time-adapted framework for infection surveillance and prophylaxis is essential to minimize NRM and improve long-term outcomes in CAR T-cell recipients [14]. These phases, their associated immune deficits, and infection risks are summarized in Fig. 1.

Pathophysiology of infection risk after CAR T‑cell therapy

Immune dysregulation

Susceptibility to infection after CAR T cell therapy reflects dynamic immune dysregulation rather than a single immunological defect. Lymphodepleting chemotherapy, CAR T-cell–mediated cytotoxicity, and immunosuppressive therapies used to manage therapy-related toxicities collectively shape the timing and spectrum of infections [3, 14, 15].
Early risk is primarily driven by profound cytopenia induced by lymphodepleting regimens. Nearly all patients develop neutropenia and lymphopenia, which alter innate and adaptive immune responses [14, 15]. Delayed or biphasic cytopenia may extend the vulnerability to the prolonged phase.
Delayed CD4+ T-cell reconstitution, including prolonged CD4+ lymphopenia and functional impairment, further increases susceptibility to viral and opportunistic infections, particularly beyond the early post-infusion phase [15, 34].
Immunosuppressive management of complications associated with immune effector cells further increases this risk. Corticosteroids and cytokine-targeted therapies (i.e., tocilizumab, anakinra) impair innate and adaptive immune function in a dose-dependent manner [3, 26, 33]. Patients requiring prolonged or multi-agent immunosuppression represent a particularly high-risk subgroup [11, 26, 32, 33].
Finally, host-related factors such as older age, prior therapy burden, prior HSCT, and comorbidities interact with CAR-T cell-specific immune perturbations to shape individual infection risks [14, 15, 19] (Table 1).

Differences in the risk of infection based on CAR T‑cell construct and disease entity

The risk of infection after CAR T-cell therapy is not uniform across all products or disease settings. Increasing clinical experience has highlighted meaningful differences in both the incidence and nature of infections based on the CAR T-cell construct and the underlying malignancy being treated [14, 34]. Among these, recipients of BCMA-directed CAR T-cell therapy appear to carry a particularly high infection burden compared with those treated with CD19-directed CAR T-cell products [11, 34, 35].
Lineage-specific immune defects contribute to susceptibility to infections. CD19-directed CAR T-cell therapy induces prolonged B-cell aplasia, leading to hypogammaglobulinemia and impaired humoral immunity [3, 30, 31, 36]. In contrast, BCMA-directed CAR T-cell therapy directly depletes plasma cells, resulting in a more profound and sustained antibody deficiency [30]. A central mechanistic driver of the increased risk of infection with BCMA-directed CAR T cell therapy is profound humoral immunodeficiency. In plasma cell–driven diseases, such as MM, this effect is further compounded by pre-existing immune dysfunction and cumulative prior therapies, resulting in severe and prolonged hypogammaglobulinemia [3740]. Comparative studies suggest that although early bacterial infection rates are broadly similar between CD19- and BCMA-directed CAR T-cell recipients, the pattern of infections diverges over time. In BCMAdirected CAR T cell therapy, subsequent infections, particularly respiratory viral and recurrent sinopulmonary bacterial infections, are more frequent and persistent. Opportunistic infections, including PJP and IFI, are also more frequently reported, particularly in patients who require prolonged corticosteroid exposure or additional immunosuppressive therapies [14, 16, 32, 34, 35].
In contrast, CD19-directed CAR T-cell therapy is more commonly associated with B-cell aplasia than with complete plasma cell depletion [3, 41]. Although hypogammaglobulinemia is still frequent, immunoglobulin levels may recover over time, and the infection risk may decline accordingly [14, 41]. Nevertheless, patients with delayed B-cell recovery remain vulnerable to late infections, reflecting the heterogeneity within CD19-directed treatment populations [17, 41].
In addition to the target antigen–related differences, the costimulatory domain may further modulate the risk of infection. CD28-based CAR T-cell constructs are associated with rapid expansion and higher rates of severe CRS and ICANS, often requiring immunosuppressive therapy and contributing to an increased risk of early infection. In contrast, 4-1BB-based constructs exhibit prolonged persistence, which can lead to sustained B-cell aplasia and a greater burden of late infections [4245].
Disease-specific factors further increase the risk of infection in patients with MM. Patients with myeloma often enter CAR T-cell therapy with advanced age, extensive prior exposure to immunosuppressive agents, baseline cytopenia, renal dysfunction, and compromised marrow reserve. The prior use of proteasome inhibitors, immunomodulatory drugs, monoclonal antibodies, and corticosteroids contributes to cumulative immune exhaustion [32, 39]. In addition, myeloma-related immune paresis and impaired antigen presentation persist even after disease response, limiting immune recovery despite effective tumor control [39, 40].
These overlapping factors help explain why infectionrelated morbidity and mortality appear disproportionately higher in patients with MM undergoing CAR T-cell therapy [11, 35]. Our findings have several practical implications. They support earlier considerations of immunoglobulin replacement, heightened vigilance for viral infections, and more aggressive risk-adapted prophylactic strategies in BCMA-directed CAR-T cell recipients [17, 32]. As newer CAR T-cell constructs and bispecific therapies continue to emerge, understanding construct- and disease-specific infection risks is essential to refine prevention strategies and minimize NRM [46, 47]. The mechanistic differences in humoral immune depletion with CD19- versus BCMA-directed CAR-T cell therapy are illustrated in Fig. 2.
A similar pattern of disease-related vulnerability has been observed in other lymphoma subtypes, particularly mantle cell lymphoma (MCL). Patients with MCL receiving CAR T-cell therapy often represent an older and heavily pretreated population with limited bone marrow reserve and baseline immune dysfunction. Although product-related factors, including the toxicity profile of brexucabtagene autoleucel, may contribute to the higher NRM observed in the MCL group, it is more likely driven by cumulative patient vulnerability and infection-related complications, which ultimately translate into an increased burden of severe and sometimes fatal infections [48].

Hematologic recovery and infection susceptibility

Hematologic recovery after CAR T-cell therapy is heterogeneous and plays a central role in determining susceptibility to infection across all post-infusion phases. Although early cytopenias are nearly universal and largely attributable to lymphodepleting chemotherapy, a substantial proportion of patients experience delayed, prolonged, or biphasic cytopenias that extend vulnerability to infection beyond the first month after treatment [21, 22, 49].
Neutrophil recovery following CAR T-cell infusion typically begins within 2–4 weeks; however, recovery kinetics vary widely [22, 49]. Some patients demonstrate rapid and sustained neutrophil recovery, whereas others develop delayed recovery or secondary decline after the initial improvement [50]. These biphasic patterns are increasingly recognized and may reflect inflammatory signaling associated with CAR T-cell expansion or limited bone marrow reserve from prior therapies [21, 24, 49]. In patients with prolonged or unexplained cytopenia, a bone marrow evaluation may be required to assess the marrow reserve and exclude alternative etiologies [49]. Importantly, prolonged neutropenia is strongly associated with an increased risk of bacterial and IFI [14, 16].
Several clinical factors have been associated with delayed or prolonged cytopenia after CAR T-cell therapy, including a high disease burden at infusion, extensive prior chemotherapy exposure, prior autologous or allogeneic HSCT, and baseline cytopenia [21, 28]. Severe CRS has also been associated with prolonged cytopenias, likely mediated through cytokine-driven marrow suppression and endothelial activation [29, 49]. Elevated levels of inflammatory markers such as ferritin and CRP are similarly associated with delayed hematologic recovery [22].
These observations have led to the development of risk stratification tools to better predict hematological toxicity after CAR T-cell therapy. One such model, the CAR-HEMATOTOX score, integrates baseline hematological and inflammatory parameters to estimate the risk of immune effector cell–associated hematotoxicity. Higher CAR-Hematotox scores are associated with prolonged cytopenia, severe infections, and increased NRM. Prospective validation studies have further supported its ability to identify patients at high risk of delayed hematologic recovery and infection-related complications [32, 34, 51].
The clinical consequences of prolonged cytopenia extend beyond those of neutropenia. Persistent anemia and thrombocytopenia contribute to transfusion dependence and increased healthcare utilization, whereas recurrent hospitalization and prolonged antimicrobial exposure may further increase the risk of resistant infections. These factors may collectively increase the risk of infection during the prolonged and late post-infusion phases [22, 49].
Granulocyte colony-stimulating factor (G-CSF) is frequently used to support neutrophil recovery after CAR-T cell therapy, although its optimal timing remains debatable. Early concerns suggested that G-CSF may exacerbate CRS or ICANS by enhancing myeloid activation. However, emerging clinical experience suggests that delayed administration, typically after resolution of CRS and ICANS, does not significantly increase toxicity and may shorten the duration of neutropenia [50, 52]. Consequently, many centers avoid G-CSF during the first 5 days after infusion and initiate G-CSF treatment approximately 7–14 days (or later) in patients with persistent grade 3–4 neutropenia and high infection risk [17, 28, 53].
Despite evolving experience, no universally accepted strategy has been proposed for managing post–CAR T-cell cytopenia. Therefore, clinical decisions regarding the use of growth factors, transfusion support, and infection prophylaxis are often individualized, based on patient-specific risk factors and institutional practices [33, 49]Understanding cytopenia kinetics and marrow reserve provides essential context to interpret risk of infection across post-infusion phases and informs subsequent discussions on targeted prophylaxis and monitoring strategies [21, 22].

Antimicrobial prophylaxis and vaccination: evidence‑based and risk‑adapted prevention

Antimicrobial prophylaxis is a central component of infection prevention after CAR T-cell therapy, but must balance efficacy with toxicity, antimicrobial resistance, and risk of overtreatment [16, 33]. Current preventive strategies are largely extrapolated from HSCT and intensive chemotherapy settings, although specific evidence relative to CAR cells and guideline recommendations are emerging [54, 55]. Prevention of infection after CAR T-cell therapy generally follows a phaseadapted and risk-stratified approach. Key international guideline recommendations for antibacterial, antiviral, and antifungal prophylaxis from the European Society for Blood and Marrow Transplantation (EBMT) and the American Society for Transplantation and Cellular Therapy (ASTCT) are summarized and compared in Table 2. Practical antimicrobial prophylaxis and vaccination strategies after CAR T-cell therapy are summarized in Table 3.

Antibacterial prophylaxis

Fluoroquinolone prophylaxis is selective, rather than universal. The National Comprehensive Cancer Network (NCCN) and the American Society of Clinical Oncology (ASCO)/Infectious Diseases Society of America (IDSA) recommend fluoroquinolone prophylaxis use during severe neutropenia, considering institutional resistance patterns and Clostridioides difficile infection [58]. In CAR T-cell recipients, antibacterial prophylaxis is typically reserved for patients with an absolute neutrophil count (ANC) < 500/μL and is discontinued upon neutrophil recovery [16, 54, 59]. Empiric broad-spectrum antimicrobial therapy should not be delayed in febrile patients even when CRS is suspected [22].

Antiviral prophylaxis

HSV and VZV prophylaxis with acyclovir or valacyclovir is universally recommended, typically initiated with lymphodepleting chemotherapy and continued for at least 1 year [32, 54]. This recommendation reflects prolonged T-cell dysfunction beyond the neutropenic period [16, 27]. Routine prophylaxis for cytomegalovirus (CMV) is not recommended; instead, a risk-adapted surveillance approach is generally employed in selected high-risk patients. Further details regarding CMV reactivation patterns and management are discussed in Sect. "CMV Reactivation" [26, 6063].

Antifungal prophylaxis

Fluconazole is commonly used to prevent candidiasis [16, 32]. Mold-active prophylaxis is generally reserved for patients with established risk factors, including prolonged neutropenia, prior invasive fungal infection (IFI), prior allo-HSCT, or prolonged or high-dose corticosteroid exposure [16, 51, 64]. In addition to the EBMT and ASTCT guidelines, the updated ECIL-10 recommendations provide a more structured, risk-adapted framework for antifungal prophylaxis in CAR-T cell recipients. Notably, ECIL-10 distinguishes between pre-infusion factors (e.g., prior therapies, baseline cytopenia, and prior IFI) and postinfusion factors (e.g., CRS requiring corticosteroids, prolonged neutropenia, or the use of additional immunosuppressive agents) and suggests that mold-active prophylaxis should be considered when such risk factors are present. This approach extends previous guideline recommendations by incorporating dynamic treatmentrelated risk factors specific to CAR T-cell therapy [51].

Vaccination after CAR T‑cell therapy

Current guidelines and expert consensus statements suggest that vaccination after CAR T cell therapy should be considered in the context of delayed and variable immune reconstitution. Inactivated vaccines are generally considered safe and are typically initiated approximately 3–6 months after infusion, whereas live vaccines should be deferred following more complete immune recovery, often 12–24 months post-therapy [6570].
Vaccine responsiveness is frequently reduced after CAR T-cell therapy, largely reflecting impaired humoral immunity [67, 71, 72]. Although responses may improve with B-cell recovery, serological measures alone do not consistently predict protective immunity [73]. Vaccination is generally used as a complementary strategy along with antimicrobial prophylaxis and intravenous immunoglobulin (IVIG) in high-risk patients [65, 66]. Vaccination of household contacts is also commonly recommended to improve indirect protection [16, 65, 74]. Given the limited prospective data in this setting, current practice often relies on a pragmatic, time-based approach with selective consideration of immune recovery and the clinical context [65, 67].

Role of intravenous immunoglobulin

Hypogammaglobulinemia is a common complication after CD19- and BCMA-directed CAR T-cell therapy and contributes to intermediate and late risk of infection [17, 75]. IVIG provides passive antibody replacement and may enhance opsonization and immune modulation [75, 76]. Current practice favors selective administration [17, 75]. Most guidelines recommend IVIG in patients with serum IgG levels < 400–600 mg/dL accompanied by recurrent or severe infections. The typical dose is 400–500 mg/kg of IVIG every 3–4 weeks, with the practical goal of maintaining serum IgG at > 400–600 mg/dL. BCMA-directed CAR T-cell therapy, particularly for patients with MM, may warrant earlier consideration because of plasma cell depletion and sustained antibody deficiency [17, 32, 40]. Routine prophylactic IVIG is not recommended for any recipients (Table 4).
IVIG use must balance benefits with cost and infusion burden and should be guided by the clinical context, including infection history and degree of immune recovery, while considering potential adverse effects, such as thrombosis and renal dysfunction [7577].

Infection screening and monitoring

Baseline screening

Pre–CAR T evaluation includes HIV testing, hepatitis B and C serologies, and evaluation of CMV status, with antiviral prophylaxis for patients at risk of hepatitis B reactivation [16, 17, 78, 79]. Screening for tuberculosis, Strongyloides, or endemic fungi infections should be guided by epidemiologic exposure risk [54, 80]. Active infections should be identified and controlled before administering lymphodepleting chemotherapy.

Post–CAR T surveillance

Routine surveillance culture is not recommended for asymptomatic patients. Instead, post-CAR T cell monitoring is guided by clinical status and individual risk factors [32]. CMV polymerase chain reaction (PCR) monitoring is generally performed in high-risk patients. A detailed discussion of CMV reactivation patterns, risk factors, and management strategies is provided in Sect. "CMV Reactivation" [26, 32].

Distinguishing infection from CRS/ICANS

Fever, hypotension, and neurological symptoms overlap between infections and immune effector cell-associated toxicity [3, 16, 17]. Therefore, clinicians should maintain a low threshold for diagnostic evaluation and empirical antimicrobial therapy when an infection is suspected. Biomarkers such as CRP and ferritin are nonspecific and should be interpreted with caution in this setting [17, 33]. Interleukin-6 (IL-6) levels are also of limited diagnostic value, particularly in patients who have received anti-IL-6 therapy, as circulating IL-6 levels may remain elevated due to receptor blockade. In patients with persistent fever after CAR T-cell infusion, careful evaluation of atypical infections, including viral, fungal, and opportunistic pathogens, is essential. At the same time, clinicians should consider the possibility of IEC-HS and perform appropriate laboratory assessments, including liver function tests and fibrinogen levels, to allow timely recognition and management, including anti-IL-1–directed therapy when indicated.
Therefore, infection screening and monitoring after CAR T-cell therapy requires careful baseline evaluation and risk-adapted surveillance during follow-up [36, 80]. Early recognition of infection is essential for guiding diagnostic evaluation and timely antimicrobial therapy in this highly immunocompromised population.

Special clinical scenarios

COVID‑19

CAR T recipients may experience prolonged viral shedding and impaired vaccine responses due to B cell depletion [8184]. Infection that occurs early after infusion or during periods of immunosuppression carries an increased risk of severe disease [60, 81]. Thus, early antiviral therapy and repeated diagnostic testing may be required in patients with persistent symptoms [61, 84].
The management of SARS-CoV-2 infection before CAR T-cell therapy should be guided by symptom severity. In symptomatic patients, CAR T-cell infusion is generally delayed for approximately 7–14 days until clinical improvement is achieved. Repeated SARS-CoV-2 testing after symptom resolution is not always required. Antiviral therapies, such as remdesivir or nirmatrelvir/ritonavir, should be considered when clinically indicated.
In patients with asymptomatic or mild infections, CAR T-cell therapy may be considered in selected cases, although delayed treatment is generally preferred when feasible. Clinical decision-making should consider symptom severity, evidence of lower respiratory tract involvement, inflammatory markers, and the urgency of treating the underlying malignancy [62].

Invasive fungal infections

Although IFI is relatively rare after CAR T-cell therapy, it is associated with substantial mortality and occurs in a setting of cumulative and evolving immunosuppression. This risk reflects the interplay of multiple baseline and treatment-related factors rather than a single dominant determinant [3, 25]. Recent guideline updates, including ECIL-10, emphasize risk stratification by integrating both pre-infusion (e.g., prior therapies, baseline cytopenia, or prior IFI) and post-infusion factors (e.g., CRS requiring corticosteroids, prolonged neutropenia, or additional immunosuppressive therapy) [51]. The NCCN guidelines for MM further define high-risk scenarios based on treatment-related immunosuppression, including corticosteroid exposure (≥ 10 mg dexamethasone daily for > 3 days within a 7-day period), receipt of ≥ 1 g methylprednisolone per day, more than one dose of tocilizumab, or the use of additional immunosuppressive agents such as anakinra or siltuximab [32]. In this context, persistent respiratory symptoms or unexplained fever should prompt early imaging and evaluation of IFI [63, 85].

CMV reactivation

CMV reactivation is increasingly recognized after CAR T-cell therapy, typically occurring within the first month after infusion, with a reported incidence ranging from approximately 17% to 56% and clinically significant infection in a smaller subset [8689].
In contrast to allo-HSCT, current guidelines do not support universal CMV surveillance in CAR T-cell recipients [16, 56, 57]. The ECIL-10 recommendations suggest a risk-adapted approach, in which monitoring is considered primarily in CMV-seropositive patients with additional risk factors such as severe CRS, prolonged corticosteroid exposure, use of multiple immunosuppressive agents, or persistent lymphocytopenia. In these patients, CMV PCR monitoring may be performed during the early post-infusion period, typically between 2 and 6 weeks after CAR T-cell therapy, with the frequency adjusted according to the clinical course and immunosuppressive burden [26].
Preemptive therapy is generally initiated in the setting of high or rapidly increasing CMV DNAemia. However, ECIL-10 emphasizes that no universal viral load threshold can be defined and treatment decisions should be based on center-specific cut-offs, considering assay performance and calibration using WHO International Standard Units (IU/mL). From a clinical perspective, it is important to distinguish asymptomatic CMV DNAemia from clinically significant CMV infection and CMV end-organ disease because these entities have different management implications. When treatment is indicated, antiviral options, such as valganciclovir, ganciclovir, and foscarnet, may be considered. In the CAR T-cell setting, drug selection should account for toxicity profiles, particularly myelosuppression associated with ganciclovir-based therapies, which may limit their use in patients with ongoing cytopenia.
Given the absence of prospective CAR-T cell-specific data, current CMV monitoring and management strategies are largely extrapolated from the HSCT experience, which may limit their direct applicability in this setting.

Conclusions

Current infection prevention strategies after CAR T-cell therapy are largely extrapolated from experience with intensive chemotherapy and HSCT and are primarily based on observed infection patterns rather than on evidence from randomized controlled trials. As CAR T-cell therapy continues to expand, more individualized approaches are needed. In this context, integrated patient-specific risk assessments may play an increasingly important role in guiding monitoring and preventive strategies. Biomarkerguided strategies that incorporate dynamic CD4+ T cell counts, B cell recovery, and immunoglobulin levels may help refine risk-adapted prevention, although prospective validation remains necessary. In addition, the infection risk appears to vary across CAR T constructs, particularly with a more profound and sustained humoral deficiency observed in BCMA-directed therapy. As next-generation cellular therapies, including newer targets and dual-target constructs, are introduced into clinical practice, defining their long-term infectious profiles will be an important priority for future research.
Acknowledgements

The authors The State University of New Jersey, Rutgers, and Rutgers Health Community Medical Center for their continued academic support and collaborative environment that made this work possible. Part of this work was presented as an educational lecture at the 9th International Congress of Blood and Marrow Transplantation (BMT 2025) and the 30th Annual Congress of the Korean Society of Blood and Marrow Transplantation (KSBMT 2025 International Conference).

Notes

Authors’ contributions

Eunseuk Lee and Ji Hyun Lee wrote the main manuscript text and prepared the figures and tables. All authors reviewed the manuscript and approved the final version.

Funding

This study was supported by the Dong-A University Research Fund.

Data availability

No datasets were generated or analysed during the current study.

Declarations

Competing interests

The authors declare no competing interests.

Publisher’s Note

Springer Nature remains neutral with regard to jurisdictional claims in published maps and institutional affiliations.

REFERENCES

1. B-Cell Lymphomas. NCCN Clinical Practice Guidelines in Oncology. Version 1.2026.
2. Sehn LH, Salles G. 2021; Diffuse large B-cell lymphoma. N Engl J Med. 384(9):842–58. DOI: 10.1056/NEJMra2027612. PMID: 33657296. PMCID: PMC8377611.
3. Brudno JN, Maus MV, Hinrichs CS. 2024; CAR T cells and T-cell therapies for cancer: a translational science review. JAMA. 332(22):1924–35. DOI: 10.1001/jama.2024.19462. PMID: 39495525. PMCID: PMC11808657.
4. Neelapu SS, et al. 2021; Comparison of 2-year outcomes with CAR T cells (ZUMA-1) vs salvage chemotherapy in refractory large B-cell lymphoma. Blood Adv. 5(20):4149–55. DOI: 10.1182/bloodadvances.2020003848. PMID: 34478487. PMCID: PMC8945634.
5. A VS, et al. Tisagenlecleucel vs. historical standard of care in children and young adult patients with relapsed/refractory B-cell precursor acute lymphoblastic leukemia. Leukemia. 2023;37(12):2346-55. 10.1038/s41375-023-02042-4 37880478 PMC10681894
6. Puig N, et al. 2024; Measurable residual disease by mass spectrometry and next-generation flow to assess treatment response in myeloma. Blood. 144(23):2432–8. DOI: 10.1182/blood.2024024995. PMID: 39293025.
7. Cappell KM, Kochenderfer JN. 2023; Long-term outcomes following CAR T cell therapy: what we know so far. Nat Rev Clin Oncol. 20(6):359–71. DOI: 10.1038/s41571-023-00754-1. PMID: 37055515. PMCID: PMC10100620.
8. Bock TJ, et al. 2025; Outcome correlates of approved CD19-targeted CAR T cells for large B cell lymphoma. Nat Rev Clin Oncol. 22(4):241–61. DOI: 10.1038/s41571-025-00992-5. PMID: 39966627.
9. Kuhnl A, et al. 2022; A national service for delivering CD19 CAR-Tin large B-cell lymphoma - the UK real-world experience. Br J Haematol. 198(3):492–502. DOI: 10.1111/bjh.18209. PMID: 35485402. PMCID: PMC9733886.
10. Czapka MT, Riedell PA, Pisano JC. 2023; Infectious complications of CAR T-cell therapy: a longitudinal risk model. Transpl Infect Dis. 25(Suppl 1):e14148. DOI: 10.1111/tid.14148. PMID: 37695203.
11. Cordas Dos Santos DM, et al. 2024; A systematic review and metaanalysis of nonrelapse mortality after CAR T cell therapy. Nat Med. 30(9):2667–78. DOI: 10.1038/s41591-024-03084-6. PMID: 38977912. PMCID: PMC11765209.
12. Lemoine J, et al. 2023; Nonrelapse mortality after CAR T-cell therapy for large B-cell lymphoma: a LYSA study from the DESCAR-T registry. Blood Adv. 7(21):6589–98. DOI: 10.1182/bloodadvances.2023010624. PMID: 37672383. PMCID: PMC10641092.
13. Penack O, et al. 2023; Organ complications after CD19 CAR T-cell therapy for large B cell lymphoma: a retrospective study from the EBMT transplant complications and lymphoma working party. Front Immunol. 14:1252811. DOI: 10.3389/fimmu.2023.1252811. PMID: 37828980. PMCID: PMC10565347. PMID: d5f9a6ad12ff48e2b04afd5d77a7a7a5.
14. Kampouri E, et al. 2023; Infections after chimeric antigen receptor (CAR)-T-cell therapy for hematologic malignancies. Transpl Infect Dis. 25(Suppl 1):e14157. DOI: 10.1111/tid.14157. PMID: 37787373.
15. Haidar G, Garner W, Hill JA. 2020; Infections after anti-CD19 chimeric antigen receptor T-cell therapy for hematologic malignancies: timeline, prevention, and uncertainties. Curr Opin Infect Dis. 33(6):449–57. DOI: 10.1097/QCO.0000000000000679. PMID: 33009139.
16. Prevention and Treatment of Cancer-Related Infections. NCCN(National Comprehensive Cancer Network). Version 2.2025-January 22, 2026.
17. Management of CAR T-Cell and Lymphocyte Engager-Related Toxicities. NCCN Clinical Practice Guidelines in Oncology. Version 2.2026-November 11, 2025.
18. Telli Dizman G, Aguado JM, Fernandez-Ruiz M. 2022; Risk of infection in patients with hematological malignancies receiving CAR T-cell therapy: systematic review and meta-analysis. Expert Rev Anti Infect Ther. 20(11):1455–76. DOI: 10.1080/14787210.2022.2128762. PMID: 36148506.
19. Wudhikarn K, et al. 2025; Infection after CD19 chimeric antigen receptor T-cell therapy for large B-cell lymphoma: real-world analysis from CIBMTR. Blood Adv. 9(21):5460–72. DOI: 10.1182/bloodadvances.2025016141. PMID: 40435511. PMCID: PMC12607006.
20. Jain MD, Smith M, Shah NN. 2023; How I treat refractory CRS and ICANS after CAR T-cell therapy. Blood. 141(20):2430–42. DOI: 10.1182/blood.2022017414. PMID: 36989488. PMCID: PMC10329191.
21. Rejeski K, et al. 2021; CAR-HEMATOTOX: a model for CAR T-cell-related hematologic toxicity in relapsed/refractory large B-cell lymphoma. Blood. 138(24):2499–513. DOI: 10.1182/blood.2020010543. PMID: 34166502. PMCID: PMC8893508.
22. Rejeski K, Subklewe M, Locke FL. 2023; Recognizing, defining, and managing CAR-T hematologic toxicities. Hematology Am Soc Hematol Educ Program. 2023(1):198–208. DOI: 10.1182/hematology.2023000472. PMID: 38066881. PMCID: PMC10727074.
23. Rejeski K, et al. 2023; Immune effector cell-associated hematotoxicity: EHA/EBMT consensus grading and best practice recommendations. Blood. 142(10):865–77. DOI: 10.1182/blood.2023020578. PMID: 37300386.
24. Si X, et al. 2022; Hematologic cytopenia post CAR T cell therapy: etiology, potential mechanisms and perspective. Cancer Lett. 550:215920. DOI: 10.1016/j.canlet.2022.215920. PMID: 36122628.
25. Bouvier A, et al. 2026; Invasive fungal infections after CD19 chimeric antigen receptor T-cell therapy for B-cell lymphoma: a Lymphoma study association study from the DESCAR-T (Dispositif d'Enregistrement et Suivi des patients traites par CAR-T cells) registry. Clin Microbiol Infect. 32(2):277–84. DOI: 10.1016/j.cmi.2025.10.005. PMID: 41109429.
26. Ljungman P, et al. 2025; Recommendations from the 10th European Conference on Infections in Leukaemia for the management of cytomegalovirus in patients after allogeneic haematopoietic cell transplantation and other T-cell-engaging therapies. Lancet Infect Dis. 25(8):e451–62. DOI: 10.1016/S1473-3099(25)00069-6. PMID: 40188837.
27. https://doi.org/10.3390/v17010133. DOI: 10.3390/v17010133. PMID: 39861922. PMCID: PMC11768728.
28. Hematopoietic Growth Factors. NCCN Clinical Practice Guidelines in Oncology. Version 3.2026.
29. Nakamura N, et al. 2024; Clinical impact of cytokine release syndrome on prolonged hematotoxicity after chimeric antigen receptor T Cell therapy: KyoTox A-Score, a novel prediction model. Transplant Cell Ther. 30(4):404–14. DOI: 10.1016/j.jtct.2024.01.073. PMID: 38281589.
30. Bishop MR. 2024; Late complications and long-term care of adult CAR T-cell patients. Hematology Am Soc Hematol Educ Program. 2024(1):109–15. DOI: 10.1182/hematology.2024000534. PMID: 39643985. PMCID: PMC11665735.
31. Kampouri E, et al. 2022; Managing hypogammaglobulinemia in patients treated with CAR-T-cell therapy: key points for clinicians. Expert Rev Hematol. 15(4):305–20. DOI: 10.1080/17474086.2022.2063833. PMID: 35385358.
32. Multiple Myeloma. NCCN Clinical Practice Guidelines in Oncology. Version 5.2026-January 9.2026.
33. Santomasso BD, et al. 2021; Management of immune-related adverse events in patients treated with chimeric antigen receptor T-cell therapy: ASCO guideline. J Clin Oncol. 39(35):3978–92. DOI: 10.1200/JCO.21.01992. PMID: 34724386.
34. Riedel A, et al. 2025; Immunological consequences of CAR T-cell therapy: an analysis of infectious complications and immune reconstitution. Blood Adv. 9(13):3149–58. DOI: 10.1182/bloodadvances.2024015346. PMID: 40188456. PMCID: PMC12242403. PMID: 9d3d4d650a4f4a4a92adc254b20ac611.
35. Reynolds GK, et al. 2023; Infections in haematology patients treated with CAR-T therapies: a systematic review and meta-analysis. Crit Rev Oncol Hematol. 192:104134. DOI: 10.1016/j.critrevonc.2023.104134. PMID: 37739146.
36. Hill JA, Seo SK. 2020; How I prevent infections in patients receiving CD19-targeted chimeric antigen receptor T cells for B-cell malignancies. Blood. 136(8):925–35. DOI: 10.1182/blood.2019004000. PMID: 32582924. PMCID: PMC7441168.
37. van de Donk N, et al. 2025; Optimising T-cell immunotherapy in patients with multiple myeloma: practical considerations from the European Myeloma Network. Lancet Haematol. 12(8):e635–49. DOI: 10.1016/S2352-3026(25)00117-6. PMID: 40580975.
38. Wang Y, et al. 2021; Humoral immune reconstitution after anti-BCMA CAR T-cell therapy in relapsed/refractory multiple myeloma. Blood Adv. 5(23):5290–9. DOI: 10.1182/bloodadvances.2021004603. PMID: 34587230. PMCID: PMC9153033.
39. van de Donk N, Usmani SZ, Yong K. 2021; CAR T-cell therapy for multiple myeloma: state of the art and prospects. Lancet Haematol. 8(6):e446–61. DOI: 10.1016/S2352-3026(21)00057-0. PMID: 34048683.
40. Josyula S, et al. Pathogen-Specific Humoral Immunity and Infections in B Cell Maturation Antigen-Directed Chimeric Antigen Receptor T Cell Therapy Recipients with Multiple Myeloma. Transplant Cell Ther, 2022;28(6):304. e1-304 e9. 10.1016/j.jtct.2022.03.005 35288345 PMC9197988
41. Wat J, Barmettler S. 2022; Hypogammaglobulinemia after chimeric antigen receptor (CAR) T-cell therapy: characteristics, management, and future directions. J Allergy Clin Immunol Pract. 10(2):460–6. DOI: 10.1016/j.jaip.2021.10.037. PMID: 34757064. PMCID: PMC8837681.
42. Maziarz RT, et al. 2026; Five-year analysis of the JULIET trial of Tisagenlecleucel in patients with relapsed/refractory large B-Cell lymphoma. J Clin Oncol. 44(2):86–91. DOI: 10.1200/JCO-25-00507. PMID: 41252666. PMCID: PMC12783362.
43. Neelapu SS, et al. 2023; Five-year follow-up of ZUMA-1 supports the curative potential of axicabtagene ciloleucel in refractory large B-cell lymphoma. Blood. 141(19):2307–15. DOI: 10.1182/blood.2022018893. PMID: 36821768. PMCID: PMC10646788.
44. Yang Y, et al. 2024; New insights into CAR T-cell hematological toxicities: manifestations, mechanisms, and effective management strategies. Exp Hematol Oncol. 13(1):110. DOI: 10.1186/s40164-024-00573-9. PMID: 39521987. PMCID: PMC11549815. PMID: 792ff3c390cb4a2e97d09c5b64d8c7d1.
45. Park JH, et al. 2018; Cytokine release syndrome grade as a predictive marker for infections in patients with relapsed or refractory B-Cell acute lymphoblastic leukemia treated with chimeric antigen receptor T Cells. Clin Infect Dis. 67(4):533–40. DOI: 10.1093/cid/ciy152. PMID: 29481659. PMCID: PMC6070095.
46. Brockelmann PJ, et al. 2025; Beyond maximum grade: tolerability of immunotherapies, cellular therapies, and targeted agents in haematological malignancies. Lancet Haematol. 12(6):e470–81. DOI: 10.1016/S2352-3026(25)00051-1. PMID: 40447355.
47. Arya S, Shahid Z. 2024; Overview of infectious complications among CAR T- cell therapy recipients. Front Oncol. 14:1398078. DOI: 10.3389/fonc.2024.1398078. PMID: 39026972. PMCID: PMC11255439. PMID: be61085824aa40cabb673de713c34e14.
48. Wang M, et al. 2020; KTE-X19 CAR T-Cell therapy in relapsed or refractory mantlecell lymphoma. N Engl J Med. 382(14):1331–42. DOI: 10.1056/NEJMoa1914347. PMID: 32242358. PMCID: PMC7731441.
49. Jain T, Olson TS, Locke FL. 2023; How I treat cytopenias after CAR T-cell therapy. Blood. 141(20):2460–9. DOI: 10.1182/blood.2022017415. PMID: 36800563. PMCID: PMC10646792.
50. Rejeski K, et al. 2024; Immune effector cell-associated haematotoxicity after CAR T-cell therapy: from mechanism to management. Lancet Haematol. 11(6):e459–70. DOI: 10.1016/S2352-3026(24)00077-2. PMID: 38734026. PMCID: PMC12413773.
51. Pagano L, et al. 2025; Primary antifungal prophylaxis in hematological malignancies. Updated clinical practice guidelines by the European Conference on Infections in Leukemia (ECIL). Leukemia. 39(7):1547–57. DOI: 10.1038/s41375-025-02586-7. PMID: 40200079. PMCID: PMC12208874.
52. Lievin R, et al. 2022; Effect of early granulocyte-colony-stimulating factor administration in the prevention of febrile neutropenia and impact on toxicity and efficacy of anti-CD19 CAR-T in patients with relapsed/refractory B-cell lymphoma. Bone Marrow Transplant. 57(3):431–9. DOI: 10.1038/s41409-021-01526-0. PMID: 35094012. PMCID: PMC8907072.
53. Schubert ML, et al. 2021; Side-effect management of chimeric antigen receptor (CAR) T-cell therapy. Ann Oncol. 32(1):34–48. DOI: 10.1016/j.annonc.2020.10.478. PMID: 33098993.
54. Gudiol C, et al. 2021; Chimeric antigen receptor T-cell therapy for the treatment of lymphoid malignancies: is there an excess risk for infection? Lancet Haematol. 8(3):e216–28. DOI: 10.1016/S2352-3026(20)30376-8. PMID: 33460558.
55. Stemler J, et al. 2023; Primary prophylaxis of invasive fungal diseases in patients with haematological malignancies: 2022 update of the recommendations of the Infectious Diseases Working Party (AGIHO) of the German Society for Haematology and Medical Oncology (DGHO). J Antimicrob Chemother. 78(8):1813–26. DOI: 10.1093/jac/dkad143. PMID: 37311136. PMCID: PMC10393896.
56. Greco R, et al. 2025; Indications for haematopoietic cell transplantation and CAR-T for haematological diseases, solid tumours and immune disorders: 2025 EBMT practice recommendations. Bone Marrow Transplant. 60(11):1499–525. DOI: 10.1038/s41409-025-02701-3. PMID: 40926035. PMCID: PMC12583170.
57. Shahid Z, et al. 2024; Best practice considerations by The American Society of Transplant and Cellular Therapy: infection prevention and management after chimeric antigen receptor T cell therapy for hematological malignancies. Transplant Cell Ther. 30(10):955–69. DOI: 10.1016/j.jtct.2024.07.018. PMID: 39084261. PMCID: PMC12826105.
58. Taplitz RA, et al. 2018; Antimicrobial prophylaxis for adult patients with cancerrelated immunosuppression: ASCO and IDSA clinical practice guideline update. J Clin Oncol. 36(30):3043–54. DOI: 10.1200/JCO.18.00374. PMID: 30179565.
59. Liu C, et al. 2026; Tackling antimicrobial resistance in people who are immunocompromised: leveraging diagnostic and antimicrobial stewardship. Lancet Infect Dis. 26(1):e30–48. DOI: 10.1016/S1473-3099(25)00311-1. PMID: 40812337. PMCID: PMC13218428.
60. Al-Ramahi JS, et al. 2023; Lessons learned from COVID-19 pandemic: outcomes after SARS-CoV-2 infection in hematopoietic cell transplant and cell therapy recipients. Leuk Lymphoma. 64(12):1981–91. DOI: 10.1080/10428194.2023.2243355. PMID: 37574842.
61. Rosen EA, et al. 2024; COVID-19 outcomes among hematopoietic cell transplant and chimeric antigen receptor T-cell recipients in the era of SARS-CoV-2 Omicron variants and COVID-19 therapeutics. Transplant Cell Ther. 30(11):1108 e1–1108 e11. DOI: 10.1016/j.jtct.2024.08.010. PMID: 39179107. PMCID: PMC11540736.
62. Tabbara N, Dioverti-Prono MV, Jain T. 2024; Mitigating and managing infection risk in adults treated with CAR T-cell therapy. Hematology Am Soc Hematol Educ Program. 2024(1):116–25. DOI: 10.1182/hematology.2024000535. PMID: 39644015. PMCID: PMC11706248.
63. Pennese E, et al. 2023; Case report: invasive fungal infection after anti-CD19 CAR-T cell therapy. Implication for antifungal prophylaxis. Front Immunol. 14:1272798. DOI: 10.3389/fimmu.2023.1272798. PMID: 37841271. PMCID: PMC10574963. PMID: 429862a72249402aab3562460f3fa147.
64. Dadwal SS, et al. 2021; American Society of Transplantation and Cellular Therapy Series, 2: management and prevention of aspergillosis in hematopoietic cell transplantation recipients. Transplant Cell Ther. 27(3):201–11. DOI: 10.1016/j.jtct.2020.10.003. PMID: 33781516. PMCID: PMC9088165.
65. Kamboj M, et al. 2024; Vaccination of adults with cancer: ASCO guideline. J Clin Oncol. 42(14):1699–721. DOI: 10.1200/JCO.24.00032. PMID: 38498792. PMCID: PMC11095883.
66. Survivorship. NCCN Clinical Practice Guidelines in Oncology. Version 3.2025 -February 2, 2026.
67. Einarsdottir S, et al. 2025; Humoral vaccine responses following chimeric antigen receptor T-cell therapy for hematological malignancies. Blood Cancer J. 15(1):114. DOI: 10.1038/s41408-025-01321-w. PMID: 40603286. PMCID: PMC12223166. PMID: a39031300d8b4eb1a00452e79a6d425f.
68. Aleissa MM, et al. Severe Acute Respiratory Syndrome Coronavirus 2 Vaccine Immunogenicity among Chimeric Antigen Receptor T Cell Therapy Recipients. Transplant Cell Ther. 2023;29(6):398. e1-398 e5. 10.1016/j.jtct.2023.03.005 36906276 PMC9995387
69. Lee D, et al.Pneumococcal Conjugate Vaccine Does Not Induce Humoral Response When Administrated Within the Six Months After CD19 CAR T-Cell Therapy. Transplant Cell Ther. 2023;29(4):277. e1-277 e9. 10.1016/j.jtct.2022.08.011 35970303
70. Khawaja F, et al. 2023; Frequently asked questions on Coronavirus Disease 2019 vaccination for hematopoietic cell transplantation and chimeric antigen receptor T-Cell recipients from the American Society for Transplantation and Cellular Therapy and the American Society of Hematology. Transplant Cell Ther. 29(1):10–8. DOI: 10.1016/j.jtct.2022.10.010. PMID: 36273782. PMCID: PMC9584756.
71. Hill JA, et al. 2024; SARS-CoV-2 vaccination in the first year after hematopoietic cell transplant or chimeric antigen receptor T-Cell therapy: A prospective, multicenter, observational study. Clin Infect Dis. 79(2):542–54. DOI: 10.1093/cid/ciae291. PMID: 38801746. PMCID: PMC11327798.
72. https://doi.org/10.3390/cancers14143527. DOI: 10.3390/cancers14143527. PMID: 35884587. PMCID: PMC9319387.
73. Kinoshita H, et al. 2025; T Cell immune response to Influenza Vaccination when administered prior to and following autologous Chimeric Antigen Receptor-Modified T Cell Therapy. Transplant Cell Ther. 31(5):327–38. DOI: 10.1016/j.jtct.2025.02.019. PMID: 40032074. PMCID: PMC12058394.
74. Pediatric Acute Lymphoblastic Leukemia. NCCN Clinical Practice Guidelines in Oncology. Version 1.2026.
75. Otani IM, et al. 2022; Practical guidance for the diagnosis and management of secondary hypogammaglobulinemia: a work group report of the AAAAI Primary Immunodeficiency and Altered Immune Response Committees. J Allergy Clin Immunol. 149(5):1525–60. DOI: 10.1016/j.jaci.2022.01.025. PMID: 35176351.
76. Wonnaparhown A, et al. 2024; IgG replacement in multiple myeloma. Blood Cancer J. 14(1):124. DOI: 10.1038/s41408-024-01107-6. PMID: 39054331. PMCID: PMC11272770. PMID: b7df78badc9b43dcb87026e9eb8b09be.
77. Ludwig H, et al. 2023; Prevention and management of adverse events during treatment with bispecific antibodies and CAR T cells in multiple myeloma: a consensus report of the European Myeloma Network. Lancet Oncol. 24(6):e255–69. DOI: 10.1016/S1470-2045(23)00159-6. PMID: 37269857. PMCID: PMC12402850.
78. Ali FS, et al. 2025; AGA Clinical Practice Guideline on the prevention and treatment of Hepatitis B Virus reactivation in at-risk individuals. Gastroenterology. 168(2):267–84. DOI: 10.1053/j.gastro.2024.11.008. PMID: 39863345.
79. Mikulska M, et al. 2025; Updated recommendations for the management of hepatitis B, C, and E virus infections in patients with haematological malignancies and those undergoing haematopoietic cell transplantation: recommendations from the 9th European Conference on Infections in Leukaemia (ECIL-9). Lancet Haematol. 12(5):e389–99. DOI: 10.1016/S2352-3026(25)00049-3. PMID: 40306834.
80. Los-Arcos I, et al. 2021; Recommendations for screening, monitoring, prevention, and prophylaxis of infections in adult and pediatric patients receiving CAR T-cell therapy: a position paper. Infection. 49(2):215–31. DOI: 10.1007/s15010-020-01521-5. PMID: 32979154. PMCID: PMC7518951.
81. Infante MS, et al. Outcomes and Management of the SARS-CoV2 Omicron Variant in Recipients of Hematopoietic Cell Transplantation and Chimeric Antigen Receptor T Cell Therapy. Transplant Cell Ther. 2024;30(1):116. e1–116 e12. 10.1016/j.jtct.2023.09.027 37806446 PMC11220618
82. Mushtaq MU, et al. Impact of SARS-CoV-2 in Hematopoietic Stem Cell Transplantation and Chimeric Antigen Receptor T Cell Therapy Recipients. Transplant Cell Ther 2021;27(9):796. e1-796 e7. 10.1016/j.jtct.2021.07.005 34256172 PMC8272625
83. Luque-Paz D, et al. 2022; The burden of SARS-CoV-2 in patients receiving chimeric antigen receptor T cell immunotherapy: everything to lose. Expert Rev Anti Infect Ther. 20(9):1155–62. DOI: 10.1080/14787210.2022.2101448. PMID: 35838042.
84. Kampouri E, Hill JA, Dioverti V. 2023; COVID-19 after hematopoietic cell transplantation and chimeric antigen receptor (CAR)-T-cell therapy. Transpl Infect Dis. 25(Suppl 1):e14144. DOI: 10.1111/tid.14144. PMID: 37767643.
85. Cheok KPL, et al. 2024; Mucormycosis after CD19 chimeric antigen receptor T-cell therapy: results of a US Food and Drug Administration adverse events reporting system analysis and a review of the literature. Lancet Infect Dis. 24(4):e256–65. DOI: 10.1016/S1473-3099(23)00563-7. PMID: 38310904.
86. Lin RY, et al. 2024; Incidence and outcomes of Cytomegalovirus reactivation after chimeric antigen receptor T-cell therapy. Blood Adv. 8(14):3813–22. DOI: 10.1182/bloodadvances.2024012922. PMID: 38838226. PMCID: PMC11298821.
87. Marquez-Algaba E, et al. 2022; Impact of cytomegalovirus replication in patients with aggressive B cell lymphoma treated with chimeric antigen receptor T cell therapy. Transplant Cell Ther. 28(12):851 e1. 851 e8. DOI: 10.1016/j.jtct.2022.09.007. PMID: 36221995.
88. Hayashino K, et al. 2025; Cytomegalovirus reactivation in patients with large B-cell lymphoma treated with chimeric antigen receptor T-cell therapy. Int J Hematol. 122(5):689–99. DOI: 10.1007/s12185-025-04023-y. PMID: 40526215. PMCID: PMC12572091.
89. Khan MA, et al. 2025; Predicators and outcomes of Cytomegalovirus reactivation in chimeric antigen receptor T-cell therapy: A systematic review. Clin Lymphoma Myeloma Leuk. 25(12):e1121–6. DOI: 10.1016/j.clml.2025.08.014. PMID: 40940256.

Fig. 1
Temporal evolution of toxicities, immune reconstitution, and infection risk after CAR T-cell therapy. A Schematic overview of the CAR T cell therapy timeline and clinical factors that may influence infection risk during each treatment phase. The treatment course included patient selection, CAR T-cell manufacturing (with or without bridging therapy), lymphodepleting chemotherapy, CAR T-cell infusion, and post-infusion care. Clinical variables, such as prior lines of therapy, prior infections, baseline hypogammaglobulinemia, and treatment-related toxicities, may contribute to infection susceptibility during the early, prolonged, and late phases after CAR T-cell therapy. The early phase (day − 6 to + 30) is characterized by grade ≥ 3 neutropenia/lymphopenia, CRS, ICANS, and other immune effector cell-associated toxicities. The prolonged phase (days + 30 to + 90) included persistent cytopenia, B-cell aplasia, hypogammaglobulinemia, delayed T-cell reconstitution, and delayed neurotoxicity. The late phase (> 90 days) includes sustained humoral deficits and secondary malignancies in addition to the complications listed in the earlier phases. Infectious complications can occur throughout the course of CAR T-cell therapy. B Immune reconstitution and phase-specific infection risk after CAR T cell therapy. Patients experience a hematologic nadir with profound neutropenia and lymphopenia during the early phase (< 30 days). In the prolonged phase (30–90 days). Neutrophil recovery occurs, B cell aplasia persists, and CD4 + T cell recovery remains delayed. In the late phase (> 90 days), persistent B-cell aplasia and hypogammaglobulinemia persist despite gradual T-cell recovery, contributing to ongoing susceptibility to bacterial, viral, and opportunistic infections. Red downward arrows indicate depletion, green upward arrows indicate recovery, and the red X symbols indicate persistent absence or impairment. Abbreviations: CAR, Chimeric antigen receptor; LOT, lines of therapy; CRS, cytokine release syndrome; ICANS, immune effector cell-associated neurotoxicity syndrome; IEC-HS, immune effector cell-associated hemophagocytic syndrome; CMV, cytomegalovirus; RSV, respiratory syncytial virus; HSV, herpes simplex virus; VZV, varicella zoster virus. Created with BioRender.com
br-61-30-f1.tif
Fig. 2
Differential humoral immune depletion following CD19- versus BCMA-directed CAR T-cell therapy. A Expression of CD19 and BCMA across the B cell differentiation pathway in the bone marrow and lymph nodes. CD19 is expressed from early B-cell precursors through mature and memory B cells but is absent in terminally differentiated long-lived PCs. In contrast, BCMA expression was enriched in plasmablasts, long-lived PCs, and myeloma cells, with minimal expression in the earlier B-cell stages. B Functional consequences of lineage-specific targeting. CD19-directed CAR-T cell therapy induces B cell aplasia through the depletion of CD19+ B cells; however, long-lived PCs may remain relatively preserved, allowing partial maintenance of antibody production and resulting in moderate reduction in immunoglobulin levels. In contrast, BCMA-directed CAR T-cell therapy directly depletes BCMA+ Plasma cells, including long-lived antibody-producing cells, within the bone marrow niche. This results in profound hypogammaglobulinemia, impaired pathogen-specific immunity, and an increased susceptibility to recurrent and opportunistic infections. Abbreviations: Pro B, pro-B cell; Pre B, pre-B cell; GC B, germinal center B cell; PC, plasma cell; BCMA, B-cell maturation antigen; PJP, Pneumocystis jirovecii pneumoniae; CMV, cytomegalovirus. Created with BioRender.com
br-61-30-f2.tif
Table 1
Summary of infection risk factors after CAR T-cell therapy
Category Risk factor Impact on infection risk
Treatment-related Lymphodepleting chemotherapy Early bacterial and fungal infections
Grade ≥ 3 CRS Increased risk of CMV reactivation and prolonged cytopenias
Prolonged or high-dose corticosteroids Independent predictor of bacterial, viral, and fungal infections
Use of ≥ 2 immunosuppressive agents (e.g., tocilizumab + anakinra) Opportunistic infections, CMV reactivation
Hematologic Prolonged or biphasic neutropenia ~ 60–80% in early phase, bacterial and invasive fungal infections
Delayed CD4 recovery (< 200/μL) Viral infections, Pneumocystis jirovecii pneumonia
CAR T construct CD19-directed CAR T B-cell aplasia, hypogammaglobulinemia
BCMA-directed CAR T Profound plasma cell depletion, severe humoral immunodeficiency
Patient-related Older age, extensive prior therapy, prior HSCT Delayed immune recovery, higher NRM
Baseline immunity Hypogammaglobulinemia, CMV seropositivity Recurrent infections, CMV reactivation (variable incidence in seropositive patients; higher with immunosuppression)

The risk factors shown represent commonly reported clinical variables associated with increased infection risk following CAR T-cell therapy, based on observational studies and registry analyses. Multiple factors frequently coexist in individual patients and may have additive effects on the susceptibility to infection

Abbreviations: CAR chimeric antigen receptor T-cell therapy, CRS cytokine release syndrome, CMV cytomegalovirus, HSCT hematopoietic stem cell transplantation, NRM nonrelapse mortality

Table 2
Summary of guideline recommendations from the european society for blood and marrow transplantation (EBMT) and the american society for transplantation and cellular therapy (ASTCT) for antimicrobial prophylaxis after CAR T-cell therapy
Domain EBMT [56] ASTCT [57]
Antibacterial prophylaxis Consider during neutropenia, extrapolated from HSCT practice; institutional resistance patterns should be considered Selective approach; fluoroquinolone prophylaxis reasonable during neutropenia; close monitoring acceptable
Antifungal prophylaxis (yeast) Fluconazole during neutropenia Fluconazole during neutropenia
Antifungal prophylaxis (mold) Not routinely recommended; consider in high-risk patients only with defined risk factors High-risk patients only with defined risk factors
HSV/VZV prophylaxis Universal prophylaxis; extrapolated from HSCT practice Universal prophylaxis; starting with lymphodepletion; prolonged duration
CMV prophylaxis Not recommended due to insufficient evidence Not recommended
PJP prophylaxis Recommended for all patients; ≥ 6 months; duration guided by immune recovery ≥ 6 months; continuation often guided by CD4 < 200 cells/μL
HBV reactivation prevention Mandatory antiviral prophylaxis for HBsAg +; prophylaxis or close DNA monitoring for anti-HBcAg + Mandatory prophylaxis for HBsAg +; prophylaxis or surveillance for anti-HBcAg +
IVIG replacement Selective use in hypogammaglobulinemia with recurrent or severe infections; routine prophylaxis not endorsed Selective use when IgG ≤ 400 mg/dL with infections; lower threshold in pediatric patients
Vaccination Delayed revaccination; extrapolated from HSCT; start ≥ 3–6 months post-CAR-T depending on immune recovery Staged revaccination: influenza/COVID-19 ~ 3 months; other inactivated ≥ 6 months; live ≥ 12 months with immune recovery

Recommendations were adapted from the current EBMT and ASTCT consensus guidelines. Specific prophylactic strategies may vary according to the institutional practices, patient risk factors, and local epidemiology

Abbreviations: EBMT European Society for Blood and Marrow Transplantation, ASTCT American Society for Transplantation and Cellular Therapy, HSCT herpes simplex virus, HSV hematopoietic stem cell transplantation, VZV, varicella zoster virus, CMV cytomegalovirus, PJP Pneumocystis jirovecii pneumonia, HBV hepatitis B virus, HBsAg hepatitis B surface antigen, anti-HBc, antibody to hepatitis B core antigen, IVIG intravenous immunoglobulin

Table 3
Practical antimicrobial prophylaxis and vaccination strategies after CAR T-cell therapy based on current guideline recommendations
Type of prophylaxis Indication Recommended strategy Duration
Antimicrobial prophylaxis
Antibacterial ANC < 500/μL Fluoroquinolone (if local resistance acceptable) Until neutrophil recovery
Antifungal (yeast) Neutropenia Fluconazole Until neutrophil recovery
Antifungal (mold) Prolonged neutropenia, prior IFI, prior allo-HCT, high-dose steroids, CRS/ICANS escalation Posaconazole, isavuconazole, or echinocandin (avoid voriconazole with ICANS) Through risk period; ≥ 1 month after steroid cessation
HSV/VZV All CAR T recipients Acyclovir or valacyclovir ≥ 1 year; often extended
PJP All CAR T recipients TMP-SMX (alternatives if intolerant) ≥ 6 months and CD4 > 200/μL
CMV Only High-risk patients PCR surveillance (no routine prophylaxis) 2–6 weeks post-infusion or up to 30 days after steroid cessation
Vaccination
Inactivated influenza vaccine All CAR T recipients Annual inactivated influenza vaccine Start ~ 3 months after CAR T; annually
COVID-19 vaccine All CAR T recipients Updated COVID-19 vaccination per current schedule Start ~ 3 months after CAR T
Pneumococcal vaccine All CAR T recipients Conjugate pneumococcal vaccine series Start ~ 6 months after CAR T
Routine inactivated vaccines Patients with immune recovery DTaP/Tdap, Hib, hepatitis A/B, IPV, HPV, RSV Start ~ 6 months after CAR T
Live vaccines Selected patients with immune reconstitution MMR, VZV or other live vaccines, if appropriate ≥ 24 months after CAR T

The table summarizes practical infection prevention strategies based on current international guidelines, including recommendations from the EBMT [56], ASTCT [57], and NCCN [16]. Specific antimicrobial regimens and vaccination schedules may be adapted according to local epidemiology, institutional protocols, and patientspecific risk factors

Abbreviations: ANC absolute neutrophil count, IFI invasive fungal infection, allo-HCT allogeneic hematopoietic cell transplantation, CRS cytokine release syndrome, ICANS immune effector cell–associated neurotoxicity syndrome, HSV herpes simplex virus, VZV varicella-zoster virus, PJP Pneumocystis jirovecii pneumonia, TMPSMX trimethoprim–sulfamethoxazole, CMV cytomegalovirus, CAR T chimeric antigen receptor T-cell, DTaP/Tdap diphtheria-tetanus-acellular pertussis vaccine, Hib Haemophilus influenzae type b vaccine, IPV inactivated poliovirus vaccine, HPV human papillomavirus, RSV respiratory syncytial virus, MMR measles-mumps-rubella

Table 4
Indications for IVIG After CAR T-cell therapy
CAR T construct Suggested IVIG indication Rationale
CD19-directed IgG < 400–600 mg/dL with recurrent or severe infections B-cell aplasia with variable recovery [16, 17, 75]
BCMA-directed (MM) IgG < 400 mg/dL (even without documented infection) Profound plasma cell depletion and sustained humoral deficiency [17, 32, 77]
Pediatric patients Lower threshold for initiation Higher infection susceptibility [74]
Discontinuation IgG normalization and infection resolution Avoid overtreatment [17, 75]

The suggested thresholds reflect commonly used clinical practice patterns reported in the literature and expert guidance. Decisions regarding IVIG initiation and discontinuation should consider the infection history, degree of hypogammaglobulinemia, and recovery of humoral immunity

Abbreviations: CAR T chimeric antigen receptor T-cell therapy, IVIG intravenous immunoglobulin, IgG immunoglobulin G, MM multiple myeloma

TOOLS
Similar articles