

Journal List > Blood Res > v.61 > 1516096201

Choi, Jang, and Jung: Allogeneic stem cell transplantation for myelofibrosis in the modern era: Single‑center outcomes with DIPSS risk stratification

Abstract

Purpose

To describe the post-transplant outcomes in patients with myelofibrosis stratified by the Dynamic International Prognostic Scoring System (DIPSS) risk at transplantation, and to identify clinical factors associated with overall survival (OS) after allogeneic hematopoietic stem cell transplantation (allo-HSCT).

Methods

We retrospectively analyzed the data of 42 patients with myelofibrosis who underwent allo-HSCT at Samsung Medical Center between 2014 and 2023. OS was estimated using the Kaplan–Meier method and compared using the log-rank test. Exploratory Cox proportional-hazard regression analyses were performed to assess independent associations with OS.

Results

At transplantation, 28 patients (66.7%) had Intermediate (Int-1/2) and 14 (33.3%) had High DIPSS risk. OS differed significantly by DIPSS risk group (log-rank P = 0.0034): the median OS was 15.2 months (95% confidence interval [CI], 7.2–NR months) in the Intermediate-risk group versus 6.4 months (95% CI, 3.3–35.1 months) in the High-risk group. All 14 patients in the High-risk group (100%) and 14 of 28 patients in the Intermediate-risk group (50%) died during follow-up. The 1-, 2-, and 3-year OS rates in the Intermediate- and High-risk groups were 57.1% vs. 28.6%, 50.0% vs. 14.3%, and 50.0% vs. 7.1%, respectively. In an exploratory multivariable analysis adjusted for hematopoietic cell transplantation-specific comorbidity index and donor type, DIPSS High-risk disease remained independently associated with inferior OS (adjusted hazard ratio [HR], 2.91; 95% CI, 1.27–6.63; P = 0.011). No other clinical variable, including age (≥ 60 vs. < 60 years; P = 0.16 by log-rank), achieved statistical significance.

Conclusion

DIPSS High-risk disease at transplantation was associated with uniformly poor post-transplant survival in this single-center cohort. These hypothesis-generating findings underscore the importance of transplant timing before progression to high-risk disease, and warrant validation in larger multicenter studies.

Introduction

Myelofibrosis (MF) is a rare Philadelphia chromosome– negative myeloproliferative neoplasm with an annual incidence of ~ 0.5 per 100,000 and a median age of approximately 65 years at diagnosis [1, 2]. It is characterized by progressive bone marrow fibrosis, extramedullary hematopoiesis with splenomegaly, constitutional symptoms, and a risk of leukemic transformation [1, 3]. The prognosis is poor in comparison with other myeloproliferative neoplasms, with median survival ranging from > 10 years in low-risk patients to 2–3 years in highrisk patients [2, 4]. The pathogenesis of MF involves the clonal proliferation of hematopoietic stem cells, frequently with Janus kinase 2 (JAK2), calreticulin (CALR), or myeloproliferative leukemia protein (MPL) mutations, and an altered bone marrow microenvironment that produces pro-fibrotic cytokines such as transforming growth factor beta 1 (TGF-β1) and bone morphogenetic protein 2 (BMP-2) [5].
Risk stratification of patients with MF is most commonly performed using the Dynamic International Prognostic Scoring System (DIPSS), which incorporates age, hemoglobin level, leukocyte count, peripheral blasts, and constitutional symptoms, with an anemia-weighted double score [4]. High-molecular-risk (HMR) mutations (e.g., ASXL transcriptional regulator 1 [ASXL1], serineand arginine-rich splicing factor 2 [SRSF2], enhancer of zeste 2 polycomb repressive complex 2 subunit [EZH2], and isocitrate dehydrogenase 1 and 2 [IDH1/2]) further worsen the prognosis [6]. Treatment is risk-adapted. Low-risk or asymptomatic patients may be observed, while intermediate-2, high-risk, or symptomatic patients typically receive Janus kinase (JAK) inhibitors such as ruxolitinib [7], fedratinib [8], pacritinib [9], or momelotinib [10]. These agents improve symptoms and splenomegaly but rarely achieve molecular remission or significantly extend survival. Allogeneic hematopoietic stem cell transplantation (allo-HSCT) remains the only potential curative therapy [11].
Recent EBMT/ELN consensus recommendations emphasize allo-HSCT as the only potentially curative option and support its consideration in medically fit patients with Intermediate-2 or High-risk MF (and selected patients showing Intermediate-1 disease with additional adverse features) while integrating comorbidity and molecular risk assessment into decision-making [12]. Transplant-specific prognostic tools such as the Myelofibrosis Transplant Scoring System (MTSS) have been proposed to refine post-transplant risk estimation [13]. Notably, the current consensus suggests that chronological age alone should not constitute an absolute contraindication and that reduced-intensity conditioning (RIC) may expand the feasibility of HSCT in selected older patients [14, 15]. In this study, we retrospectively described the outcomes of 42 patients with myelofibrosis who underwent allo-HSCT at a single center between 2014 and 2023. We focused on the pretransplant DIPSS risk category as the primary stratification variable and evaluated age and other transplant- and disease-related factors in secondary exploratory analyses.

Materials and methods

Patient selection and data collection

We performed a retrospective cohort study of patients with MF who underwent allo-HSCT at Samsung Medical Center between 2014 and 2023. A total of 42 patients were identified through the institutional transplant database, including those with primary myelofibrosis (PMF), post-polycythemia vera myelofibrosis (post-PV MF), and post-essential thrombocythemia myelofibrosis (post-ET MF). This study was conducted in accordance with the ethical principles of the Declaration of Helsinki (revised in 2013) and Korean Good Clinical Practice guidelines. Approval was obtained from the Institutional Review Board of Samsung Medical Center (IRB No. 2025–11–108), and the requirement for individual informed consent was waived. Patients were identified using only anonymized patient numbers, and personally identifiable information was kept confidential in accordance with the IRB protocol.

Definitions of variables and outcomes

The examined variables included sex, MF subtype, and donor type (matched sibling donor [MSD], matched unrelated donor [MUD], or haploidentical donor). Conditioning intensity (myeloablative conditioning [MAC] vs. RIC), DIPSS risk category at transplantation, and the hematopoietic cell transplantation-specific comorbidity index (HCT-CI; < 3 vs. ≥ 3) were incorporated to address potential confounders. Clinical factors, including pretransplant spleen size, constitutional symptoms, and JAK inhibitor exposure and response, were also recorded. The driver mutation status (JAK2, CALR, MPL) was included, and next-generation sequencing (NGS) results were incorporated where available.
The primary outcome was overall survival (OS) after transplantation, stratified according to DIPSS risk. OS was calculated from the date of HSCT to the date of death from any cause or the date of the last follow-up, with surviving patients censored at the last contact.
Secondary analyses evaluated OS by age group (≥ 60 vs. < 60 years) and other factors, including donor type, conditioning regimen, HCT-CI, driver mutation status, and spleen size. The DIPSS component variables were not tabulated by risk group to avoid circularity.

Statistical analysis

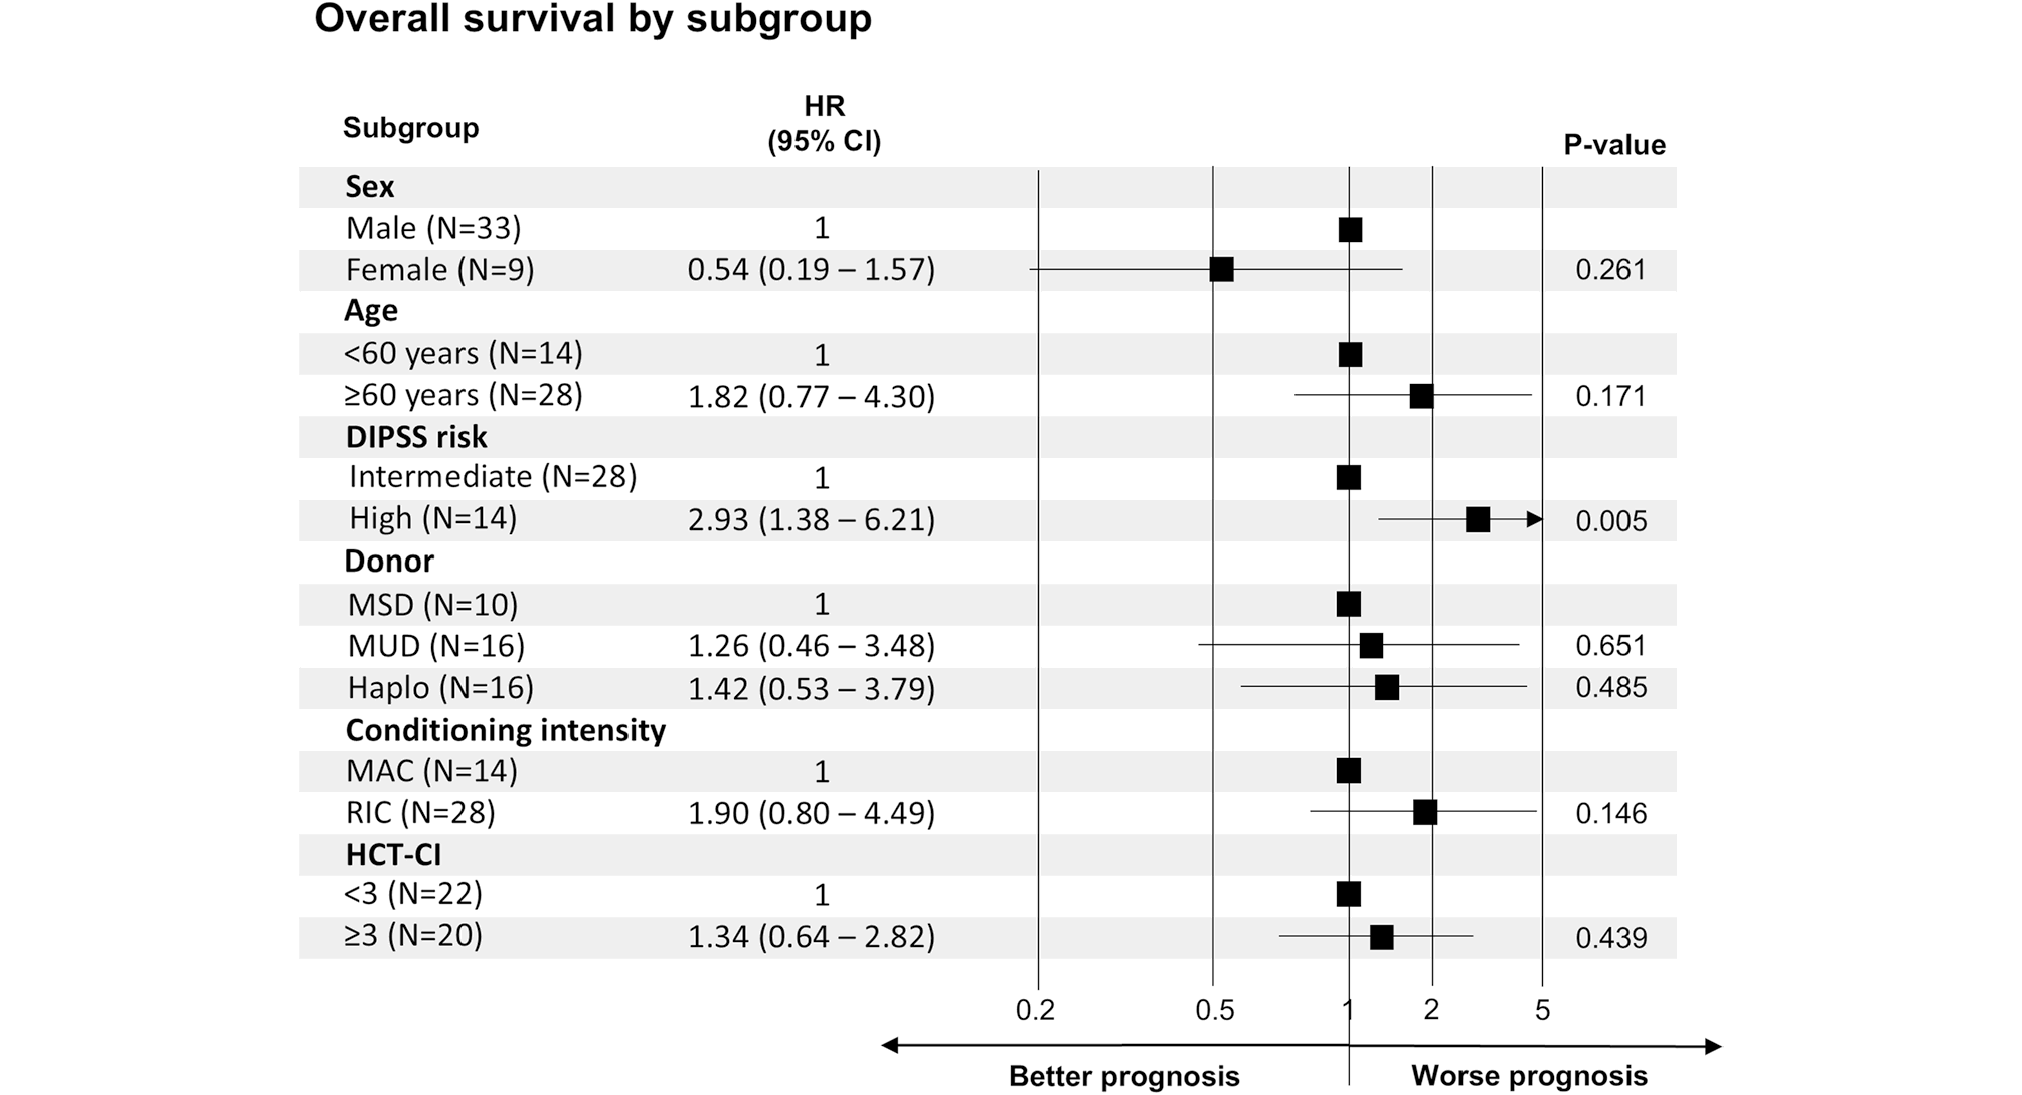
Survival curves were estimated using the Kaplan–Meier method and compared using the log-rank test. Categorical variables were compared using the chi-squared test or Fisher’s exact test, as appropriate. Given the limited sample size and inherent baseline imbalances, all analyses were considered exploratory, and P-values were interpreted with caution. Exploratory Cox proportional-hazard regression was performed for the sensitivity analysis (univariable estimates in Fig. 2; multivariable model in Supplementary Table 1). Advanced statistical techniques (e.g., propensity-score matching and competing-risk models) were not used given the limited number of cases and events. A sensitivity analysis restricted to patients who received RIC was performed to address potential confounding by the conditioning intensity. Analyses were performed using R version 4.2.2 (R Foundation for Statistical Computing, Vienna, Austria).

Results

Baseline characteristics

Between 2014 and 2023, 42 patients with MF underwent allo-HSCT. At transplantation, 28 patients (66.7%) had Intermediate (Int-1/2) DIPSS risk, and 14 (33.3%) had High DIPSS risk (Table 1). The Intermediate-risk group was predominantly male (71.4%) and mostly consisted of patients with PMF (82.1%). Donor types included MSDs (32.1%), haploidentical donors (28.6%), and MUDs (39.3%). The High-risk group was also predominantly male (92.9%) with a higher proportion of haploidentical donors (57.1%). All patients received busulfan plus fludarabine-based conditioning; BuFlu2 was used in all High-risk patients, whereas BuFlu4 was used in 50.0% of Intermediate-risk patients. An HCT-CI ≥ 3 was observed in 42.9% and 57.1% of Intermediate- and High-risk patients, respectively. Spleen size categories and prior ruxolitinib exposure were broadly similar between the groups (Table 1).

OS in relation to the DIPSS risk classification and age

The OS was significantly lower in the High-risk group (log-rank P = 0.0034) (Fig. 1). The median OS was 15.2 months (95% confidence interval [CI], 7.2 months–NR) in the Intermediate-risk group and 6.4 months (95% CI, 3.3–35.1 months) in the High-risk group. All 14 High-risk patients (100%) and 14 of 28 Intermediaterisk patients (50%) died during follow-up. The 1-, 2-, and 3-year OS rates in the High- and Intermediate-risk groups were 57.1% vs. 28.6%, 50.0% vs. 14.3%, and 50.0% vs. 7.1%, respectively. A swimmer plot illustrating patientlevel follow-up in relation to the DIPSS risk classification is shown in Supplementary Fig. 1. In the age-based comparison (≥ 60 vs. < 60 years), the median OS was 8.0 months (95% CI, 5.4–36.3 months) in the ≥ 60-year group and 15.2 months (95% CI, 6.3 months–NR) in the < 60-year group (P = 0.16) (Supplementary Fig. 2).

Exploratory subgroup and multivariable analyses

The results of the univariable subgroup analyses are presented in Fig. 2. DIPSS High-risk disease showed the strongest association with inferior OS (hazard ratio [HR], 2.93; 95% CI, 1.38–6.21); all other subgroup estimates were not statistically significant. In the exploratory multivariable Cox regression analysis (Supplementary Table 1), DIPSS High-risk disease remained independently associated with inferior OS after adjustment for HCT-CI and donor type (adjusted HR, 2.91; 95% CI, 1.27–6.63; P = 0.011), whereas age ≥ 60 years was not significant (adjusted HR, 1.65; 95% CI, 0.66–4.15; P = 0.30). These models are presented as hypotheses-generating and should not be interpreted as confirmatory.

Sensitivity analysis restricted to RIC

Because all patients with DIPSS High-risk disease received RIC (BuFlu2), while 50% of patients with Intermediate-risk disease received MAC (BuFlu4), a sensitivity analysis with the cohort restricted to patients who received uniform RIC conditioning (n = 28: 14 Intermediate, 14 High) was performed. The prognostic separation by DIPSS risk was preserved: the 3-year OS was 50.0% (95% CI, 22.9%–72.2%) in the Intermediate group versus 7.1% (95% CI, 0.5%–27.5%) in the High-risk group (logrank P = 0.018). The Cox HR for DIPSS High versus Intermediate risk in this subset was 2.88 (95% CI, 1.15–7.22; P = 0.024). The median follow-up was 60.5 months (Supplementary Fig. 3).

Driver mutation and spleen size

No significant differences in OS were observed in relation to the driver mutation status (log-rank P = 0.10) (Supplementary Fig. 4) or splenic size category before transplantation (log-rank P = 0.85) (Supplementary Fig. 5). Spleen size was categorized by the longest diameter (< 22 vs. ≥ 22 cm); one patient with a prior splenectomy was excluded from this analysis.

Cause of death

Overall, 28 patients died during the follow-up. Infection was the most frequent cause of death in both groups (intermediate, 9/28 [32.1%]; high, 6/14 [42.9%]), followed by disease progression, and graft-versus-host disease (GVHD) (Table 2). Among the 13 patients who died within the first 6 months after HSCT, 9 (69.2%) died of infection, while 6 of 15 (40.0%) died at ≥ 6 months. Because the post-transplant disease status near the time of death was not uniformly available, deaths were not formally attributed to relapse-related or non-relapse mortality.

Discussion

In this single-center retrospective cohort study, DIPSS risk at transplantation was the only clinical variable significantly associated with post-transplant OS. All 14 patients with DIPSS High-risk disease died during follow-up after transplantation, with a median OS of only 6.4 months, while the corresponding value was 15.2 months in the Intermediate-risk group. In the exploratory multivariable models, DIPSS High-risk disease was independently associated with inferior OS (adjusted HR, 2.91; P = 0.011), whereas no other variable, including age, HCT-CI, and donor type, reached statistical significance. Notably, all patients with DIPSS High-risk disease were aged ≥ 60 years, precluding the reliable separation of age and disease-risk effects. These findings support the concept of a therapeutic window for allo-HSCT in MF, and suggest that transplantation should ideally be pursued before progression to DIPSS High-risk disease [16, 17].
Consistent with the updated EBMT/ELN recommendations, risk stratification is central to transplant decision-making in MF [12]. In our cohort, DIPSS High-risk disease was associated with inferior OS in both unadjusted and exploratory adjusted analyses. Transplantspecific scoring systems such as the MTSS may further refine post-transplant risk estimation [13]. However, the MTSS requires platelet count and performance status data that were not systematically captured in our retrospective dataset, precluding its calculation in the present study. Furthermore, comprehensive molecular annotation was limited because NGS data were available for only 13 of the 42 patients (31.0%), which precluded the evaluation of HMR features at the cohort level. Integrated clinical-molecular scoring systems such as MIPSS70 [18] incorporate HMR mutations that were not systematically captured in our cohort. In an exploratory analysis restricted to the NGS-tested subset, the presence of ≥ 2 HMR mutations appeared to be associated with poor outcomes, although the small sample size precluded formal statistical testing. Future studies with comprehensive molecular annotations are warranted to determine whether molecular risk features refine the prognostic impact of the DIPSS category in a transplant setting [19].
Conditioning intensity differed between the two groups: all patients with DIPSS High-risk disease received RIC (BuFlu2), whereas 50% of those with DIPSS Intermediate-risk disease received MAC (BuFlu4). This allocation reflects risk-adapted clinical practice, wherein patients with a greater disease burden are preferentially offered RIC to reduce early transplant-related toxicity. Although conditioning intensity can influence posttransplant outcomes in MF [20, 21], a sensitivity analysis restricted to the RIC-only subset (n = 28) preserved the prognostic separation between the DIPSS risk groups (3-year OS: 50.0% vs. 7.1%; log-rank P = 0.018; Cox HR: 2.88, 95% CI 1.15–7.22), indicating that the observed survival difference was not primarily driven by differential conditioning intensity. Nevertheless, the RIC-only subset remained small and non-randomized, and residual confounding from unmeasured factors cannot be fully excluded.
Driver mutation status and spleen size were not significantly associated with OS in our cohort, likely reflecting their limited statistical power [2225]. Rather than performing splenectomy or splenic irradiation solely to reduce spleen size [26, 27], JAK inhibitors can be reasonably used primarily as a pretransplant bridging therapy, with splenic reduction as a secondary benefit [28]. Alternative approaches should be considered for patients who do not respond to JAK inhibitors [29, 30].
Infection was the leading cause of death in both DIPSS risk groups, with nine of 13 early deaths (within 6 months) being infection-related (69.2%). All patients underwent rabbit anti-human thymocyte globulin (rATG)-based conditioning, which is known to delay immune reconstitution and increase susceptibility to opportunistic infections. The higher proportion of haploidentical donors in the High-risk group (57.1% vs. 28.6%) may have further contributed to the risk of infection, given the additional immunosuppression required in an HLA-mismatched setting. These observations underscore the need for intensified infection surveillance and antimicrobial prophylaxis strategies, particularly in the first six months after HSCT. However, our dataset did not capture specific pathogens or infection sites, and the absence of competing-risk analyses limited further interpretation.
Our study had several limitations. The small sample size and retrospective single-center design limited the statistical power and generalizability of the findings. The age-stratified comparisons should be interpreted with caution because the conditioning regimen, JAK inhibitor use, and DIPSS risk were not uniformly distributed among the age groups. The only statistically significant association observed was the relationship between OS and DIPSS risk category; all other comparisons should be regarded as hypothesis-generating. When transplantation is considered in patients with DIPSS High-risk disease, pretransplant risk optimization, including JAK inhibitor bridging therapy, may be reasonable. If meaningful disease-risk reduction cannot be achieved, nontransplant approaches and supportive care should be discussed regardless of the patient’s age.

Conclusion

In this single-center retrospective analysis, DIPSS Highrisk disease at transplantation was associated with uniformly poor post-transplant survival, with 100% mortality even in patients who underwent allo-HSCT. These findings highlight the importance of transplant timing and suggest that allo-HSCT should be considered before progression to DIPSS High-risk disease. Given the limitations of this small retrospective cohort, these hypothesis-generating observations warrant validation in multicenter studies that incorporate integrated clinicalmolecular transplant risk models.

Appendix

Supplementary Information

The online version contains supplementary material available at https://doi.org/10.1007/s44313-026-00142-5.

Notes

Authors’ contributions

DHC was responsible for study design, data collection, statistical analysis, data interpretation, and manuscript writing. JHJ contributed to data collection, data interpretation, and critical review. CWJ was responsible for study conception and design, data interpretation, critical revision, and supervision. All authors reviewed and approved the final manuscript.

Funding

This study received no external funding.

Data availability

The data underlying this article are available from the corresponding author on reasonable request, subject to institutional and ethical regulations.

Declarations

Ethics approval and consent to participate

This study was conducted in accordance with the ethical principles of the Declaration of Helsinki (as revised in 2013). Approval was obtained from the Institutional Review Board of Samsung Medical Center (IRB No. 2025–11-108). The requirement for individual informed consent was waived by the IRB given the retrospective nature of the study.

Consent for publication

Not applicable.

Competing interests

The authors declare no competing interests.

Publisher’s Note

Springer Nature remains neutral with regard to jurisdictional claims in published maps and institutional affiliations.

REFERENCES

1. Mora B, Bucelli C, Cattaneo D, Bellani V, Versino F, Barbullushi K, et al. 2024; Prognostic and Predictive Models in Myelofibrosis. Curr Hematol Malig Rep. 19(5):223–35. https://doi.org/10.1007/s11899-024-00739-6. DOI: 10.1007/s11899-024-00739-6. PMID: 39179882. PMCID: PMC11416430.
2. Martino M, Pitea M, Sgarlata A, Delfino IM, Cogliandro F, Scopelliti A, et al. 2024; Treatment Strategies Used in Treating Myelofibrosis: State of the Art. Hematol Rep. 16(4):698–713. https://doi.org/10.3390/hematolrep16040067. DOI: 10.3390/hematolrep16040067. PMID: 39584924. PMCID: PMC11587016. PMID: 9f0d67e055a94fe2973a05585c1e2da4.
3. Leiva O, Ng SK, Chitalia S, Balduini A, Matsuura S, Ravid K. 2017; The role of the extracellular matrix in primary myelofibrosis. Blood Cancer J. 7(2):e525. https://doi.org/10.1038/bcj.2017.6. DOI: 10.1038/bcj.2017.6. PMID: 28157219. PMCID: PMC5386340.
4. Passamonti F, Cervantes F, Vannucchi AM, Morra E, Rumi E, Cazzola M, et al. 2010; Dynamic International Prognostic Scoring System (DIPSS) predicts progression to acute myeloid leukemia in primary myelofibrosis. Blood. 116(15):2857–8. https://doi.org/10.1182/blood-2010-06-293415. DOI: 10.1182/blood-2010-06-293415. PMID: 20947690.
5. Martinaud C, Desterke C, Konopacki J, Pieri L, Torossian F, Golub R, et al. 2015; Osteogenic Potential of Mesenchymal Stromal Cells Contributes to Primary Myelofibrosis. Cancer Res. 75(22):4753–65. https://doi.org/10.1158/0008-5472.CAN-14-3696. DOI: 10.1158/0008-5472.CAN-14-3696. PMID: 26404004.
6. Tefferi A, Nicolosi M, Mudireddy M, Lasho TL, Gangat N, Begna KH, et al. 2018; Revised cytogenetic risk stratification in primary myelofibrosis: analysis based on 1002 informative patients. Leukemia. 32(5):1189–99. https://doi.org/10.1038/s41375-018-0018-z. DOI: 10.1038/s41375-018-0018-z. PMID: 29472717. PMCID: PMC5940654.
7. Verstovsek S, Mesa RA, Gotlib J, Levy RS, Gupta V, DiPersio JF, et al. 2012; A double-blind, placebo-controlled trial of ruxolitinib for myelofibrosis. N Engl J Med. 366(9):799–807. https://doi.org/10.1056/NEJMoa1110557. DOI: 10.1056/NEJMoa1110557. PMID: 22375971. PMCID: PMC4822164.
8. Pardanani A, Harrison C, Cortes JE, Cervantes F, Mesa RA, Milligan D, et al. 2015; Safety and Efficacy of Fedratinib in Patients With Primary or Secondary Myelofibrosis: A Randomized Clinical Trial. JAMA Oncol. 1(5):643–51. https://doi.org/10.1001/jamaoncol.2015.1590. DOI: 10.1001/jamaoncol.2015.1590. PMID: 26181658.
9. Mascarenhas J, Hoffman R, Talpaz M, Gerds AT, Stein B, Gupta V, et al. 2018; Pacritinib vs Best Available Therapy, Including Ruxolitinib, in Patients With Myelofibrosis: A Randomized Clinical Trial. JAMA Oncol. 4(5):652–9. https://doi.org/10.1001/jamaoncol.2017.5818. DOI: 10.1001/jamaoncol.2017.5818. PMID: 29522138. PMCID: PMC5885169.
10. Mesa RA, Kiladjian JJ, Catalano JV, Devos T, Egyed M, Hellmann A, et al. 2017; SIMPLIFY-1: A Phase III Randomized Trial of Momelotinib Versus Ruxolitinib in Janus Kinase Inhibitor-Naive Patients With Myelofibrosis. J Clin Oncol. 35(34):3844–50. https://doi.org/10.1200/JCO.2017.73.4418. DOI: 10.1200/JCO.2017.73.4418. PMID: 28930494. PMCID: PMC6553796.
11. Ranalli P, Natale A, Guardalupi F, Santarone S, Canto C, La Barba G, et al. 2024; Myelofibrosis and allogeneic transplantation: critical points and challenges. Front Oncol. 14:1396435. https://doi.org/10.3389/fonc.2024.1396435. DOI: 10.3389/fonc.2024.1396435. PMID: 38966064. PMCID: PMC11222377. PMID: 2d24ce92ee67458abc78afed5a7076ad.
12. Kroger N, Bacigalupo A, Barbui T, Ditschkowski M, Gagelmann N, Griesshammer M, et al. 2024; Indication and management of allogeneic haematopoietic stem-cell transplantation in myelofibrosis: updated recommendations by the EBMT/ELN International Working Group. Lancet Haematol. 11(1):e62–74. https://doi.org/10.1016/S2352-3026(23)00305-8. DOI: 10.1016/S2352-3026(23)00305-8. PMID: 38061384.
13. Gagelmann N, Ditschkowski M, Bogdanov R, Bredin S, Robin M, Cassinat B, et al. 2019; Comprehensive clinical-molecular transplant scoring system for myelofibrosis undergoing stem cell transplantation. Blood. 133(20):2233–42. https://doi.org/10.1182/blood-2018-12-890889. DOI: 10.1182/blood-2018-12-890889. PMID: 30760453.
14. Fauble V, Leis J, Mesa RA. 2012; Allogeneic stem cell transplant for myelofibrosis patients over age 60: likely impact of the JAK2 inhibitors. Leuk Suppl. 1(Suppl 1):S2–7. https://doi.org/10.1038/leusup.2012.2. DOI: 10.1038/leusup.2012.2. PMID: 27175229. PMCID: PMC4851182.
15. Daghia G, Zabelina T, Zeck G, von Pein UM, Christopeit M, Wolschke C, et al. 2019; Allogeneic stem cell transplantation for myelofibrosis patients aged >/=65 years. Eur J Haematol. 103(4):370–8. https://doi.org/10.1111/ejh.13294. DOI: 10.1111/ejh.13294. PMID: 31306511.
16. Ditschkowski M, Elmaagacli AH, Trenschel R, Gromke T, Steckel NK, Koldehoff M, et al. 2012; Dynamic International Prognostic Scoring System scores, pre-transplant therapy and chronic graft-versus-host disease determine outcome after allogeneic hematopoietic stem cell transplantation for myelofibrosis. Haematologica. 97(10):1574–81. https://doi.org/10.3324/haematol.2011.061168. DOI: 10.3324/haematol.2011.061168. PMID: 22491742. PMCID: PMC3487559. PMID: e5d5175cb3d3475c892f537004143bf3.
17. Cooper JP, Scott BL. 2018; Allogeneic transplantation for myelofibrosis with adverse risk karyotype: attack on the clones? Am J Hematol. 93(5):603–4. https://doi.org/10.1002/ajh.25078. DOI: 10.1002/ajh.25078. PMID: 29498109.
18. Ali H, Aldoss I, Yang D, Mokhtari S, Khaled S, Aribi A, et al. 2019; MIPSS70+ v2.0 predicts long-term survival in myelofibrosis after allogeneic HCT with the Flu/Mel conditioning regimen. Blood Adv. 3(1):83–95. https://doi.org/10.1182/bloodadvances.2018026658. DOI: 10.1182/bloodadvances.2018026658. PMID: 30622146. PMCID: PMC6325305.
19. Luque Paz D, Gagelmann N, Benajiba L, Riou J, Salit R, Orvain C, et al. 2025; Role of molecular alterations in transplantation decisions for patients with primary myelofibrosis. Blood Adv. 9(4):797–807. https://doi.org/10.1182/bloodadvances.2024014368. DOI: 10.1182/bloodadvances.2024014368. PMID: 39561372. PMCID: PMC11869958. PMID: 8d0a5ff68a354f0d8886948b4872c1f0.
20. Murthy GSG, Kim S, Estrada-Merly N, Abid MB, Aljurf M, Assal A, et al. 2023; Association between the choice of the conditioning regimen and outcomes of allogeneic hematopoietic cell transplantation for myelofibrosis. Haematologica. 108(7):1900–8. https://doi.org/10.3324/haematol.2022.281958. DOI: 10.3324/haematol.2022.281958. PMID: 36779595. PMCID: PMC10316233. PMID: 3607fa3e9937487db3f85032af240a0d.
21. Machherndl-Spandl S, Hannouf S, Nikoloudis A, Zach O, Strassl I, Kaynak E, et al. 2024; Improved outcomes in myelofibrosis after allogeneic stem-cell transplantation in the era of Ruxolitinib pretreatment and intensified conditioning regimen-single-center analysis. Cancers (Basel). 16(19):3257. https://doi.org/10.3390/cancers16193257. DOI: 10.3390/cancers16193257. PMID: 39409879. PMCID: PMC11482566.
22. Tefferi A, Lasho TL, Finke CM, Knudson RA, Ketterling R, Hanson CH, et al. 2014; CALR vs JAK2 vs MPL-mutated or triple-negative myelofibrosis: clinical, cytogenetic and molecular comparisons. Leukemia. 28(7):1472–7. https://doi.org/10.1038/leu.2014.3. DOI: 10.1038/leu.2014.3. PMID: 24402162.
23. Schulze S, Stengel R, Jaekel N, Wang SY, Franke GN, Roskos M, et al. 2019; Concomitant and noncanonical JAK2 and MPL mutations in JAK2V617Fand MPLW515 L-positive myelofibrosis. Genes Chromosomes Cancer. 58(11):747–55. https://doi.org/10.1002/gcc.22781. DOI: 10.1002/gcc.22781. PMID: 31135094.
24. Polverelli N, Mauff K, Kroger N, Robin M, Beelen D, Beauvais D, et al. 2021; Impact of spleen size and splenectomy on outcomes of allogeneic hematopoietic cell transplantation for myelofibrosis: a retrospective analysis by the chronic malignancies working party on behalf of European Society for Blood and Marrow Transplantation (EBMT). Am J Hematol. 96(1):69–79. https://doi.org/10.1002/ajh.26020. DOI: 10.1002/ajh.26020. PMID: 33064301.
25. Kroger N, Sbianchi G, Sirait T, Wolschke C, Beelen D, Passweg J, et al. 2021; Impact of prior JAK-inhibitor therapy with ruxolitinib on outcome after allogeneic hematopoietic stem cell transplantation for myelofibrosis: a study of the CMWP of EBMT. Leukemia. 35(12):3551–60. https://doi.org/10.1038/s41375-021-01276-4. DOI: 10.1038/s41375-021-01276-4. PMID: 34023851. PMCID: PMC8632691.
26. Gagelmann N, Hobbs GS, Campodonico E, Helbig G, Novak P, Schroeder T, et al. 2024; Splenic irradiation for myelofibrosis prior to hematopoietic cell transplantation: a global collaborative analysis. Am J Hematol. 99(5):844–53. https://doi.org/10.1002/ajh.27252. DOI: 10.1002/ajh.27252. PMID: 38357714.
27. Helbig G, Wieczorkiewicz-Kabut A, Markiewicz M, Krzemien H, Wojciak M, Bialas K, et al. 2019; Splenic irradiation before allogeneic stem cell transplantation for myelofibrosis. Med Oncol. 36(2):16. https://doi.org/10.1007/s12032-019-1245-5. DOI: 10.1007/s12032-019-1245-5. PMID: 30617767. PMCID: PMC6326000.
28. Polverelli N, Hernandez-Boluda JC, Czerw T, Barbui T, D'Adda M, Deeg HJ, et al. 2023; Splenomegaly in patients with primary or secondary myelofibrosis who are candidates for allogeneic hematopoietic cell transplantation: a position paper on behalf of the Chronic Malignancies Working Party of the EBMT. Lancet Haematol. 10(1):e59–70. https://doi.org/10.1016/S2352-3026(22)00330-1. DOI: 10.1016/S2352-3026(22)00330-1. PMID: 36493799.
29. Harrison CN, Kiladjian JJ, Koschmieder S, Passamonti F. 2024; Myelofibrosis: current unmet needs, emerging treatments, and future perspectives. Cancer. 130(12):2091–7. https://doi.org/10.1002/cncr.35244. DOI: 10.1002/cncr.35244. PMID: 38373144.
30. Reynolds SB, Pettit K. 2022; New approaches to tackle cytopenic myelofibrosis. Hematology Am Soc Hematol Educ Program. 2022(1):235–44. https://doi.org/10.1182/hematology.2022000340. DOI: 10.1182/hematology.2022000340. PMID: 36485113. PMCID: PMC9820710.

Fig. 1
Overall survival categorized by DIPSS risk at transplantation in patients who underwent allogeneic HSCT. Kaplan–Meier curves for the DIPSS Intermediate- (Intermediate-1/2 combined; n = 28) and High-risk (n = 14) groups. The median OS was 15.2 months (95% CI, 7.2–NR) in the Intermediate-risk group and 6.4 months in the High-risk group (log-rank P = 0.0034). Numbers at risk are shown below the x-axis
br-61-27-f1.tif
Fig. 2
Univariable subgroup analysis of overall survival after allogeneic HSCT. Hazard ratios (HRs) with 95% confidence intervals are shown for pre-specified clinical variables (DIPSS risk, sex, age, donor type, conditioning intensity, and HCT-CI). All analyses are exploratory; confidence intervals are wide due to the limited sample size, and results should be interpreted as hypothesis-generating only
br-61-27-f2.tif
Table 1
Baseline characteristics of 42 myelofibrosis patients undergoing allogeneic HSCT, stratified by DIPSS risk group at transplantation (intermediate [Int-1/2] vs high)
Characteristic Intermediate (n = 28) High (n = 14) P-value
Sex
Male 20 (71.4%) 13 (92.9%) 0.23
Female 8 (28.6%) 1 (7.1%)
Types of myelofibrosis
PMF 23 (82.1%) 9 (64.3%) 0.337
Post ET MF 3 (10.7%) 4 (28.6%)
Post PV MF 2 (7.1%) 1 (7.1%)
Driver mutation
TN 7 (25.0%) 2 (14.3%) 0.36
JAK2 13 (46.4%) 9 (64.3%)
CALR 4 (14.3%) 0 (0.0%)
MPL 3 (10.7%) 1 (7.1%)
Unknown 1 (3.6%) 2 (14.3%)
Donor type
Matched sibling donor 9 (32.1%) 1 (7.1%) 0.106
Haploidentical 8 (28.6%) 8 (57.1%)
Matched unrelated donor 11 (39.3%) 5 (35.7%)
Conditioning regimen
BuFlu4 14 (50.0%) 0 (0.0%) 0.001
BuFlu2 14 (50.0%) 14 (100.0%)
HCT-CI score
< 3 16 (57.1%) 6 (42.9%) 0.515
≥ 3 12 (42.9%) 8 (57.1%)
NGS available
Yes 9 (32.1%) 4 (28.6%) 1.0
No 19 (67.9%) 10 (71.4%)
Spleen size before HSCT
Longest diameter < 22 cm 19 (67.9%) 9 (64.3%) 0.715
Longest diameter ≥ 22 cm 8 (28.6%) 5 (35.7%)
Splenectomy 1 (3.6%) 0 (0.0%)
Previous ruxolitinib exposure
Yes 18 (64.3%) 11 (78.6%) 0.485
No 10 (35.7%) 3 (21.4%)
Response to JAK inhibitor among exposed (descriptive)
Any response 16 (88.9%) 8 (72.7%) 0.339
Disease progression 2 (11.1%) 3 (27.3%)

All patients received busulfan plus fludarabine-based conditioning regimens

Comparisons between groups are exploratory; p-values should be interpreted with caution

DIPSS component variables (age, hemoglobin, leukocyte count, peripheral blasts, and constitutional symptoms) were not tabulated by risk group to avoid circularity

Abbreviations: ET Essential thrombocythemia, MF Myelofibrosis, PV Polycythemia vera, JAK2 Janus kinase 2, CALR Calreticulin, MPL Myeloproliferative leukemia protein, Bu Busulfan, Flu Fludarabine, HCT-CI Hematopoietic Cell Transplantation–Comorbidity Index, NGS Next-generation sequencing, HSCT Hematopoietic stem cell transplantation

Table 2
Causes of death stratified by DIPSS risk group at transplantation
Causes of death Intermediate (N = 28) High (N = 14)
Number of deaths 14 (50.0%) 14 (100.0%)
Infection 9 (32.1%) 6 (42.9%)
Disease progression 2 (7.1%) 3 (21.4%)
GVHD 1 (3.6%) 3 (21.4%)
Bleeding (Engraftment failure) 1 (3.6%) 0 (0.0%)
Unknown 1 (3.6%) 2 (14.3%)
TOOLS
Similar articles