Journal List > Blood Res > v.61 > 1516094461

Lee, Lin, Tsai, Hsu, Yao, Tien, Lo, Chang, Kuo, Yu, Liu, Yuan, Tseng, Peng, Yao, Ko, Tien, Hou, and Chou: Prognostic impact of lymphocyte to monocyte ratio in patients with myelodysplastic neoplasms/syndromes

Abstract

Purpose

Myelodysplastic syndromes/neoplasms (MDS) represent a heterogeneous group of clonal hematopoietic disorders with variable prognosis. While several risk models exist, the prognostic role of immune-related biomarkers remains unclear. This study aimed to determine whether the lymphocyte-to-monocyte (L/M) ratio at diagnosis serves as an independent prognostic factor in MDS and to explore its biological correlates.

Methods

A retrospective analysis of 554 patients with primary MDS diagnosed at the National Taiwan University Hospital was conducted. Patients were stratified by an L/M ratio cutoff of 1.5, determined by maximally selected rank statistics. Clinical, cytogenetic, and mutational profiles were assessed. Survival outcomes were analyzed using Kaplan–Meier methods and multivariable Cox regression incorporating IPSS-R, IPSS-M, and WHO-2022/ICC classifications. RNA sequencing was performed on diagnostic bone marrow samples to evaluate transcriptomic differences between groups.

Results

Patients with L/M ratio > 1.5 were younger, had lower platelet counts, more advanced subtypes, and higher frequencies of STAG2 and U2AF1 mutations. Elevated L/M ratio was significantly associated with inferior leukemia-free and overall survival, independent of established prognostic models. Adverse prognostic effects were mitigated by allogeneic hematopoietic stem cell transplantation but not by hypomethylating agents. Transcriptomic analysis revealed downregulation of inflammatory pathways (IL-2–STAT5, IL6–JAK–STAT3, interferon responses) and the p53 pathway, along with enrichment of MYC targets in the high L/M group.

Conclusion

An elevated L/M ratio is an independent and readily available biomarker that predicts poor outcomes in MDS. Integration of this parameter into existing risk models may refine prognostication and guide treatment intensity. Transcriptomic findings suggest immune suppression and p53 deregulation underlie its adverse impact, highlighting potential therapeutic avenues.

Keywords

Myelodysplastic syndromes/neoplasms, Prognosis, Risk stratification, Lymphocyte, Monocyte

Introduction

Myelodysplastic syndromes/neoplasms (MDS), a broad category of clonal myeloid disorders, are characterized by dysregulated hematopoiesis, which leads to cytopenia and dysplastic hematopoietic cells. Clinical and genetic heterogeneity, recurrent chromosomal abnormalities, and variable prognostic outcomes are features of MDS [1]. To risk-stratify patients with MDS and direct treatment, several prognostic models have been developed, such as the International Prognostic Scoring System (IPSS) [2], revised IPSS (IPSS-R) [3], molecular IPSS (IPSS-M), World Health Organization (WHO) Classification-based Prognostic Scoring System [4], and MD Anderson Prognostic Scoring System [5]. These models primarily incorporate parameters such as cytopenia severity, cytogenetic abnormalities, bone marrow (BM) blast percentage, gene mutations, and transfusion dependency.
Recent studies have also highlighted the prognostic relevance of peripheral lymphocyte and monocyte counts in solid tumors and hematologic malignancies [6, 7, 8, 9, 1011]. In MDS, absolute lymphocyte count (ALC) and absolute monocyte count (AMC) at diagnosis are individually associated with patient outcomes [12, 13]. Lymphopenia adversely affects survival in IPSS-M-defined low-risk MDS patients [14], whereas monocytopenia, observed in 29.5% of MDS, correlates with higher blast counts and worse outcomes [12, 13]. These findings suggest that peripheral immune cell profiles may reflect the underlying disease biology and immune dysregulation. Given the interplay between these two values, the lymphocyte-to-monocyte (L/M) ratio presents as a more integrative and robust biomarker; however, studies regarding the prognostic implications of the L/M ratio in patients with MDS are scarce.

Methods

At the National Taiwan University Hospital (NTUH), data were collected from 554 patients with primary MDS who were diagnosed and treated at NTUH. We retrospectively reviewed a cohort of 554 patients diagnosed with primary MDS based on the WHO-2016 criteria, with subsequent reclassification based on the WHO-2022 and International Consensus Classification (ICC). The survival impact of the L/M ratio was evaluated in the context of the novel classification systems IPSS-R and IPSS-M. To avoid confounding factors, patients with a history of chemotherapy, radiation, or hematologic malignancies were excluded, given the distinct mutational profiles and clinical outcomes of primary and secondary MDS [15]. The TruSight Myeloid Panel and HiSeq platform (Illumina, San Diego, CA, USA) were used to sequence the cryopreserved BM samples and identify mutations in 54 myeloid-related genes [16, 17] (Supplemental Table 1). TP53 copy-neutral loss of heterozygosity and five residual genes (ETNK1, GNB1, NF1, PPM1D, and PRPF8) identified using the IPSS-M model were not evaluated in this study. By following the manufacturer's instructions, the library was prepared and sequenced to achieve a median read depth of 10,550 x. Variant analysis used databases for somatic mutation annotation and interpretation, including COSMIC v86, dbSNP v151, ClinVar, PolyPhen-2, and SIFT. A variant analysis diagnostic algorithm has been previously described [18]. Polymerase chain reaction (PCR) and fluorescence capillary electrophoresis are required for FLT3-ITD analysis due to the limitations of next-generation sequencing (NGS), whereas Sanger sequencing and PCR are required for KMT2A-PTD analysis [19, 20]. Cellularity and fibrosis of the BM were evaluated and verified by pathologists using reticulin staining. Cytogenetic analyses were performed according to the International System for Human Cytogenetic Nomenclature in cytogenetic analyses [20, 21].
Following the manufacturer’s instructions, RNA was extracted from diagnostic BM samples (without CD34 + cell isolation), and sequencing libraries were created using the TruSeq Stranded mRNA Library Prep Kit (Illumina). The libraries were subsequently sequenced using a 150-bp paired-end read mode on an Illumina NovaSeq 6000. STAR (v2.7) was used to align the clean reads to the human reference genome GRCh38 after adapter sequencing, and low-quality bases were eliminated from the raw sequencing data using Cutadapt (v3.0) in two-pass mode. Each gene's raw count was determined using GENCODE v28 annotation and was then converted to transcripts per million for additional analysis [22].
The NTUH Research Ethics Committee approved this study (approval number: 20220705RINB). Each participant provided written informed consent in compliance with the Declaration of Helsinki.

Statistical analysis

Fisher's exact or χ2 test for categorical variables and the Mann–Whitney U test for continuous variables were used in the statistical analyses. The time between diagnosis and leukemic transformation, death, or last follow-up was referred to as leukemia-free survival (LFS). The relationship between the date of diagnosis and the last follow-up or death from any cause was known as overall survival (OS). Survival curves were produced using Kaplan–Meier analysis, and the log-rank test was used to determine significance. For both univariable and multivariable analyses, Cox proportional hazards models were used. A time-dependent covariate was thought to be allogeneic hematopoietic stem cell transplantation (HSCT) [23]. Maximally selected rank statistics were applied to determine the optimal cutoff point of the L/M ratio [24, 25]. This approach was a suitable standardized two-sample linear rank statistic to determine the maximum standardized statistics of all potential cutoffs, which offered the best separation of the results into two groups [26, 27]. By selecting replacement samples of the same size from the original dataset, bootstrapping replicated the process of creating samples from an underlying population. The results were tested on individuals excluded from the bootstrap or original samples [28]. All P values were two-sided, and at P < 0.05, they were deemed statistically significant. IBM SPSS Statistics v23 for Windows was used for all analyses.

Results

Clinical characteristics and genetic profiles

The demographic features are presented in Table 1. For the total cohort, the median age was 67.3 years, with a male predominance (63.7%). According to the WHO-2016 classification, half (49.9%) of the patients had MDS with excess blasts (EB), including EB1 (19.9%) and EB2 (30.0%). When classifying patients with ICC, there were 76 (13.7%) and 11 (2.0%) patients with MDS/AML who had myelodysplasia-related gene mutations or myelodysplasia-related cytogenetic abnormalities, respectively (Table 1). A total of 21 (3.8%) and 36 (6.5%) patients met the diagnostic criteria for MDS with mutated TP53 and MDS/AML with mutated TP53, respectively, based on different blast percentages (Table 1). For the WHO-2022 classification, 83 (15.0%) individuals had hypocellular marrow, 12 (2.2%) had significant BM fibrosis, and were grouped as hypoplastic MDS (MDS-h) or MDS with fibrosis (MDS-f) (Table 1).
A total of 68.9% patients had IPSS-R intermediate-(25.5%), high-(20.9%), or very high-risk disease (22.5%), and a total of 61.0% patients had IPSS-M moderately high-(15.0%), high-(16.6%), or very high-risk (29.4%) disease (Table 1). Regarding treatments, 41.7% of patients with EB received hypomethylating agents (HMA, 41.7%) or chemotherapy (5.4%), and 19.4% of patients in the intermediate-, high-, or very-high-risk IPSS-R group underwent allogeneic HSCT.
Overall, 78.2% had at least one gene mutation or cytogenetic abnormality. As shown in Supplemental Table 2, the most common mutation in this cohort was the ASXL1 mutation (21.3%), followed by TET2 (15.5%), SF3B1 (13.9%), RUNX1 (12.3%), STAG2 (11.9%), and TP53 (10.6%). When stratified based on the biological function of the affected genes, mutations in genes involved in epigenetic modifications (45.5%), including DNA methylation-related genes (26.7%) and chromatin-modifying genes (28.7%), were the most common, followed by mutations in the spliceosome complex genes (34.3%).

Clinical and genetics differences between patients with high or low L/M ratio

As mentioned above, we used maximally selected rank statistics to determine the optimal L/M ratio cutoff that correlated with the outcomes. Differences in clinical characteristics and genetic profiles between patients with high (> 1.5) or low (≤ 1.5) L/M ratio were explored. Specifically, patients with L/M > 1.5 were significantly younger and had lower platelet counts at diagnosis. They had a higher prevalence of EB2 (WHO-2016), EB (ICC), and IB2 (ICC) subtypes, and a lower prevalence of MDS-SLD, MDS-RS-SLD, and SF3B1-mutated subtypes (as defined by both ICC and WHO-2022, Table 1). Taken together, patients with L/M > 1.5 had a lower proportion of low-risk IPSS-R or IPSS-M (Table 1 and Supplemental Fig. 1). Furthermore, those with L/M > 1.5 had more U2AF1 (9.5% vs. 4.4%, P = 0.028) and STAG2 (14.7% vs. 7.3%, P = 0.009) mutations, while they had less SF3B1 (10.6% vs. 19.3%, P = 0.004) mutations compared with those with L/M ≤ 1.5 (Fig. 1 and Supplemental Table 2). When categorized by the genetic functional group, patients with a high L/M ratio had more cohesion complex gene mutations (15.2% vs. 7.3%, P = 0.007) (Supplemental Table 2 and Fig. 1B).

Survival impact of L/M ratio

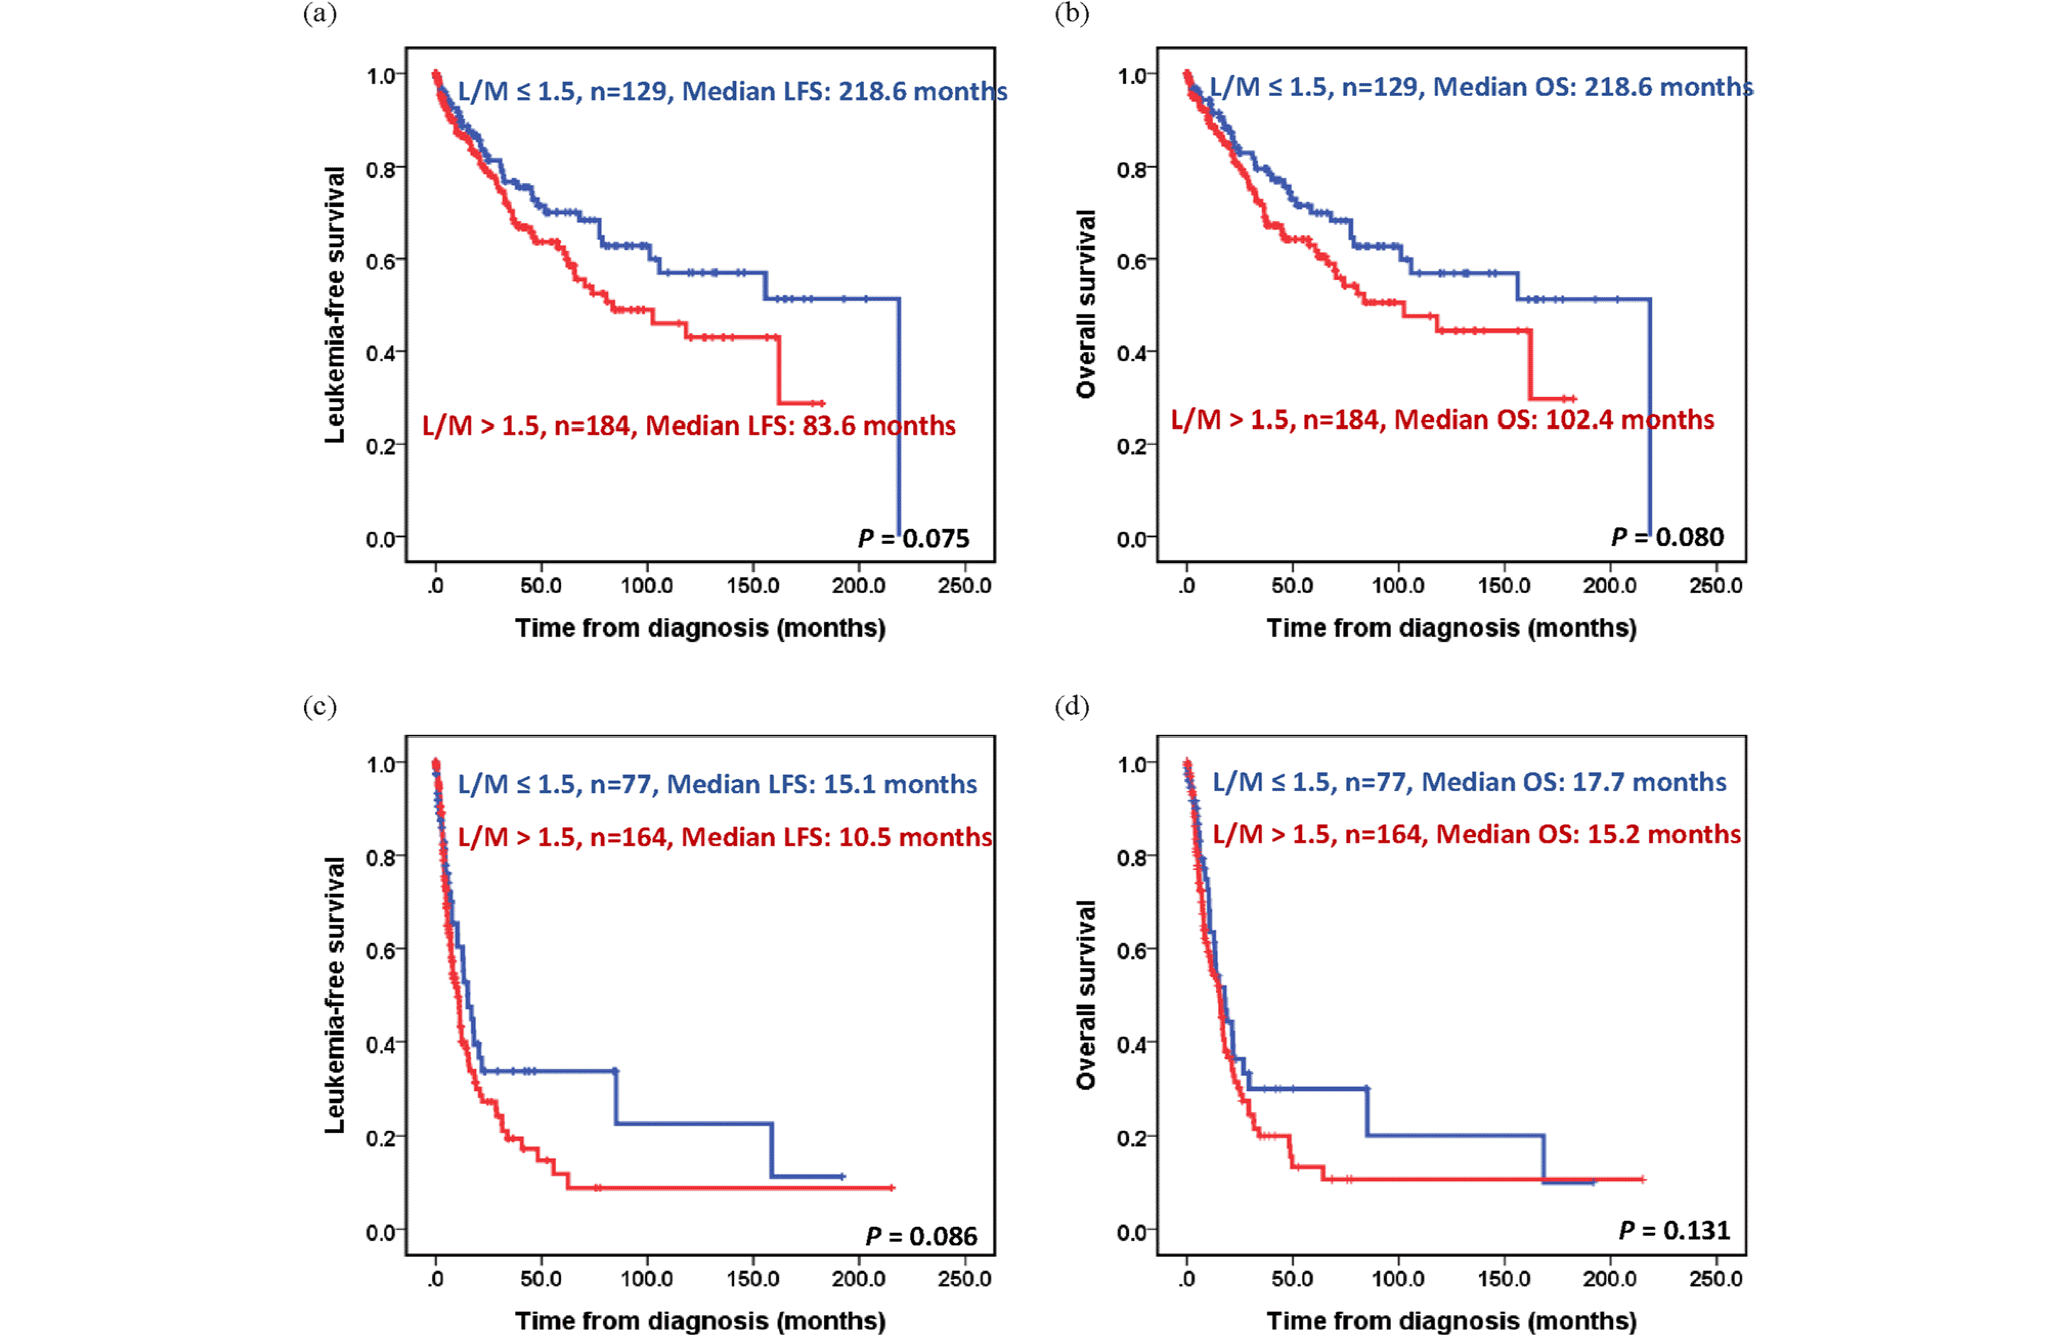
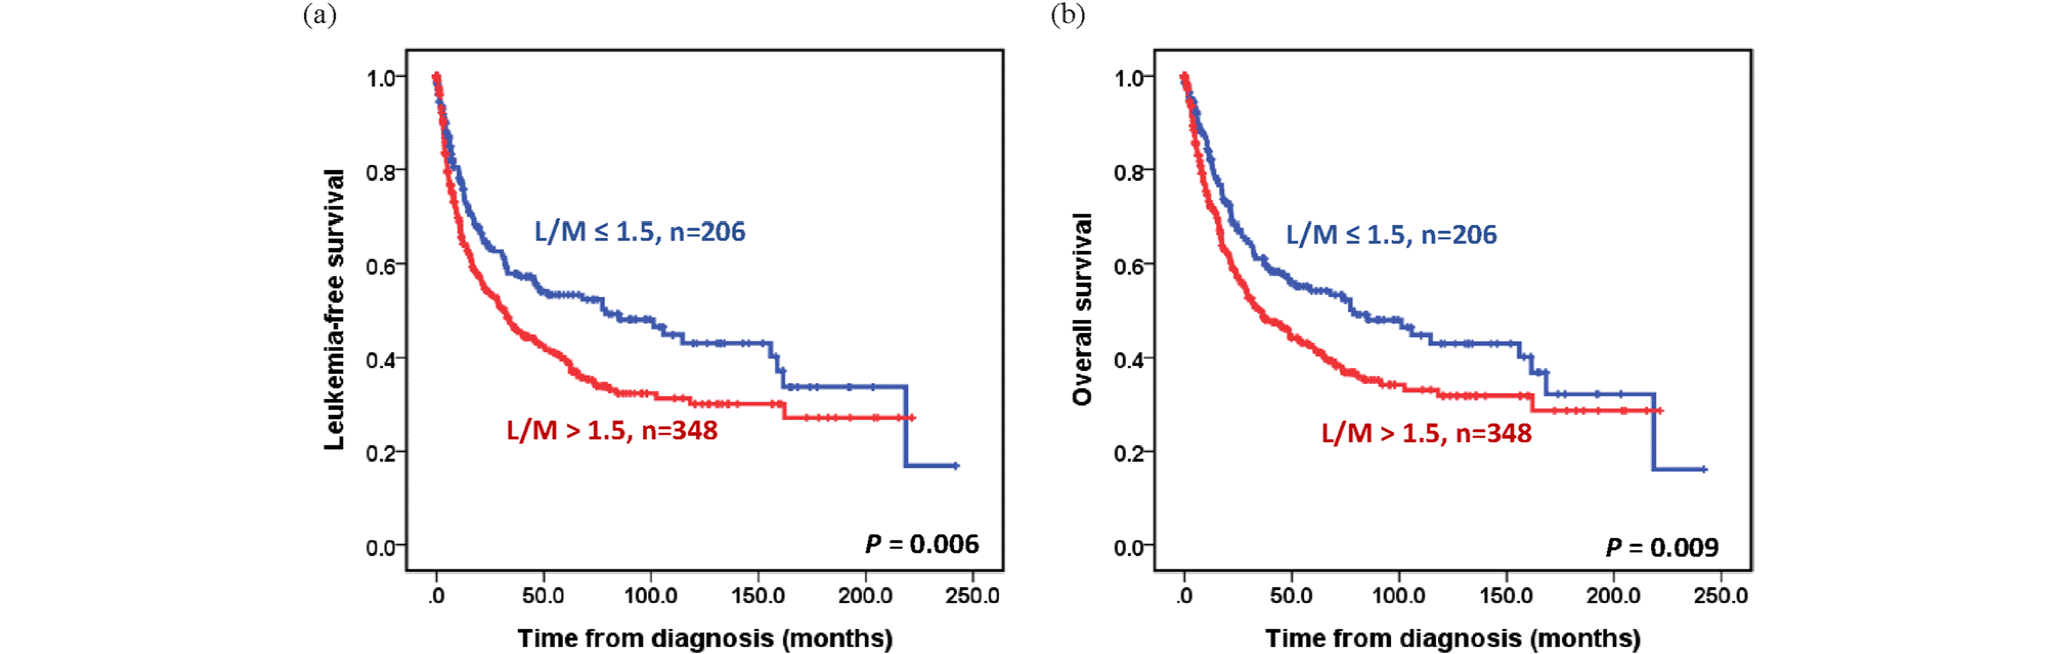
Kaplan–Meier survival analysis showed that patients with L/M ratio > 1.5 had LFS and OS of 31.5 and 34.9 months, respectively, which were significantly shorter than the LFS and OS of those with L/M ratio ≤ 1.5 (78.7 months for LFS and OS, both P < 0.05) (Fig. 2). When censoring at the transplantation, individuals with high L/M ratio had a trend of inferior outcomes in both lower (very low, low, or intermediate-risk IPSS-R) or higher (high or very high-risk IPSS-R) risk group (in lower risk group: median LFS: 83.6 vs. 218.6 months, P = 0.075; median OS: 102.4 vs. 218.6 months, P = 0.080; in higher risk group: LFS: 10.5 vs. 15.1 months, P = 0.086; median OS: 15.2 vs. 17.7 months, P = 0.131) (Fig. 3). According to our previous studies [29, 30], we defined MDS with del5(q), MDS with low blasts (MDS-LB), and MDS-LB and RS as low-risk MDS, whereas MDS with increased blasts and MDS-f were defined as high-risk MDS in the WHO-2022 classification. For the ICC, MDS with del(5q), MDS with mutated SF3B1, and MDS, NOS with SLD or MLD were defined as low-risk MDS. The results of Cox regression analyses were internally validated using the bootstrapping method. In univariable analysis, in addition to older age, high ferritin levels, MDS classification based on the ICC or WHO-2022 classification, and risk stratification by the IPSS-R or IPSS-M, L/M > 1.5 was associated with shorter LFS (hazard ratios [HR]: 1.422, P = 0.006) and OS (HR: 1.401, P = 0.010) (Supplemental Table 3). Furthermore, we validated the thresholds relevant to the prognostic impact of ALC (1.5, or 1.2 × 109/L) and AMC (0.2, or 0.3 × 109/L), which had been reported previously [12, 14, 31, 32] by using our cohort. No differences in survival were observed between the groups. As a continuous variable in the univariable analysis, a higher AMC was associated with shorter LFS and OS (both HR: 1.003, P < 0.001) (Supplemental Table 3).
Variables with a P-value < 0.1 in univariable Cox regression analysis and allo-HSCT were used as covariates. Two models incorporating ICC or WHO-2022 subtypes were used. For LFS, older age, high ferritin levels, ICC or WHO-2022 subtypes, and higher IPSS-M scores were associated with worse outcomes (all P < 0.05). L/M ratio > 1.5 had a trend toward shorter LFS (HR: 1.303, P = 0.094; HR: 1.358, P = 0.053, Table 2). For OS, older age, L/M > 1.5 (HR: 1.484, P = 0.014; HR: 1.548, P = 0.006), ICC or WHO-2022 subtypes, and higher IPSS-M were independent poor prognostic factors (Table 2). Additionally, HSCT may confer protective effects (HR: 0.597, P = 0.065 for LFS; HR: 0.568, P = 0.046 for OS). For patients who did not undergo HSCT, individuals with high L/M ratio had median LFS and OS of 28.8 and 31.3 months, respectively, which were significantly worse than those of patients with a low L/M ratio (median LFS and OS: 78.7 months, both P = 0.001, Supplemental Figs. 2A and 2B). At the same time, patients with high L/M ratio receiving HSCT had similar outcomes compared to those with low L/M ratio (median LFS 53.8 and 46.7 months, P = 0.755; median OS 73.3 and 73.7 months, P = 0.759, Supplemental Figs. 2C and 2D). In patients with very low, low, and intermediate IPSS-R risk, the adverse prognostic impact of a high L/M ratio was mitigated by HSCT (Supplemental Fig. 3). However, HMA treatment could not abrogate the adverse effects of a high L/M ratio (P = 0.056 for LFS and P = 0.023 for OS).
Using multivariable analyses, we assessed the prognostic significance of AMC and L/M ratios by combining various variables. Even after controlling for AMC, the L/M ratio remained a valid indicator of poor prognosis for both LFS and OS (Supplemental Table 4). However, without the simultaneous assessment of lymphocyte counts, AMC alone did not demonstrate significant value in independently predicting outcomes (Supplemental Table 5).

Functional analysis of patients with high or low L/M ratio

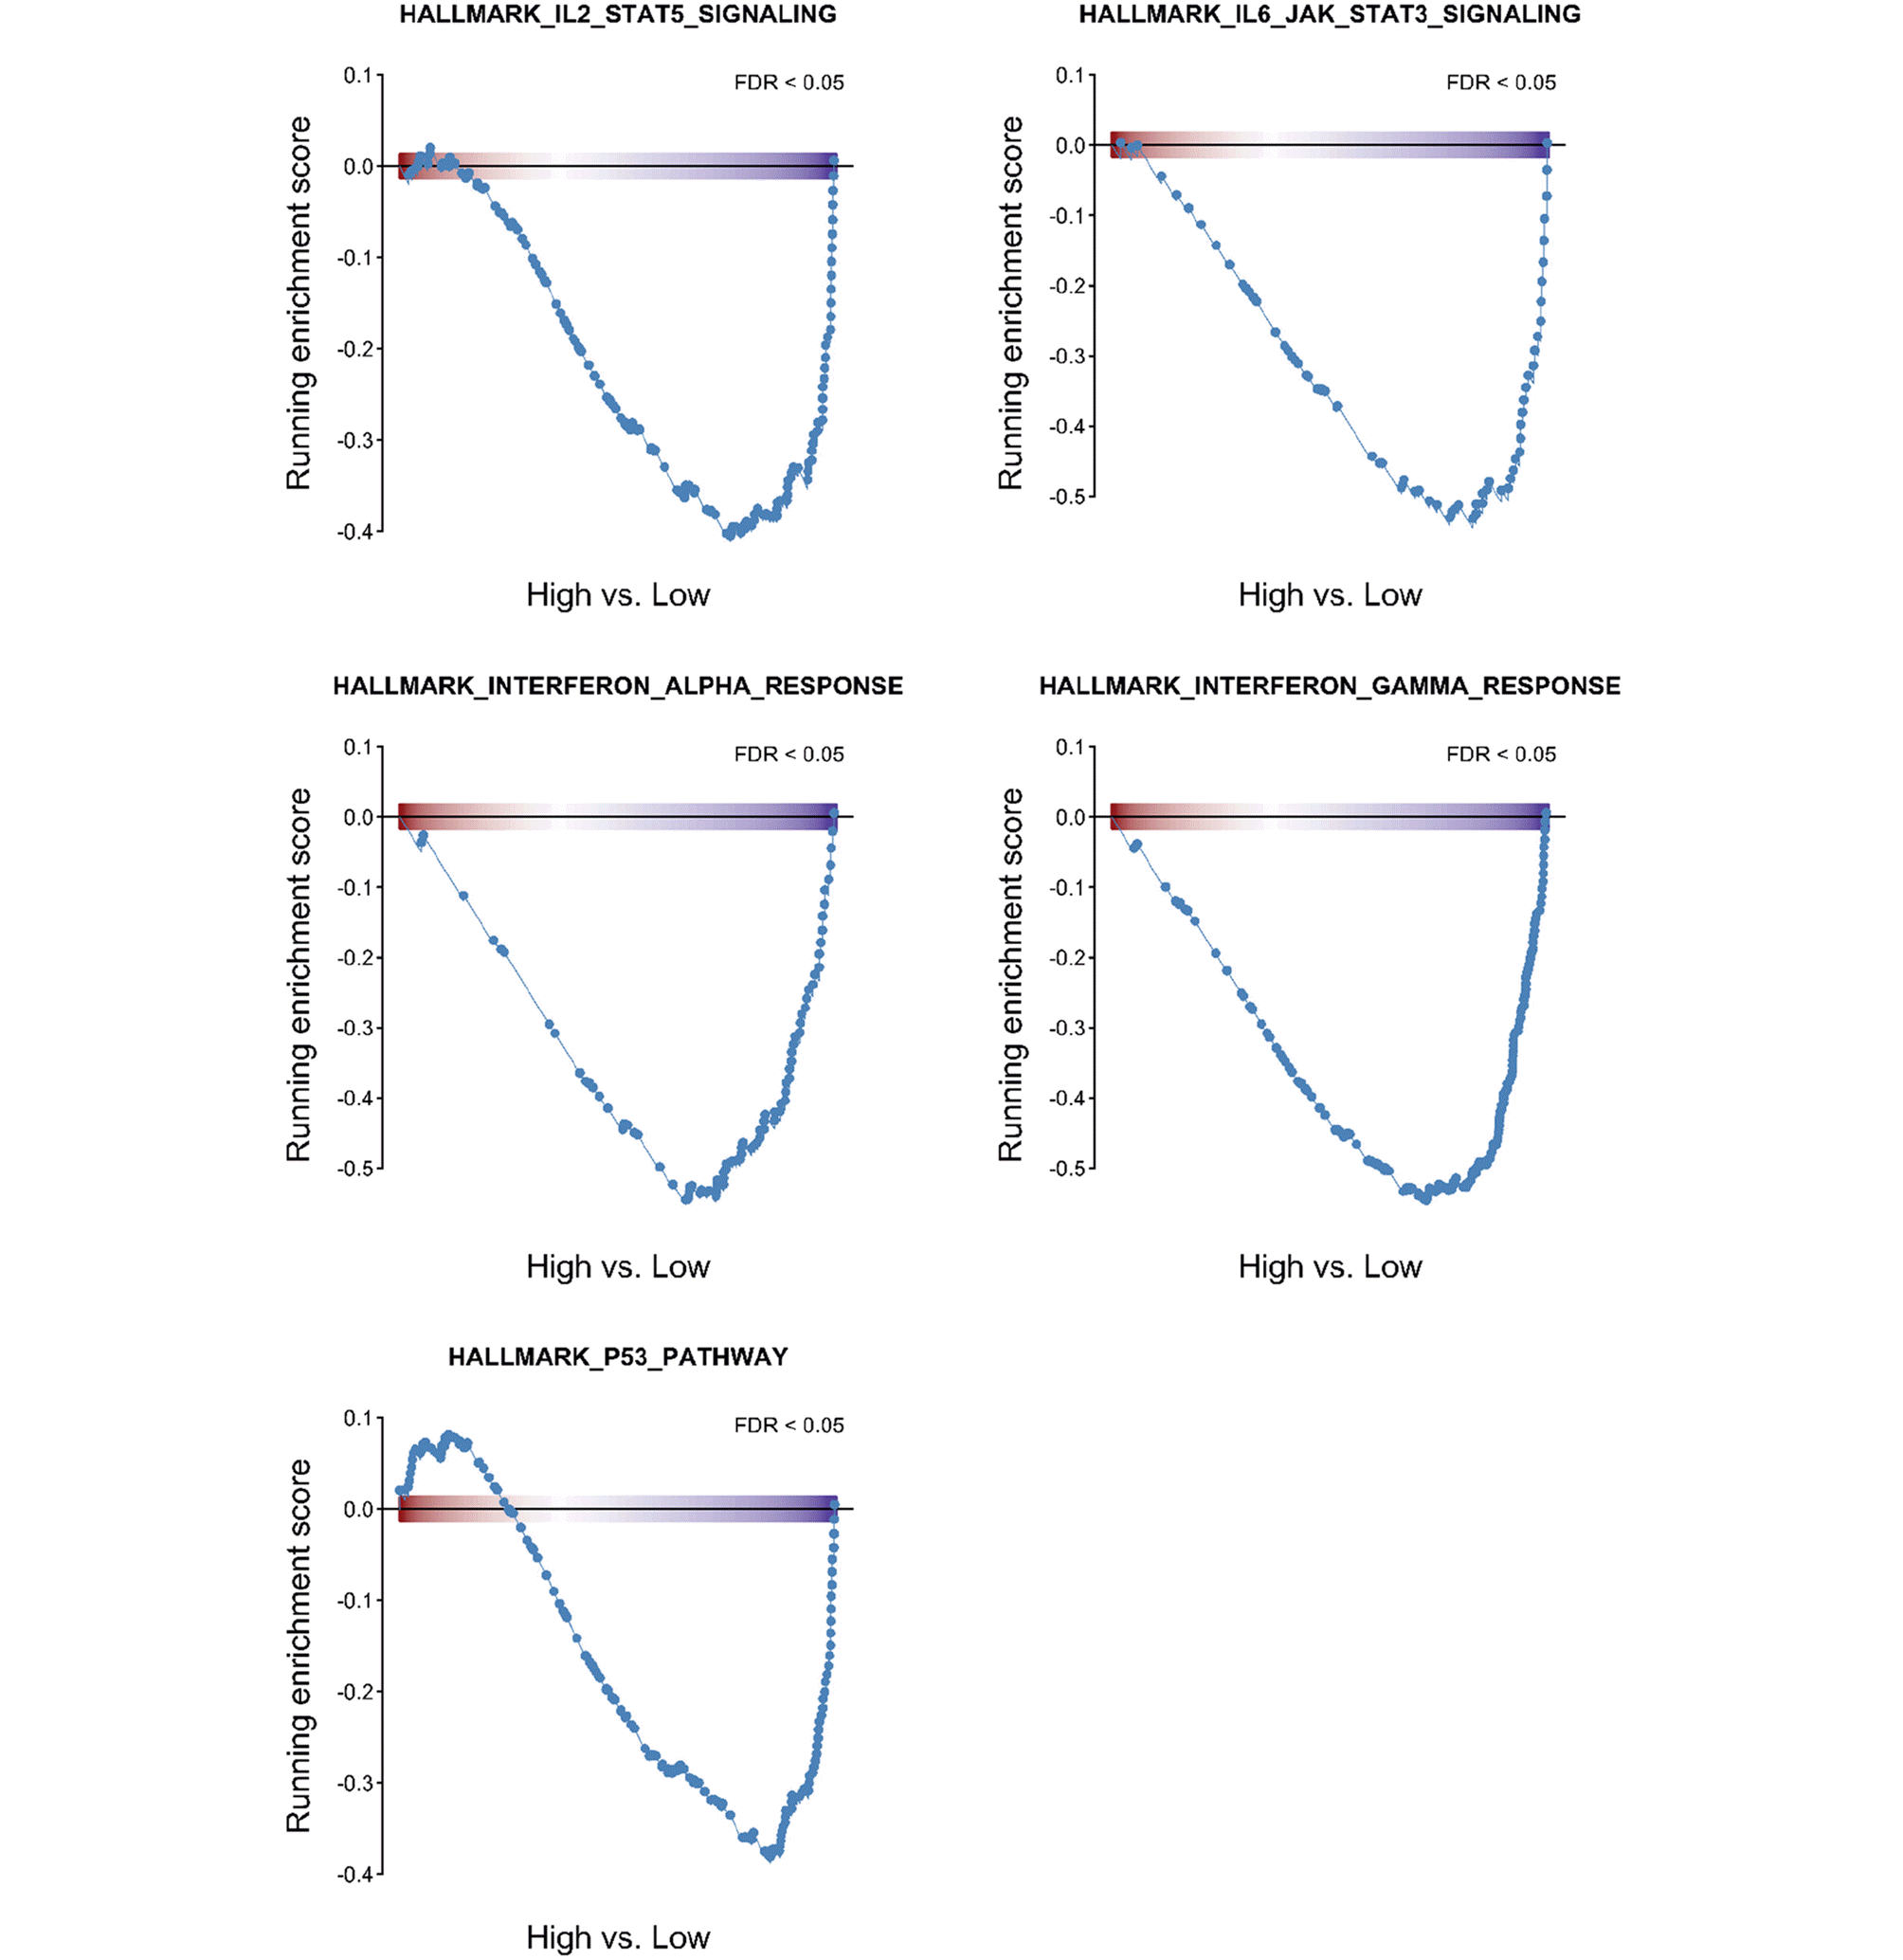
To clarify the potential biological mechanisms underlying the negative prognostic effect of a higher L/M ratio, we analyzed RNA sequencing data of BM samples from 66 and 44 patients with high and low L/M ratios, respectively. Differential expression analysis between patients with high vs. low L/M ratios was performed (Supplemental Fig. 4). The significantly underexpressed functional pathways in patients with a high L/M ratio included IL-2–STAT5, IL6-JAK-STAT3, and interferon-gamma/alpha responses that regulate the inflammatory response (Fig. 4). Similarly, patients with a high L/M ratio showed notable downregulation of the p53 pathway and positive enrichment of MYC target genes (Fig. 4).

Discussion

This study demonstrated that an elevated L/M ratio of > 1.5 at diagnosis is an independent prognostic factor in patients with MDS, even after adjusting for established risk scoring systems such as IPSS-R and IPSS-M. Furthermore, we assessed the differences in clinical characteristics, genetic profiles, disease subtypes based on the WHO-2016 and WHO-2022 criteria, ICC, and the distribution of risk stratification using the IPSS-R and IPSS-M between patients with high and low L/M ratios. Individuals with a high L/M ratio exhibited higher frequencies of U2AF1 and STAG2 mutations but fewer SF3B1 mutations and were more likely to present with advanced WHO-2022 or ICC subtypes.
In recent years, our knowledge of the pathophysiology underlying MDS has advanced considerably, with disease pathogenesis largely driven by molecular alterations [33, 34, 3536]. In a more contemporary effort, Bernard et al. proposed the IPSS-M, a prognostic model that integrates clinical parameters, cytogenetic abnormalities, and somatic mutations in 31 genes [37]. The absolute neutrophil count was excluded due to a lack of independent prognostic factors. A six-risk category schema was established, which had a higher prognostic predictive accuracy than the IPSS-R. Previously, we confirmed the prognostic value of the IPSS-M and validated its performance in an Asian cohort [20].
Both the WHO-2022 classification [38] and the novel ICC [39] introduced novel disease entities that incorporated the mutation status of SF3B1 and TP53. Furthermore, the WHO-2022 classification evaluates BM cellularity and fibrosis to define MDS-h and MDS-f. However, the lack of comprehensive genetic sequencing technologies, including NGS or PCR for KMT2A-PTD detection, prevents IPSS-M or novel classification systems from being widely used. Because patients with MDS have severe neutropenia and/or neutrophil dysfunction, they are more likely to experience infectious complications. Pollyea et al. discovered that compared to monocytes from healthy control participants, monocytes from patients with MDS had comparatively normal innate immune functions [40]. Furthermore, monocytes from patients with MDS exhibit moderately elevated HLA-DR expression. These findings imply that monocytes help patients with MDS fight infections by compensating for other immune deficiencies [40]. Thus, several studies have documented the negative survival impact of monocytopenia in patients with MDS [12, 13, 31], and it has been linked to negative clinical characteristics, such as greater severity of anemia, neutropenia, and thrombocytopenia [12].
Lymphocyte count is increasingly being recognized as an important prognostic marker in various types of cancer [41, 42, 4344]. Previous studies have suggested an association between poor prognosis and a lower ALC. Silzle et al. found that lymphopenia < 1.2 × 109/l at diagnosis was associated with inferior outcomes in patients with MDS with low-risk IPSS-R [32]. In the very low- and low-risk IPSS-M groups, ALC < 1.5 × 109/l was correlated with other severe cytopenias, fewer SF3B1 mutations, and shorter OS [14]. In WHO-2016 classification-defined MDS with ring sideroblasts, Mangaonkar et al. confirmed the negative prognostic predictive value of lymphopenia [45]. Additionally, we validated the prognostic impacts of AMC and ALC, which revealed that AMC did not have a survival effect as a dichotomous variable. In contrast, as a continuous variable, a higher AMC conferred poor outcomes in the univariable analysis. When using a cutoff value of 1.2 × 109/L or 1.5 × 109/L, no survival differences were found. The L/M ratio serves as a significant prognostic biomarker in various cancers, reflecting the interplay between the immune system and tumor biology. In the multivariable analysis, when considering the survival impact of lymphocytes and monocytes, significance was retained for the L/M ratio but not for AMC. This indicated that host immunity may be considered as a factor to incorporate into current risk stratification models, and lymphocytes and monocytes should be evaluated concomitantly. In summary, the current study adds to this knowledge by showing that the L/M ratio is a more accurate prognostic marker than AMC or ALC alone.
In the past few years, various combinations of inflammatory parameters, including the ratios of neutrophils to lymphocytes, platelets to lymphocytes, and lymphocytes to monocytes, have been used to predict the prognosis of patients with hematological and oncological cancers [46, 4748]. One of the new inflammatory indices, the hemoglobin, albumin, lymphocyte, and platelet (HALP) score, can predict the outcomes of lymphoma, kidney, and lung cancers [49, 5051]. Gursoy et al. showed that a high HALP score was linked to adverse clinicopathological features in patients with MDS [43].
In our study, we revealed the prognostic implications of the L/M ratio in the context of two novel classification systems (WHO-2022 or ICC). Patients with an L/M ratio > 1.5 had more severe thrombocytopenia and a higher risk of mutational profile with more U2AF1, STAG2, but fewer SF3B1 mutations. Furthermore, we found that HSCT could improve the survival of patients with a high L/M ratio. Thus, these routine laboratory tests may be widely applied and may help identify patients who may benefit from more aggressive therapy.
To further clarify the mechanism underlying the adverse prognostic impact of a high L/M ratio in patients with MDS, we performed transcriptomic analysis and depicted differential gene expression. Gene set enrichment analysis revealed the downregulation of multiple immune and inflammatory signaling pathways, including interferon-alpha and gamma responses, IL6-JAK-STAT3, IL-2–STAT5, and the p53 pathway. These findings suggest a state of immunosuppression or immune evasion in patients with high L/M ratios, which may contribute to disease progression. The underexpression of the interferon signaling axis, particularly type I interferons, may impair antigen presentation and immune surveillance, thereby promoting leukemic clonal expansion [52]. STAT5 is essential for the development and functional maturation of multiple hematopoietic lineages, including B cells, T cells, natural killer cells, and erythroid progenitors. Loss-of-function STAT5 mutations are linked to impaired B cell adaptive immunity, immunosuppressive effects, and serious infections, which may contribute to poor outcomes [53]. Abnormal Stat3/5 signaling biosignature in patients with MDS has been reported to predict treatment response and outcomes [54]. The p53 pathway, a key tumor suppressor network, plays a critical role in genomic stability. Loss or dysfunction of p53 leads to enhanced self-renewal of leukemia-initiating cells [55] and evasion of cancer surveillance [56]. Downregulation of the p53 pathway in patients with high L/M ratios may further imply impaired apoptotic regulation and increased genomic instability. MYC expression increased in patients with a high L/M ratio. Higher MYC expression is associated with the blockade of myeloid cell differentiation [57], cooperation with other oncogenes [58], and cancer metabolism [59], which may result in accelerated disease progression and reduced survival [60]. Together, these results provide molecular insights into the adverse prognosis of patients with MDS with a high L/M ratio and highlight the potential utility of immunomodulatory or p53-targeted strategies in this population. The study's retrospective design, inability to assess TP53 copy-neutral loss of heterozygosity, the requirement of five residual genes by the IPSS-M, and treatment regimen variability are some of its limitations. Although the survival effect of the L/M ratio was internally validated using the bootstrapping method, external validation is warranted to confirm our results. The cutoff of 1.5 in current study may represent an internally optimized threshold rather than a universal reference value. In addition, owing to the retrospective nature of our cohort and incomplete time-to-event data in certain censored cases, reliable estimation of the C-index was not feasible in this study. The underlying pathophysiology of a high L/M ratio leading to poor prognosis requires further exploration. Future studies incorporating comprehensive immune profiling and prospectively standardized follow-up are warranted to quantitatively assess the incremental value of the L/M ratio in risk stratification and to better define its clinical utility—for example, identifying high-risk patients within the same IPSS-M category or optimizing the timing of allogeneic HSCT. However, our study provides a simple and highly applicable method for further identification of patients with MDS who are at a higher risk of progression. These findings have significant clinical implications in resource-limited settings. To find a cure, patients with high L/M ratios may be eligible for more intensive therapies.
In conclusion, this study presents compelling evidence for the prognostic value of the L/M ratio in MDS, advocating its integration into clinical practice. Transcriptomic profiling suggests that altered immune signaling and deregulated oncogenic pathways may have clinical implications. The L/M ratio is a simple and easy-to-use laboratory test that helps differentiate patients with different survival rates, which may potentially improve patient outcomes. Further validation in larger prospective cohorts is essential to confirm their roles in guiding treatment decisions.

Acknowledgements

We acknowledge the services provided by the Department of Laboratory Medicine and Medical Research, National Taiwan University Hospital, and Tai-Chen Cell Therapy Center. Moreover, we acknowledge the services provided by the DNA Sequencing Core of the First Core Laboratory of the National Taiwan University College of Medicine, Taiwan.

Notes

Authors’ contributions

WHL: Formal analysis, Investigation, Data Curation, Writing - Original Draft. XCHT, YYK, CLH, CYY, MCL, YLP, CYS, and MHT: Investigation. CCL, FMT, MYL, BSK, WCC, MY, and HFT: Resources. SCY and CTY: Investigation. HAH: Conceptualization, Design, Supervision, Funding acquisition, Writing - Review & Editing,. All the authors have reviewed and approved the final manuscript.

Funding

This work was partially supported by grants from the Ministry of Science and Technology (Taiwan) (MOST 104–2314-B-002–128-MY4, 106–2314-B-002–226-MY3, 108–2628-B-002–015, 109–2314-B-002–213, and 111–2314-B-002–279), and the Ministry of Health and Welfare (Taiwan) (MOHW 107-TDU-B-211–114009 and 111-TDU-B-221–114001). This work was partially supported by the National Key Area International Cooperation Alliance: University Academic Alliance in Taiwan, Kyushu-Okinawa Open University, Medicine and Life Sciences Integrative Program, which promotes international collaboration in advanced research.

Data availability

The datasets generated and analyzed in this study are available from the corresponding author upon reasonable request.

Declarations

Competing interests

The authors declare no competing interests.

Appendix

Supplementary Information

The online version contains supplementary material available at https://doi.org/10.1007/s44313-​025-​00115-0.

Publisher’s Note

Springer Nature remains neutral with regard to jurisdictional claims in published maps and institutional affiliations.

References

1. Tefferi A, Vardiman JW. Myelodysplastic syndromes. N Engl J Med. 2009; 361:1872–1885. PMID: 19890130. DOI: 10.1056/NEJMra0902908.
2. Greenberg P, Cox C, LeBeau MM, Fenaux P, Morel P, Sanz G, et al. International scoring system for evaluating prognosis in myelodysplastic syndromes. Blood. 1997; 89:2079–2088. PMID: 9058730. DOI: 10.1182/blood.V89.6.2079.
3. Greenberg PL, Tuechler H, Schanz J, Sanz G, Garcia-Manero G, Solé F, et al. Revised international prognostic scoring system for myelodysplastic syndromes. Blood. 2012; 120:2454–2465. PMID: 22740453. PMCID: 4425443. DOI: 10.1182/blood-2012-03-420489.
4. Malcovati L, Germing U, Kuendgen A, Della Porta MG, Pascutto C, Invernizzi R, et al. Time-dependent prognostic scoring system for predicting survival and leukemic evolution in myelodysplastic syndromes. J Clin Oncol. 2007; 25:3503–3510. PMID: 17687155. DOI: 10.1200/JCO.2006.08.5696.
5. Kantarjian H, O'Brien S, Ravandi F, Cortes J, Shan J, Bennett JM, et al. Proposal for a new risk model in myelodysplastic syndrome that accounts for events not considered in the original International Prognostic Scoring System. Cancer. 2008; 113:1351–1361. PMID: 18618511. DOI: 10.1002/cncr.23697.
6. Stotz M, Szkandera J, Stojakovic T, Seidel J, Samonigg H, Kornprat P, et al. The lymphocyte to monocyte ratio in peripheral blood represents a novel prognostic marker in patients with pancreatic cancer. Clin Chem Lab Med. 2015; 53:499–506. PMID: 25389993. DOI: 10.1515/cclm-2014-0447.
7. Hutterer GC, Sobolev N, Ehrlich GC, Gutschi T, Stojakovic T, Mannweiler S, et al. Pretreatment lymphocyte-monocyte ratio as a potential prognostic factor in a cohort of patients with upper tract urothelial carcinoma. J Clin Pathol. 2015; 68:351–355. PMID: 25661796. DOI: 10.1136/jclinpath-2014-202658.
8. Hu RJ, Ma JY, Hu G. Lymphocyte-to-monocyte ratio in pancreatic cancer: prognostic significance and meta-analysis. Clin Chim Acta. 2018; 481:142–146. PMID: 29544747. DOI: 10.1016/j.cca.2018.03.008.
9. Zhang X, Duan J, Wen Z, Xiong H, Chen X, Liu Y, et al. Are the derived indexes of peripheral whole blood cell counts (NLR, PLR, LMR/MLR) clinically significant prognostic biomarkers in multiple myeloma? A systematic review and meta-analysis. Front Oncol. 2021; 11:766672. PMID: 34888244. PMCID: 8650157. DOI: 10.3389/fonc.2021.766672.
10. Yang J, Guo X, Hao J, Dong Y, Zhang T, Ma X. The prognostic value of blood-based biomarkers in patients with testicular diffuse large B-cell lymphoma. Front Oncol. 2019; 9:1392. PMID: 31921649. PMCID: 6914857. DOI: 10.3389/fonc.2019.01392.
11. Szkandera J, Gerger A, Liegl-Atzwanger B, Absenger G, Stotz M, Friesenbichler J, et al. The lymphocyte/monocyte ratio predicts poor clinical outcome and improves the predictive accuracy in patients with soft tissue sarcomas. Int J Cancer. 2014; 135:362–370. PMID: 24347236. DOI: 10.1002/ijc.28677.
12. Silzle T, Blum S, Kasprzak A, Nachtkamp K, Rudelius M, Hildebrandt B, et al. The Absolute Monocyte Count at Diagnosis Affects Prognosis in Myelodysplastic Syndromes Independently of the IPSS-R Risk Score. Cancers (Basel). 2023;15(14):3572.
13. Diamantopoulos PT, Charakopoulos E, Symeonidis A, Kotsianidis I, Viniou NA, Pappa V, et al. Real world data on the prognostic significance of monocytopenia in myelodysplastic syndrome. Sci Rep. 2022; 12:17914. PMID: 36289284. PMCID: 9606364. DOI: 10.1038/s41598-022-21933-7.
14. Fandrei D, Huynh T, Sébert M, Aguinaga L, Bisio V, Kim R, et al. Lymphopenia confers poorer prognosis in myelodysplastic syndromes with very low and low IPSS-M. Blood Cancer J. 2023; 13:193. PMID: 38123548. PMCID: 10733334. DOI: 10.1038/s41408-023-00965-w.
15. Kuzmanovic T, Patel BJ, Sanikommu SR, Nagata Y, Awada H, Kerr CM, et al. Genomics of therapy-related myeloid neoplasms. Haematologica. 2020; 105:e98–e101. PMID: 31413096. PMCID: 7049337. DOI: 10.3324/haematol.2019.219352.
16. Lee WH, Lin CC, Tsai CH, Tseng MH, Kuo YY, Liu MC, et al. Effect of mutation allele frequency on the risk stratification of myelodysplastic syndrome patients. Am J Hematol. 2022; 97:1589–1598. PMID: 36109871. DOI: 10.1002/ajh.26734.
17. Bernard E, Tuechler H, Greenberg PL, Hasserjian RP, Arango Ossa JE, Nannya Y, et al. Molecular international prognostic scoring system for myelodysplastic syndromes. NEJM Evid. 2022; 1:EVIDoa2200008. PMID: 38319256. DOI: 10.1056/EVIDoa2200008.
18. Tsai CH, Tang JL, Tien FM, Kuo YY, Wu DC, Lin CC, et al. Clinical implications of sequential MRD monitoring by NGS at 2 time points after chemotherapy in patients with AML. Blood Adv. 2021; 5:2456–2466. PMID: 33999144. PMCID: 8152512. DOI: 10.1182/bloodadvances.2020003738.
19. Shiah HS, Kuo YY, Tang JL, Huang SY, Yao M, Tsay W, et al. Clinical and biological implications of partial tandem duplication of the MLL gene in acute myeloid leukemia without chromosomal abnormalities at 11q23. Leukemia. 2002; 16:196–202. PMID: 11840285. DOI: 10.1038/sj.leu.2402352.
20. Lee WH, Tsai MT, Tsai CH, Tien FM, Lo MY, Tseng MH, et al. Validation of the molecular international prognostic scoring system in patients with myelodysplastic syndromes defined by international consensus classification. Blood Cancer J. 2023; 13:120. PMID: 37558665. PMCID: 10412560. DOI: 10.1038/s41408-023-00894-8.
21. International Standing Committee on Human Cytogenomic Nomenclature M-JJHRJMSSKG. ISCN 2020 an International System for Human Cytogenomic Nomenclature (2020) : recommendations of the International Standing Committee on Human Cytogenomic Nomenclature including revised sequence-based cytogenomic nomenclature developed in collaboration with the Human Genome Variation Society (HGVS) Sequence Variant Description Working Group. 2020.
22. Yao CY, Lin CC, Wang YH, Kao CJ, Tsai CH, Hou HA, et al. Kinome expression profiling improves risk stratification and therapeutic targeting in myelodysplastic syndromes. Blood Adv. 2024; 8:2442–2454. PMID: 38527292. PMCID: 11112608. DOI: 10.1182/bloodadvances.2023011512.
23. Devillier R, Forcade E, Garnier A, Guenounou S, Thepot S, Guillerm G, et al. In-depth time-dependent analysis of the benefit of allo-HSCT for elderly patients with CR1 AML: a FILO study. Blood Adv. 2022; 6:1804–1812. PMID: 34525180. PMCID: 8941467. DOI: 10.1182/bloodadvances.2021004435.
24. Laska E, Meisner M, Wanderling J. A maximally selected test of symmetry about zero. Stat Med. 2012; 31:3178–3191. PMID: 22729950. DOI: 10.1002/sim.5384.
25. Zheng BW, Huang W, Liu FS, Zhang TL, Wang XB, Li J, et al. Clinicopathological and Prognostic Characteristics in Spinal Chondroblastomas: A Pooled Analysis of Individual Patient Data From a Single Institute and 27 Studies. Global Spine J. 2023;13(3):713–23.
26. Hothorn T, Lausen B. On the exact distribution of maximally selected rank statistics. Comput Stat Data Anal. 2003; 43:121–137. DOI: 10.1016/S0167-9473(02)00225-6.
27. Lausen B, Hothorn T, Bretz F, Schumacher M. Assessment of optimal selected prognostic factors. Biom J. 2004; 46:364–374. DOI: 10.1002/bimj.200310030.
28. Steyerberg EW, Harrell FE Jr, Borsboom GJ, Eijkemans MJ, Vergouwe Y, Habbema JD. Internal validation of predictive models: efficiency of some procedures for logistic regression analysis. J Clin Epidemiol. 2001; 54:774–781. PMID: 11470385. DOI: 10.1016/S0895-4356(01)00341-9.
29. Lee WH, Lin CC, Tsai CH, Tien FM, Lo MY, Tseng MH, et al. Comparison of the 2022 world health organization classification and international consensus classification in myelodysplastic syndromes/neoplasms. Blood Cancer J. 2024; 14:57. PMID: 38594285. PMCID: 11004131. DOI: 10.1038/s41408-024-01031-9.
30. Lee WH, Lin CC, Tsai CH, Tien FM, Lo MY, Ni SC, et al. Clinico-genetic and prognostic analyses of 716 patients with primary myelodysplastic syndrome and myelodysplastic syndrome/acute myeloid leukemia based on the 2022 International Consensus Classification. Am J Hematol. 2023; 98:398–407. PMID: 36588411. DOI: 10.1002/ajh.26799.
31. Saeed L, Patnaik MM, Begna KH, Al-Kali A, Litzow MR, Hanson CA, et al. Prognostic relevance of lymphocytopenia, monocytopenia and lymphocyte-to-monocyte ratio in primary myelodysplastic syndromes: a single center experience in 889 patients. Blood Cancer J. 2017; 7:e550. PMID: 28362440. PMCID: 5380913. DOI: 10.1038/bcj.2017.30.
32. Silzle T, Blum S, Schuler E, Kaivers J, Rudelius M, Hildebrandt B, et al. Lymphopenia at diagnosis is highly prevalent in myelodysplastic syndromes and has an independent negative prognostic value in IPSS-R-low-risk patients. Blood Cancer J. 2019; 9:63. PMID: 31399557. PMCID: 6689049. DOI: 10.1038/s41408-019-0223-7.
33. Chen J, Kao YR, Sun D, Todorova TI, Reynolds D, Narayanagari SR, et al. Myelodysplastic syndrome progression to acute myeloid leukemia at the stem cell level. Nat Med. 2019; 25:103–110. PMID: 30510255. DOI: 10.1038/s41591-018-0267-4.
34. Ogawa S. Genetics of MDS. Blood. 2019; 133:1049–1059. PMID: 30670442. PMCID: 6587668. DOI: 10.1182/blood-2018-10-844621.
35. Hosono N. Genetic abnormalities and pathophysiology of MDS. Int J Clin Oncol. 2019; 24:885–892. PMID: 31093808. DOI: 10.1007/s10147-019-01462-6.
36. Rotter LK, Shimony S, Ling K, Chen E, Shallis RM, Zeidan AM, et al. Epidemiology and pathogenesis of myelodysplastic syndrome. Cancer J. 2023; 29:111–121. PMID: 37195766. DOI: 10.1097/PPO.0000000000000665.
37. Bernard E, Tuechler H, Greenberg PL, Hasserjian RP, Ossa JEA, Nannya Y, et al. Molecular international prognostic scoring system for myelodysplastic syndromes. NEJM Evid. 2022; 1:EVIDoa2200008. PMID: 38319256. DOI: 10.1056/EVIDoa2200008.
38. Khoury JD, Solary E, Abla O, Akkari Y, Alaggio R, Apperley JF, et al. The 5th edition of the World Health Organization classification of haematolymphoid tumours: myeloid and histiocytic/dendritic neoplasms. Leukemia. 2022; 36:1703–1719. PMID: 35732831. PMCID: 9252913. DOI: 10.1038/s41375-022-01613-1.
39. Arber DA, Orazi A, Hasserjian RP, Borowitz MJ, Calvo KR, Kvasnicka HM, et al. International consensus classification of myeloid neoplasms and acute leukemias: integrating morphologic, clinical, and genomic data. Blood. 2022; 140:1200–1228. PMID: 35767897. PMCID: 9479031. DOI: 10.1182/blood.2022015850.
40. Pollyea DA, Hedin BR, O'Connor BP, Alper S. Monocyte function in patients with myelodysplastic syndrome. J Leukoc Biol. 2018; 104:641–647. PMID: 29656609. DOI: 10.1002/JLB.5AB1017-419RR.
41. Sang B, Fan Y, Wang X, Dong L, Gong Y, Zou W, et al. The prognostic value of absolute lymphocyte count and neutrophil-to-lymphocyte ratio for patients with metastatic breast cancer: a systematic review and meta-analysis. Front Oncol. 2024; 14:1360975. PMID: 38515567. PMCID: 10955091. DOI: 10.3389/fonc.2024.1360975.
42. Zhao P, Zang L, Zhang X, Chen Y, Yue Z, Yang H, et al. Novel prognostic scoring system for diffuse large B-cell lymphoma. Oncol Lett. 2018; 15:5325–5332. PMID: 29552174. PMCID: 5840739.
43. Gursoy V, Sadri S, Kucukelyas HD, Hunutlu FC, Pinar IE, Yegen ZS, et al. HALP score as a novel prognostic factor for patients with myelodysplastic syndromes. Sci Rep. 2024; 14:13843. PMID: 38879594. PMCID: 11180126. DOI: 10.1038/s41598-024-64166-6.
44. Jimbo H, Horimoto Y, Ishizuka Y, Nogami N, Shikanai A, Saito M, et al. Absolute lymphocyte count decreases with disease progression and is a potential prognostic marker for metastatic breast cancer. Breast Cancer Res Treat. 2022; 196:291–298. PMID: 36156756. DOI: 10.1007/s10549-022-06748-4.
45. Mangaonkar AA, Farrukh F, Reichard KK, Ketterling RP, Gangat N, Al-Kali A, et al. Lymphocytopenia predicts shortened survival in myelodysplastic syndrome with ring sideroblasts (MDS-RS) but not in MDS/MPN-RS-T. Am J Hematol. 2022; 97:E109–E112. PMID: 34961962. DOI: 10.1002/ajh.26448.
46. Wang S, Ma Y, Sun L, Shi Y, Jiang S, Yu K, et al. Prognostic significance of pretreatment neutrophil/lymphocyte ratio and platelet/lymphocyte ratio in patients with diffuse large B-cell lymphoma. BioMed Res Int. 2018; 2018:9651254. PMID: 30643825. PMCID: 6311253. DOI: 10.1155/2018/9651254.
47. Jia W, Yuan L, Ni H, Xu B, Zhao P. Prognostic value of platelet-to-lymphocyte ratio, neutrophil-to-lymphocyte ratio, and lymphocyte-to-white blood cell ratio in colorectal cancer patients who received neoadjuvant chemotherapy. Technol Cancer Res Treat. 2021; 20:15330338211034291. PMID: 34308689. PMCID: 8317245. DOI: 10.1177/15330338211034291.
48. Go SI, Park S, Kang MH, Kim HG, Kim HR, Lee GW. Clinical impact of prognostic nutritional index in diffuse large B cell lymphoma. Ann Hematol. 2019; 98:401–411. PMID: 30413902. DOI: 10.1007/s00277-018-3540-1.
49. Peng D, Zhang CJ, Tang Q, Zhang L, Yang KW, Yu XT, et al. Prognostic significance of the combination of preoperative hemoglobin and albumin levels and lymphocyte and platelet counts (HALP) in patients with renal cell carcinoma after nephrectomy. BMC Urol. 2018; 18:20. PMID: 29544476. PMCID: 5855974. DOI: 10.1186/s12894-018-0333-8.
50. Yang N, Han X, Yu J, Shu W, Qiu F, Han J. Hemoglobin, albumin, lymphocyte, and platelet score and neutrophil-to-lymphocyte ratio are novel significant prognostic factors for patients with small-cell lung cancer undergoing chemotherapy. J Cancer Res Ther. 2020; 16:1134–1139. PMID: 33004760. DOI: 10.4103/jcrt.JCRT_1066_19.
51. Vlatka P, Marko L, Stefan M, Dorian L. The hemoglobin, albumin, lymphocyte, and platelet (HALP) score is a novel prognostic factor for patients with diffuse large B-cell lymphoma. J Cancer Res Ther. 2022; 18:725–732. PMID: 35900546. DOI: 10.4103/jcrt.jcrt_174_21.
52. Zitvogel L, Galluzzi L, Kepp O, Smyth MJ, Kroemer G. Type I interferons in anticancer immunity. Nat Rev Immunol. 2015; 15:405–414. PMID: 26027717. DOI: 10.1038/nri3845.
53. Smith MR, Satter LRF, Vargas-Hernández A. STAT5b: a master regulator of key biological pathways. Front Immunol. 2022; 13:1025373. PMID: 36755813. DOI: 10.3389/fimmu.2022.1025373.
54. Miltiades P, Lamprianidou E, Vassilakopoulos TP, Papageorgiou SG, Galanopoulos AG, Kontos CK, et al. The Stat3/5 signaling biosignature in hematopoietic stem/progenitor cells predicts response and outcome in myelodysplastic syndrome patients treated with azacitidine. Clin Cancer Res. 2016; 22:1958–1968. PMID: 26700206. DOI: 10.1158/1078-0432.CCR-15-1288.
55. Nabinger SC, Chen S, Gao R, Yao C, Kobayashi M, Vemula S, et al. Mutant p53 enhances leukemia-initiating cell self-renewal to promote leukemia development. Leukemia. 2019; 33:1535–1539. PMID: 30675010. PMCID: 9202234. DOI: 10.1038/s41375-019-0377-0.
56. Hernández Borrero LJ, El-Deiry WS. Tumor suppressor p53: biology, signaling pathways, and therapeutic targeting. Biochimica et Biophysica Acta (BBA). 2021; 1876:188556.
57. Selvakumaran M, Liebermann D, Hoffman B. The proto-oncogene c-myc blocks myeloid differentiation independently of its target gene ornithine decarboxylase. Blood. 1996; 88:1248–1255. PMID: 8695842. DOI: 10.1182/blood.V88.4.1248.bloodjournal8841248.
58. Miyamoto R, Kanai A, Okuda H, Komata Y, Takahashi S, Matsui H, et al. HOXA9 promotes MYC-mediated leukemogenesis by maintaining gene expression for multiple anti-apoptotic pathways. Elife. 2021;10:e64148.
59. Dong Y, Tu R, Liu H, Qing G. Regulation of cancer cell metabolism: oncogenic MYC in the driver's seat. Signal Transduct Target Ther. 2020; 5:124. PMID: 32651356. PMCID: 7351732. DOI: 10.1038/s41392-020-00235-2.
60. Gajzer D, Logothetis CN, Sallman DA, Calon G, Babu A, Chan O, et al. MYC overexpression is associated with an early disease progression from MDS to AML. Leuk Res. 2021; 111:106733. PMID: 34749168. PMCID: 8643343. DOI: 10.1016/j.leukres.2021.106733.

Fig. 1
Frequencies of the commonly occurred mutations (a) and frequencies of mutations categorized by the functional groups (b) in patients with myelodysplastic neoplasms/syndromes
br-61-6-f1.tif
Fig. 2
Kaplan–Meier curves for leukemia-free survival and overall survival in patients with myelodysplastic neoplasms/syndromes based on lymphocyte/monocyte (L/M) ratio. A Leukemia-free survival, stratified by L/M ratio. B Overall survival, stratified by L/M ratio
br-61-6-f2.tif
Fig. 3
Kaplan–Meier curves censoring at transplantation for leukemia-free survival and overall survival in patients with myelodysplastic neoplasms/syndromes based on lymphocyte/monocyte (L/M) ratio, stratified by revised International Prognostic Scoring System (IPSS-R). A Leukemia-free survival, stratified by L/M ratio in patients with very low-, low, or intermediate-risk IPSS-R. B Overall survival, stratified by L/M ratio in patients with very low-, low, or intermediate-risk IPSS-R. C Leukemia-free survival, stratified by L/M ratio in patients with high, or very high-risk IPSS-R. D Overall survival, stratified by L/M ratio in patients with high, or very high-risk IPSS-R
br-61-6-f3.tif
Fig. 4
Gene set enrichment analysis highlighted the underexpressed functional pathway in MDS patients with high lymphocyte to monocyte ratio
br-61-6-f4.tif
Table 1
Comparison of clinical characteristics between patients with high (> 1.5) or low (≦1.5) lymphocyte/monocyte ratio
Clinical characters
Total
(n = 554)
L/M ≤ 1.5
(n = 206)
L/M > 1.5
(n = 348)
P value
Sex
0.273
 Female
201 (36.3)
81 (39.3)
120 (34.5)
 Male
353 (63.7)
125 (60.7)
228 (65.5)
Age*
67.3 (18.4–94.5)
68.6 (19.3–94.5)
66.6 (18.4–94.2)
0.015
Laboratory data*
 WBC, × 109/L
3.39 (0.6–32.39)
3.44 (0.6–26.31)
3.36 (0.6–32.39)
0.588
 ANC, × 109/L
1.55 (0–23.48)
1.66 (0–15.65)
1.49 (0.01–23.48)
0.238
 ALC, × 109/L
1.17 (0.07–10.26)
1.03 (0.07–2.98)
1.28 (0.08–10.26)
 < 0.001
 Monocyote, × 109/L
0.22 (0.01–5.72)
0.36 (0.03–3.54)
0.15 (0.01–5.72)
 < 0.001
 Hb, g/dL
8.1 (2.6–17.1)
8.2 (3.4–14.1)
8.0 (2.6–17.1)
0.197
 Platelet, × 109/L
81 (1–721)
148 (7–655)
52 (1–721)
 < 0.001
 BM blast (%)
4.4 (0–19.5)
4.0 (0–19.2)
4.9 (0–19.5)
0.528
 PB blast (%)
0 (0–18.6)
0 (0–17.0)
0 (0–18.6)
0.123
IPSS-R
0.008
 Very low
20 (3.6)
11 (5.3)
9 (2.6)
0.093
 Low
152 (27.4)
72 (35.0)
80 (23.0)
0.003
 Int
141 (25.5)
46 (22.3)
95 (27.3)
0.194
 High
116 (20.9)
39 (18.9)
77 (22.1)
0.372
 Very high
125 (22.5)
38 (18.5)
87 (25.0)
0.075
IPSS-M
0.003
 Very low
16 (2.9)
9 (4.4)
7 (2.0)
0.109
 Low
119 (21.5)
61 (29.6)
58 (16.7)
 < 0.001
 Moderate low
81 (14.6)
29 (14.1)
52 (14.9)
0.781
 Moderate high
83 (15.0)
23 (11.2)
60 (17.2)
0.053
 High
92 (16.6)
31 (15.0)
61 (17.5)
0.448
 Very high
163 (29.4)
53 (25.7)
110 (31.6)
0.142
2016 WHO classification
 < 0.001
 MDS-5q
5 (0.9)
1 (0.5)
4 (1.1)
0.656
 MDS-SLD
79 (14.3)
40 (19.4)
39 (11.2)
0.008
 MDS-MLD
126 (22.7)
43 (20.9)
83 (23.9)
0.419
 MDS-RS-SLD
37 (6.7)
24 (11.7)
13 (3.7)
 < 0.001
 MDS-RS-MLD
24 (4.3)
12 (5.8)
12 (3.4)
0.184
 MDS-EB1
110 (19.9)
38 (18.4)
72 (20.7)
0.522
 MDS-EB2
166 (30.0)
48 (23.3)
118 (33.9)
0.008
 MDS-U
7 (1.3)
0 (0.0)
7 (2.0)
0.050
ICC
0.002
 MDS
413 (74.5)
159 (77.2)
254 (73.0)
0.273
 del(5q)
5 (0.9)
1 (0.5)
4 (1.1)
0.656
 mutated SF3B1
51 (9.2)
32 (15.5)
19 (5.5)
 < 0.001
 NOS, with SLD
90 (16.2)
41 (19.9)
49 (14.1)
0.073
 NOS, with MLD
131 (23.6)
46 (22.3)
85 (24.4)
0.575
 EB
115 (20.8)
33 (16.0)
82 (23.6)
0.034
 mutated TP53
21 (3.8)
6 (2.9)
15 (4.3)
0.405
 MDS/AML
141 (25.5)
47 (22.8)
94 (27.0)
0.273
 MDS-related genes mutations
76 (13.7)
26 (12.6)
50 (14.4)
0.564
 MDS-related cytogenetics
11 (2.0)
5 (2.4)
6 (1.7)
0.566
 mutated TP53
36 (6.5)
13 (6.3)
23 (6.6)
0.890
 NOS
18 (3.2)
3 (1.5)
15 (4.3)
0.083
2022 WHO classification
0.001
 MDS-5q
5 (0.9)
1 (0.5)
4 (1.1)
0.656
 MDS-SF3B1
67 (12.1)
40 (19.4)
27 (7.8)
 < 0.001
 MDS-h
83 (15.0)
27 (13.1)
56 (16.1)
0.341
 MDS-LB
122 (22.0)
52 (25.2)
70 (20.1)
0.159
 MDS-IB1
92 (16.6)
30 (14.6)
62 (17.8)
0.588
 MDS-IB2
127 (22.9)
35 (17.0)
92 (26.4)
0.006
 MDS-f
12 (2.2)
5 (2.4)
7 (2.0)
 > 0.999
 MDS-biTP53
46 (8.3)
16 (7.8)
30 (8.6)
0.725
Treatment
 HMA
147 (26.5)
40 (19.4)
107 (30.7)
0.004
 Intensive chemotherapy
18 (3.2)
5 (2.4)
13 (3.7)
0.401
 Clinical trial
22 (4.0)
7 (3.4)
15 (4.3)
0.595
 HSCT
93 (16.8)
31 (15.0)
62 (17.8)
0.400
 Supportive care
243 (43.9)
105 (51.0)
138 (39.7)
0.009
 Other treatment
122 (22.0)
50 (24.3)
72 (20.7)
0.325
P values of < 0.05 are statistically significant and are shown in bold
Data are presented as n (%)
*Median (range)
Other treatment: include low-dose cytarabine, rabbit-derived anti-thymocyte globulin, cyclosporine, danazol, eltrombopag, erythropoietin-stimulating agents, thalidomide, steroid, venetoclax-based therapy and oral chemotherapy
Abbreviations: ANC Absolute neutrophil count, ALC Absolute lymphocyte count, BM Bone marrow, Hb Hemoglobin, HMA Hypomethylating agent, HSCT Allogeneic hematopoietic stem cell transplantation, ICC International Consensus Classification, IPSS-R Revised international prognosis scoring system, IPSS-M Molecular international prognosis scoring system, L/M Lymphocyte/monocyte ratio, MDS-RS MDS with ring sideroblasts, MDS-EB MDS with excess blasts, MDS-SLD MDS with single lineage dysplasia, MDS-MLD MDS with multilineage dysplasia, MDS-RS-SLD MDS with ring sideroblasts and single lineage dysplasia, MDS-RS-MLD MDS with ring sideroblasts and multilineage dysplasia, MDS-U MDS, unclassifiable, MDS-5q MDS with low blasts and isolated 5q deletion, MDS-SF3B1 MDS with low blasts and SF3B1 mutation, MDS-LB and RS MDS with low blasts and ring sideroblasts, MDS-LB MDS with low blasts, MDS-h Hypoplastic MDS, MDS-IB1 MDS with increased blasts-1, MDS-IB2 MDS with increased blasts-2, MDS-f MDS with fibrosis, MDS-biTP53 MDS with biallelic TP53 inactivation, NOS Not otherwise specified, PB Peripheral blood, WBC While blood cell count
Table 2
Multivariable analysis Cox regression analysis of the impact of different variables on the leukemia-free survival and overall survival of patients with myelodysplastic syndromes/neoplasms
Variable
LFS
OS
LFS
OS
HR (95% CI)
P value
HR (95% CI)
P value
HR (95% CI)
P value
HR (95% CI)
P value
Age*
1.027 (1.016–1.038)
 < 0.001
1.032 (1.020–1.043)
 < 0.001
1.027 (1.016–1.038)
 < 0.001
1.032 (1.021–1.044)
 < 0.001
Female
0.859 (0.627–1.175)
0.341
0.894 (0.649–1.232)
0.494
0.855 (0.624–1.170)
0.327
0.893 (0.648–1.231)
0.491
Ferritin* (X 102 ng/mL)
1.001 (1.000–1.001)
0.022
1.000 (1.000–1.001)
0.078
1.001 (1.000–1.001)
0.014
1.000 (1.000–1.001)
0.065
L/M > 1.5
1.303 (0.956–1.775)
0.094
1.484 (1.084–2.031)
0.014
1.358 (0.996–1.851)
0.053
1.548 (1.130–2.119)
0.006
ICC
 < 0.001
 < 0.001
 Low-risk MDS
Reference
-
Reference
-
 MDS with EB
1.685 (1.074–2.644)
0.023
1.441 (0.905–2.292)
0.123
 MDS/AML
2.244 (1.344–3.746)
0.002
1.840 (1.082–3.131)
0.024
 Mutated TP53 §
4.666 (2.480–8.779)
 < 0.001
5.743 (2.967–11.118)
 < 0.001
WHO-2022
 < 0.001
 < 0.001
 MDS-h, and SF3B1
Reference
-
Reference
-
 Low-risk MDS
1.030 (0.649–1.634)
0.901
1.086 (0.683–1.727)
0.726
 High-risk MDS
1.826 (1.082–3.080)
0.024
1.592 (0.933–2.718)
0.088
 MDS-biTP53
4.588 (2.283–9.220)
 < 0.001
5.490 (2.664–11.312)
 < 0.001
IPSS-M
 < 0.001
 < 0.001
 < 0.001
 < 0.001
 Very low/low
Reference
-
Reference
-
Reference
-
Reference
-
 Moderate low
1.517 (0.854–2.695)
0.155
1.611 (0.908–2.859)
0.103
1.518 (0.852–2.704)
0.157
1.598 (0.898–2.845)
0.111
 Moderate high
2.081 (1.224–3.536)
0.007
1.952 (1.140–3.344)
0.015
2.023 (1.178–3.475)
0.011
1.872 (1.080–3.244)
0.025
 High
2.729 (1.559–4.776)
 < 0.001
2.898 (1.647–5.099)
 < 0.001
2.755 (1.561–4.861)
 < 0.001
2.866 (1.616–5.085)
 < 0.001
 Very high
5.119 (2.857–9.174)
 < 0.001
4.698 (2.593–8.514)
 < 0.001
5.536 (3.098–9.896)
 < 0.001
5.057 (2.804–9.121)
 < 0.001
HMA
0.959 (0.684–1.346)
0.810
0.833 (0.585–1.186)
0.311
1.070 (0.772–1.485)
0.684
0.943 (0.671–1.325)
0.735
HSCT
0.597 (0.345–1.032)
0.065
0.778 (0.449–1.349)
0.372
0.568 (0.330–0.976)
0.040
0.743 (0.432–1.275)
0.281
P values of < 0.05 are statistically significant and are shown in bold
*As continuous variables analysis
Low-risk MDS included MDS with del(5q), MDS-SF3B1, and MDS, NOS with SLD or MLD
MDS/AML with MDS-related gene mutations, MDS-related cytogenetic abnormalities, or not otherwise specified
§MDS or MDS/AML with mutated TP53
Abbreviations: CI Confidence interval, EB Excess blasts, HR Hazard ratios, HMA Hypomethylating agents, HSCT Allogeneic hematopoietic stem cell transplantation, ICC International Consensus Classification, IPSS-M Molecular International Prognostic Scoring System, L/M Lymphocyte/monocyte ratio, LFS Leukemia-free survival, MDS Myelodysplastic syndromes/neoplasms, MDS/AML Myelodysplastic syndromes/acute myeloid leukemia, OS Overall survival
TOOLS
Similar articles