Journal List > Blood Res > v.61 > 1516094459

Wei, Jia, Zhu, Yang, Zheng, Jing, Zhang, Cai, Han, Sun, Shu, Chen, Qin, Wang, and Luo: Prophylactic donor lymphocyte infusions after first allogeneic hematopoietic stem cell transplantation in children with acute leukemia

Abstract

Purpose

To evaluate the feasibility and safety of prophylactic donor lymphocyte infusion (DLI) following allogeneic hematopoietic stem cell transplantation (HSCT) to improve survival outcomes in pediatric patients with acute leukemia (AL).

Methods

Children with AL who received prophylactic DLI transfusion after allogeneic HSCT between October 2015 and October 2024 were retrospectively analyzed.

Results

In total, 101 pediatric patients with AL were enrolled in this study, comprising 42 acute lymphoblastic leukemia, 54 acute myeloid leukemia, and five mixed-phenotype acute leukemia cases. The median age at transplantation was 7.52 ± 3.98 years. The median time from HSCT to first DLI was 306.26 days (range 51.00–1016.00). Patients received a median cumulative dose of 5.00 × 10⁷/kg (0.50–36.20). Post-DLI GVHD occurred in 46.53% of cases. Most events were mild; severe GVHD occurred in only five cases. After prophylactic DLI transfusion, the 5-year overall survival (OS) and event-free survival (EFS) rates were 88.74% ± 3.70% and 79.66% ± 4.92%, respectively. The difference of the OS and EFS in patients with GVHD and without GVHD after prophylactic DLI transfusion were not statistically significant (χ2 = 0.39, P = 0.53 and χ2 = 0.98, P = 0.32). Cumulative DLI dose > 4.75 × 10⁷/kg was associated with favorable prognosis (Area under the curve 0.67, 95% confidence interval 0.50–0.83, P = 0.03).

Conclusion

Prophylactic DLI transfusion following allogeneic HSCT remains a safe and effective treatment for pediatric patients with AL and can reduce post-transplant relapse and improve long-term survival.

Keywords

Prophylactic donor lymphocyte infusion, Hematopoietic stem cell transplantation, Prognosis, Graft versus host disease, Acute leukemia

Introduction

Allogeneic hematopoietic stem cell transplantation (allo-HSCT) is an effective and potentially curative treatment for leukemia based on the potent graft-versus-leukemia (GVL) immune effect [1]. However, the outcomes for pediatric patients who undergo HSCT for high-risk acute lymphoblastic leukemia (ALL) and acute myeloid leukemia (AML) remain poor [2]. Approximately 30–80% of patients with AML relapse after transplant [3, 4]. Donor lymphocyte infusion (DLI) is widely used in post-HSCT treatment and prevention. It induces a polyclonal T cell response that targets multiple antigens on malignant cells [5]. Reportedly, the efficacy of therapeutic DLI is limited in pediatric acute leukemia (AL) after HSCT because of the rapid proliferation of leukemia cells [6, 7].
A recent study showed that prophylactic DLI can decrease the relapse rate in patients with AL without increasing the risk of severe GVHD [8]. Furthermore, the timing of intervention and infusion strategies have been the subject of intense investigation and remain critical unanswered questions in the field. In this article, we report our experience with the feasibility and safety of prophylactic DLI transfusion after HSCT.

Methods

Patients

This was a retrospective, observational study. Children with AL who underwent prophylactic DLI after allo-HSCT between October 2015 and October 2024 were enrolled. None of the patients had HLA-matched unrelated donors at the China Bone Marrow Bank. This study was conducted in accordance with the Declaration of Helsinki and was approved by the Institutional Review Board (IRB) of Beijing Children’s Hospital, Capital Medical University. All patients’ parents or guardians provided informed consent.
Data on the source of the HSCs, conditioning regimen, adverse effects, and prognosis were retrospectively reviewed. The last follow-up was defined as the number of days between the date of transplantation and the last clinic visit. In addition to this basic information, we analyzed prognosis, including overall survival (OS) and event-free survival (EFS) rates, in different subtypes. The comparisons and analyses were performed using previously reported methods. In addition, we focused on the occurrence of GVHD after DLI in these patients. The cohort will be stratified into two groups based on the presence or absence of GVHD after DLI to identify factors influencing the development of GVHD and to assess whether GVHD affects the overall prognosis of patients.

Conditioning regimens

  1. Ara-C + Bu + Cy + ATG + Me-CCNU: Cytarabine (Ara-C), 4 g/m2/d × 2 d, intravenous + Bu 0.8–1.2 mg/kg/per time, four times a day × 3 d, intravenous + cyclophosphamide (Cy) 1.8 g/m2/d × 2 d, intravenous + Me-CCNU 250 mg/m2 × 1 d, oral + anti-thymocyte globulin (ATG) 2.5 mg/kg/d × 4 d, intravenous;

  2. TBI + Cy + ATG ± Me-CCNU ± Flu: Total body irradiation (TBI) 12 Gy + Cy 30 or 50 mg/kg/d × 4 d, intravenous + ATG 2.5 mg/kg/d × 4 d, intravenous ± Me-CCNU 250 mg/m2 × 1 d, oral ± fludarabine (Flu) 25–35 mg/m2/d × (4–5)d, intravenous;

  3. Bu + Cy + ATG ± Flu: Bu 0.8–1.2 mg/kg/per time, four times a day, × 4 d, intravenous + Cy 30 or 50 mg/kg/d × 4 d, intravenous + ATG 2.5 mg/kg/d × 4 d, intravenous ± Flu 25–35 mg/m2/d × (4–5) d, intravenous;

  4. Bu + Cy + TT + ATG ± Flu: Bu 0.8–1.2 mg/kg/per time, four times a day, × 3 d, intravenous + thiotepa (TT) 10 mg/kg × 1 d, intravenous + Cy 30 or 50 mg/kg/d × 4 d, intravenous + ATG 2.5 mg/kg/d × 4 d, intravenous ± fludarabine (Flu) 25–35 mg/m2/d × (4–5) d, intravenous;

GVHD prophylaxis

Acute and chronic graft-versus-host diseases were diagnosed and graded by physicians according to defined criteria [9, 10]. All patients received cyclosporine A (CsA), mycophenolate mofetil (MMF), or short-term methotrexate (MTX) to prevent GVHD after HSCT. However, none of the patients received GVHD prophylaxis before DLI transfusion.

Prophylactic DLI transfusion

Four weeks after withdrawal of all immunosuppressants, if the patient was without GVHD and effective targeted drugs, prophylactic DLI transfusion was started to prevent AL relapse. DLI was administered in graded aliquots starting at 5 × 106/kg or 1 × 107/kg CD3+ lymphocytes according to the patient’s condition. For patients with aGVHD after HSCT, typically initiated DLI was at 5.00 × 10⁶/kg. Doses were escalated to 1.00 × 10⁷/kg in the absence of GVHD. For patients without aGVHD after HSCT, DLI was started at 1.00 × 10⁷/kg, and escalation to 5 × 10⁷/kg was done if the minimal residual disease (MRD) turned positive. Infusions were administered every 4 weeks without GVHD manifestations but discontinued upon severe GVHD development after transfusion.

Evaluation of disease status

The disease status after allo-HSCT was divided into two subtypes: OS and EFS. OS was estimated from the date of HSCT until the date of death for any reason or last contact with the patient. EFS was estimated from the time of HSCT to the appearance of any of the following events: progression, relapse, death, or a second HSCT (due to engraftment failure or loss of donor chimerism).

Statistical analysis

Statistical analyses were performed using the IBM SPSS Statistics 24 software (IBM, USA). Continuous variables were presented as the means ± standard deviation for normal distribution or the medians (range) for abnormal distribution. The t-test was used to compare measurement data with a normal distribution, and the rank-sum test was used to compare measurement data with an abnormal distribution. The chi-square (χ2) test was used to compare the enumeration data. Estimation of overall survival rate was done using the Kaplan–Meier method. The log-rank test was used to verify OS and compare survival rates between the groups. Receiver operating characteristic (ROC) curve analysis was performed to determine the cutoff values. A Bayesian formula was used to analyze the sensitivity and specificity. P < 0.05 indicated a significant difference.

Results

General information

A total of 101 pediatric patients with AL received prophylactic DLI post-HSCT, accounting for 59.73% of HSCT recipients during the study period. The cohort comprised 42 patients with acute lymphoblastic leukemia (ALL), 54 with acute myeloid leukemia (AML), and five with mixed-phenotype acute leukemia (MPAL), with a male-to-female ratio of 1.79:1 (Table 1).
  • ALL

    Among the 42 patients with ALL, 26 had B-lineage ALL (B-ALL) (common B-ALL: 22, pre-B ALL: 3, pro-B ALL: 1), 15 had T-lineage ALL (T-ALL), and one had B/T mixed ALL. Genetic abnormalities were identified in 23 patients, most commonly the BCR:ABL1 fusion (n = 5). The pre-HSCT disease status included first complete remission (CR1) in 27 patients and second complete remission (CR2) in 15 patients.
  • AML

    The AML cohort (n = 54) included eight myeloid sarcoma cases and 16 with extramedullary involvement (central nervous system involvement: seven). Fusion genes were detected in 51 patients, predominantly RUNX1::RUNX1T1 (n = 13) and KMT2A rearrangements (n = 6). Chromosomal abnormalities were observed in all 35 patients. The pre-HSCT status comprised CR1 in 47 patients, CR2 in six, and non-response (NR) in one patient.
  • MPAL

    Among the five MPAL cases, genetic abnormalities (BCR::ABL1, KRAS, and KMT2A rearrangements) were identified in three patients. The pre-HSCT status of all patients was CR1.
Transplantation information

The mean age at transplantation was 7.52 ± 3.98 years, with a median time from diagnosis to transplantation of 432.00 days (range, 77.00–3243.00 days). Among mis-matched related donor (MMSD) transplants, donor types included parental (n = 84) and sibling donors (n = 17), with an ABO/Rh incompatibility rate of 40.59%. Myeloablative conditioning regimens comprised: Ara-C + Bu + Cy + ATG + Me-CCNU in 65 cases, TBI + Cy + ATG ± Me-CCNU ± Flu in 27, Bu + Cy + ATG ± Flu in seven, and Bu + Cy + TT + ATG ± Flu in two. The mean nucleated and CD34+ cell dose infused were 11.06 ± 5.75 × 10⁸/kg and 10.03 ± 5.32 × 10⁶/kg, respectively. All patients achieved successful engraftment with a mean neutrophil engraftment time of 12.72 ± 2.33 days and platelet engraftment time of 12.97 ± 4.37 days. GVHD occurred in 71.28% of cases (aGVHD: 72, cGVHD: 15), predominantly grades I–II, involving skin and gastrointestinal tract. All GVHD cases resolved shortly after supportive management.

DLI information

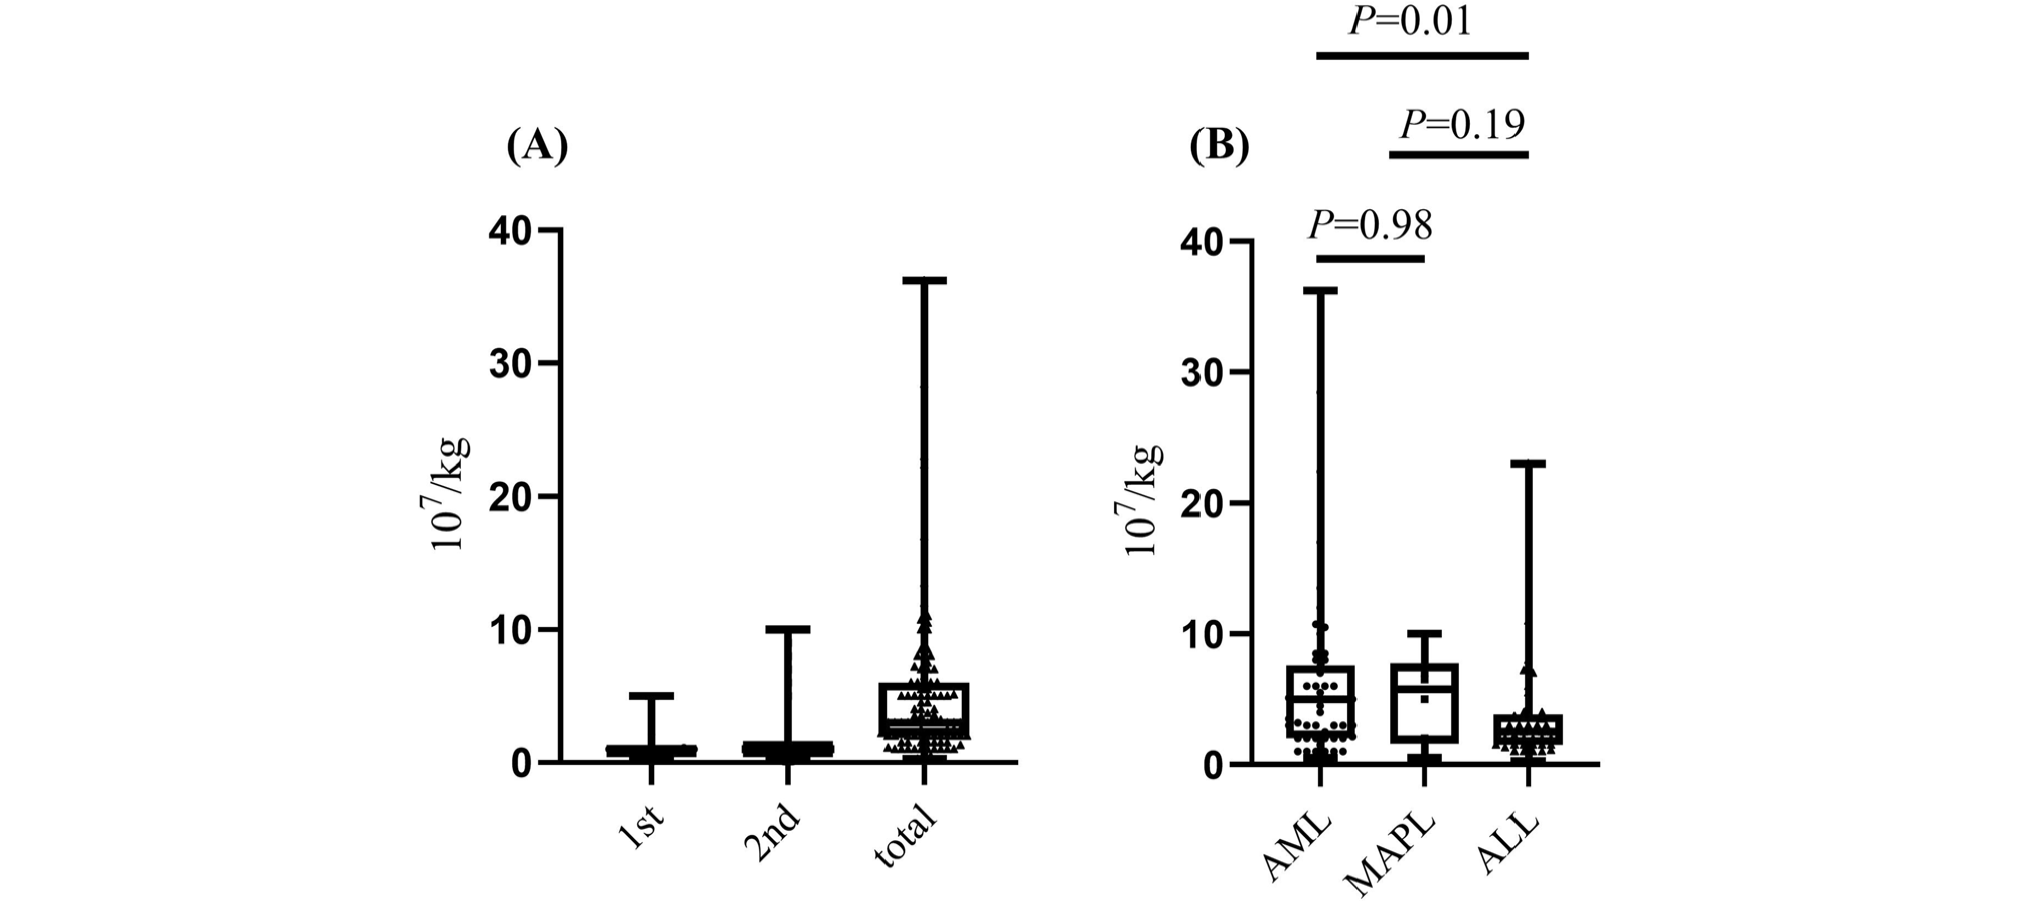
DLI was infused after GVHD disappeared, and immunosuppressive agents were withdrawn. The median time from HSCT to first DLI was 306.26 days (range 51.00–1016.00). The median dose of 1st and 2nd DLI transfusion were 1.00 (0.10–5.00) × 107/kg and 1.00 (0.50–5.00) × 107/kg, respectively. Patients received a median cumulative dose of 5.0 × 10⁷/kg (0.50–36.20), over a median of four DLI transfusion (range 1–20). Patients with AML received higher cumulative DLI doses compared to those of patients with ALL (6.22 × 10⁷/kg (0.50–36.20) vs. 3.51 × 10⁷/kg (0.29–23.00), U = 2.74, P = 0.01). There were no significant differences between AML and MPAL group (6.22 × 10⁷/kg (0.50–36.20) vs. 5.75 × 10⁷/kg (0.50–10.00), U = 0.02, P = 0.98) or ALL and MPAL group (3.51 × 10⁷/kg (0.29–23.00) vs. 5.75 × 10⁷/kg (0.50–10.00), U = 1.32, P = 0.19) (Fig. 1).
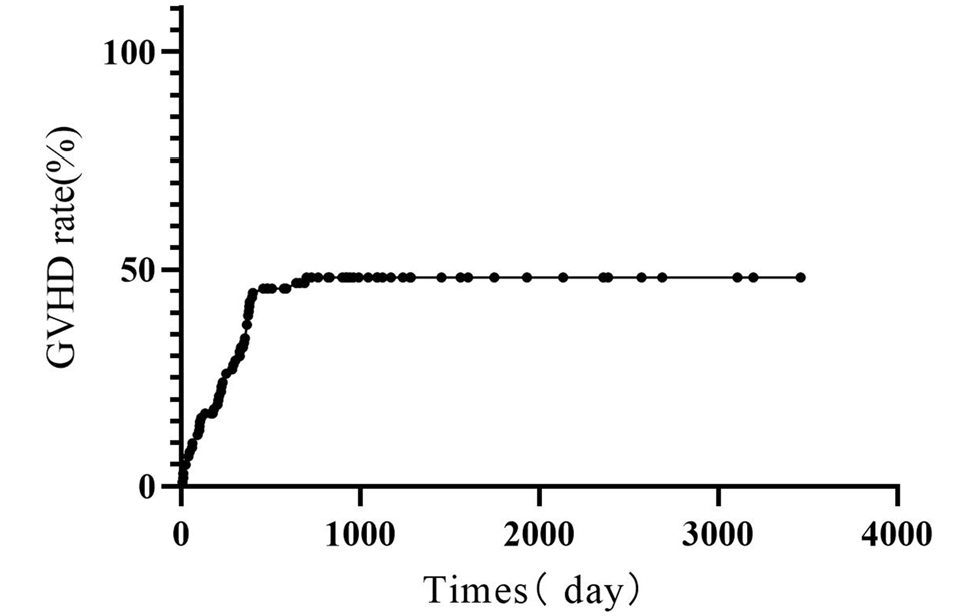
Post-DLI GVHD occurred in 46.53% (47/101) of cases, with median onset at 37.00 days (5.00 patients with 377.00) (Fig. 2). Most events were mild (grade I–II: 42 cases), and severe GVHD (grade III–IV) occurred in only five cases. Post-DLI GVHD primarily involves the skin and mouth. Regarding the GVL effect, some mild GVHD cases did not receive intervention. GVHD resolved after a median duration of 104.00 days (46.00–733.00), with no GVHD-related mortality. GVHD occurred in 57.14% (24/54) of patients with ALL (aGVHD, 14; cGVHD, 10). Most events were mild (grade I–II: 22 cases), and only two were severe GVHD (grade III-IV). In patients with AML, 37.04% (20/54) patients developed GVHD (aGVHD: 18, cGVHD: 2), among which 17 cases were of grades I–II and three cases were of grades II–IV. Among patients with MPAL, 60.00% (3/5) patients developed GVHD (aGVHD: 1, cGVHD: 2); three cases were all of grades I–II. Incidence varied by subtype without statistical significance (χ2 = 3.08, P = 0.21).

Survival analysis

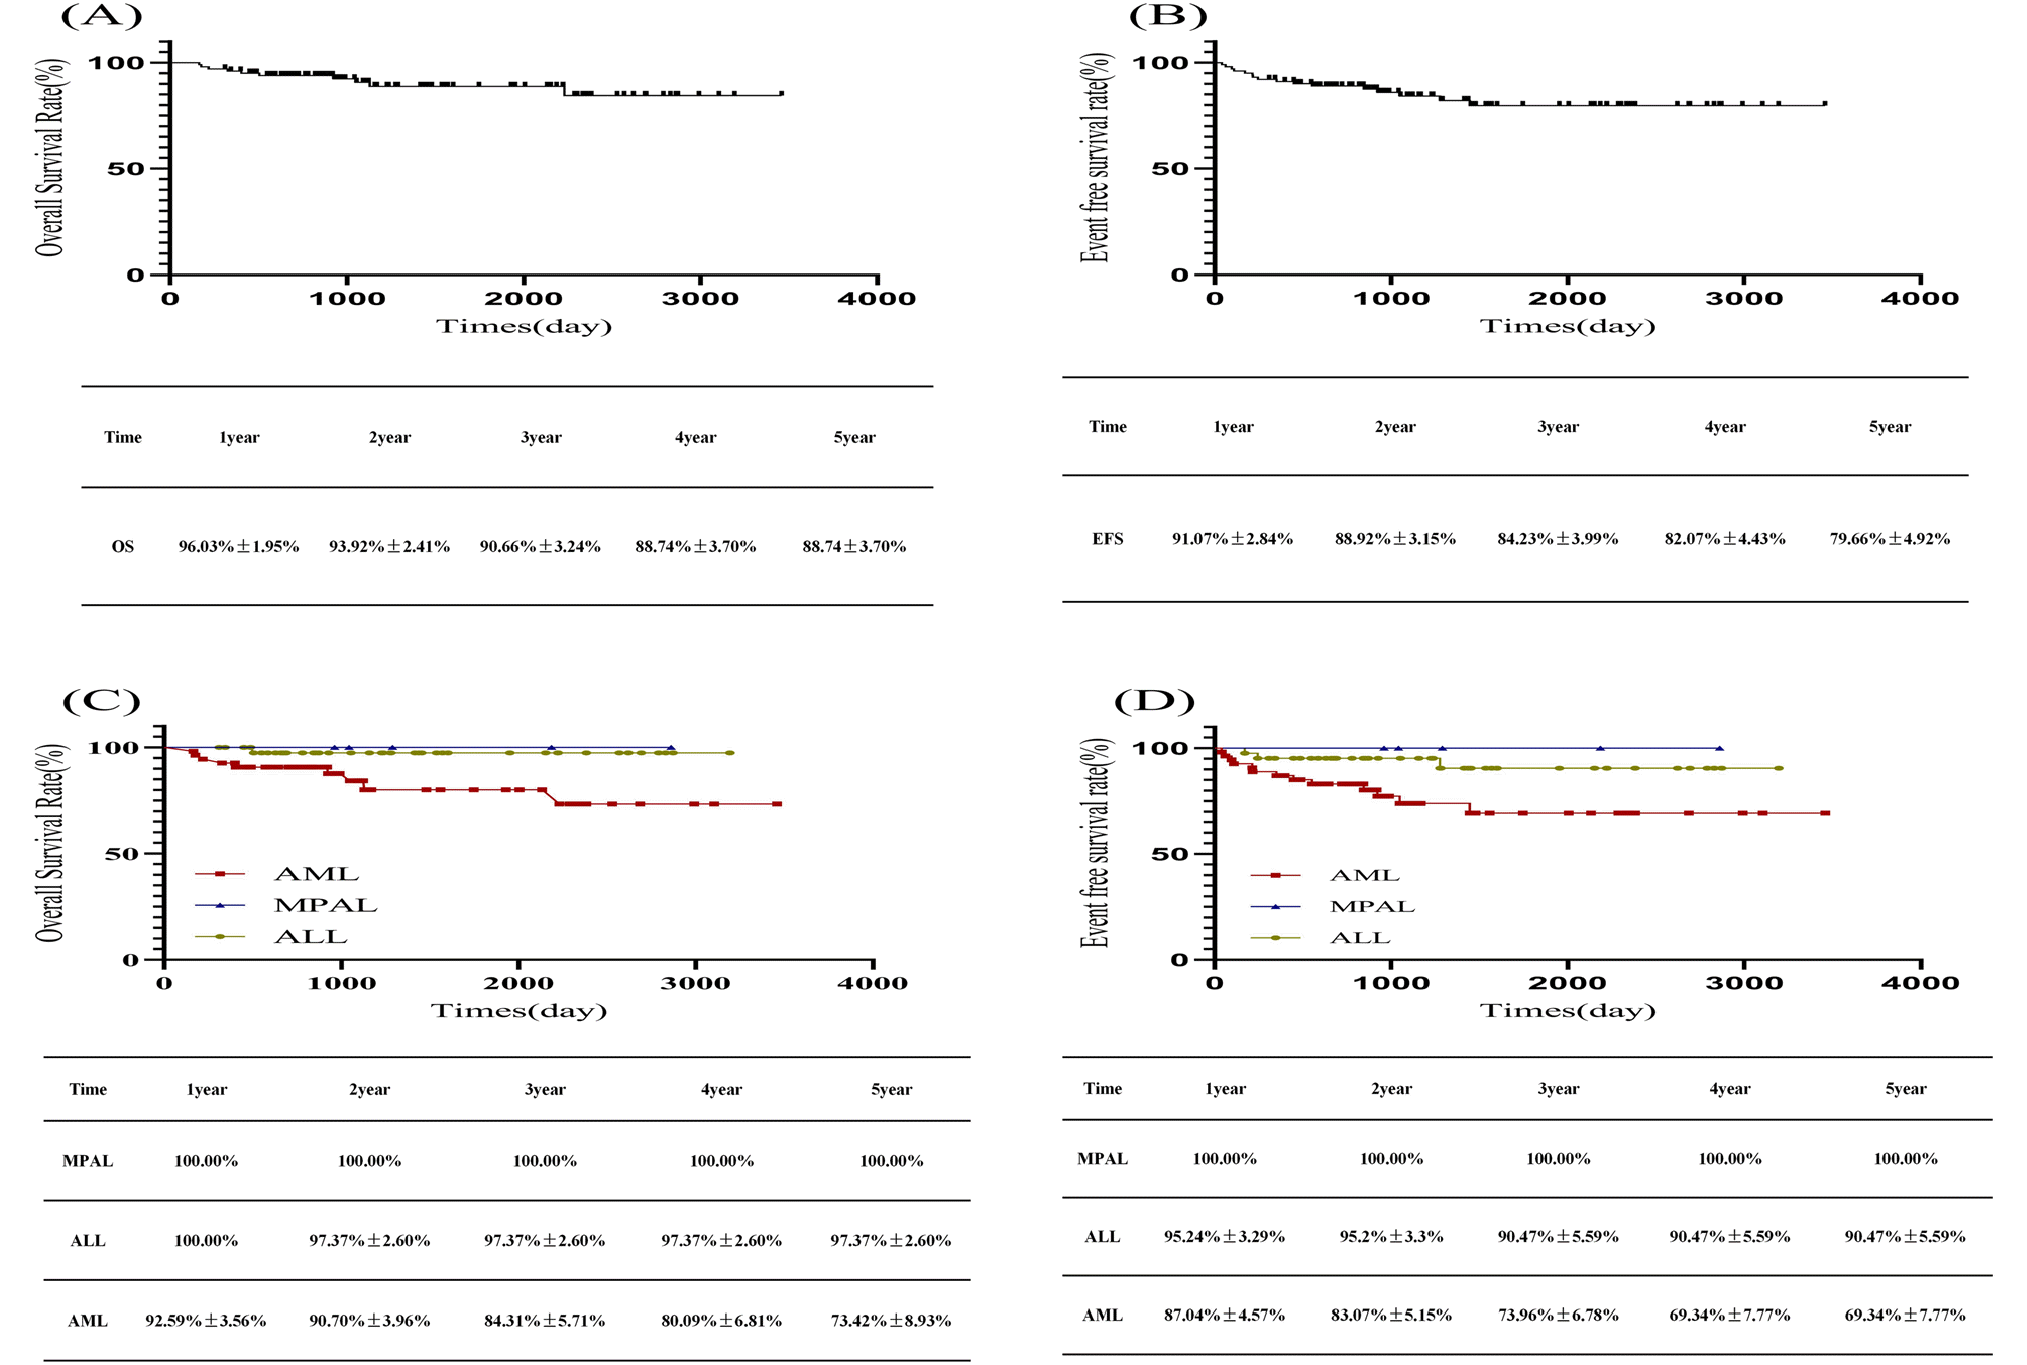
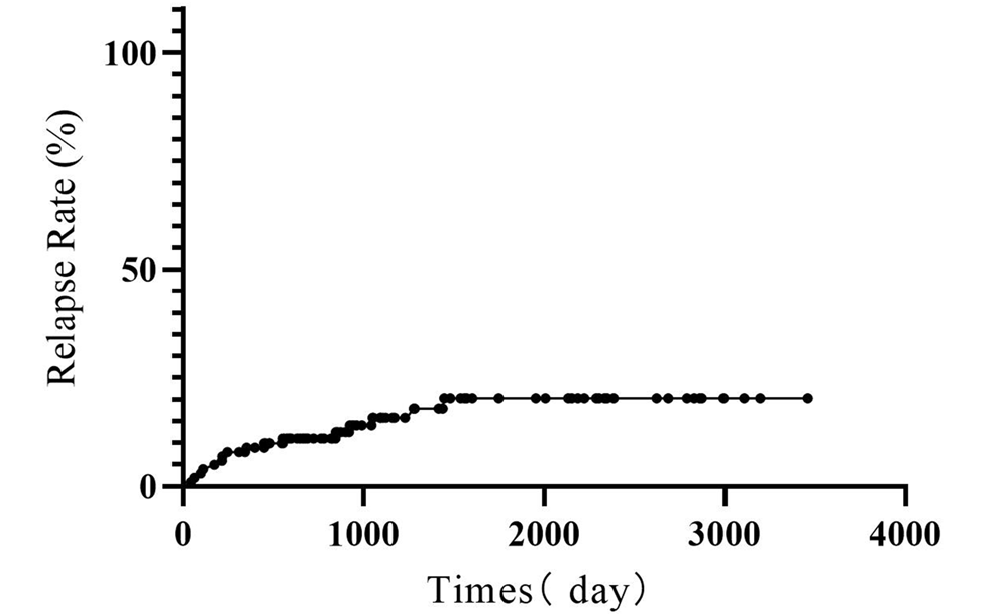
The cohort (n = 101) demonstrated a median post-HSCT follow-up of 1094.00 days (range 163.00–3459.00). Ten deaths occurred in nine patients with AML and one patient with ALL, all of which were attributed to disease progression, including eight patients who relapsed after HSCT. The 3- and 5-year OS rates were 90.66% ± 3.24% and 88.74% ± 3.70%, respectively (Fig. 3A). The 16 relapses included three patients with ALL and 13 patients with AML. The 3- and 5-year EFS rates were 84.23% ± 3.99% and 79.66% ± 4.92%, respectively (Fig. 3B). The cumulative relapse rate was 15.84% (Fig. 4).
The OS and EFS rates of ALL were 97.37% ± 2.60% and 90.48% ± 5.59%, respectively. Patients with AML receiving prophylactic DLI demonstrated significantly inferior EFS compared to those by ALL and MPAL cohorts (69.34% ± 7.77% vs. 90.48% ± 5.59% vs. 100.00%; χ2 = 6.36, P = 0.04) (Fig. 3C). Similarly, AML showed worse OS versus those of the ALL and MPAL groups (73.42% ± 8.93% vs. 97.37% ± 2.60% vs. 100.00%; χ2 = 6.11, P = 0.047) (Fig. 3D).
Among the patients with AML, 13 exhibited recurrence of baseline fusion genes after HSCT. DLI was initiated in these patients at a median of 6 days (range 1–43) after molecular relapse. Post-DLI molecular remission was achieved in nine cases (69.23%), while four maintained persistent positivity, demonstrating DLI’s capacity to induce molecular response in majority of patients with AML with post-transplant fusion gene recurrence. Among the patients with ALL, three exhibited recurrence after HSCT and two remitted after DLI transfusion.
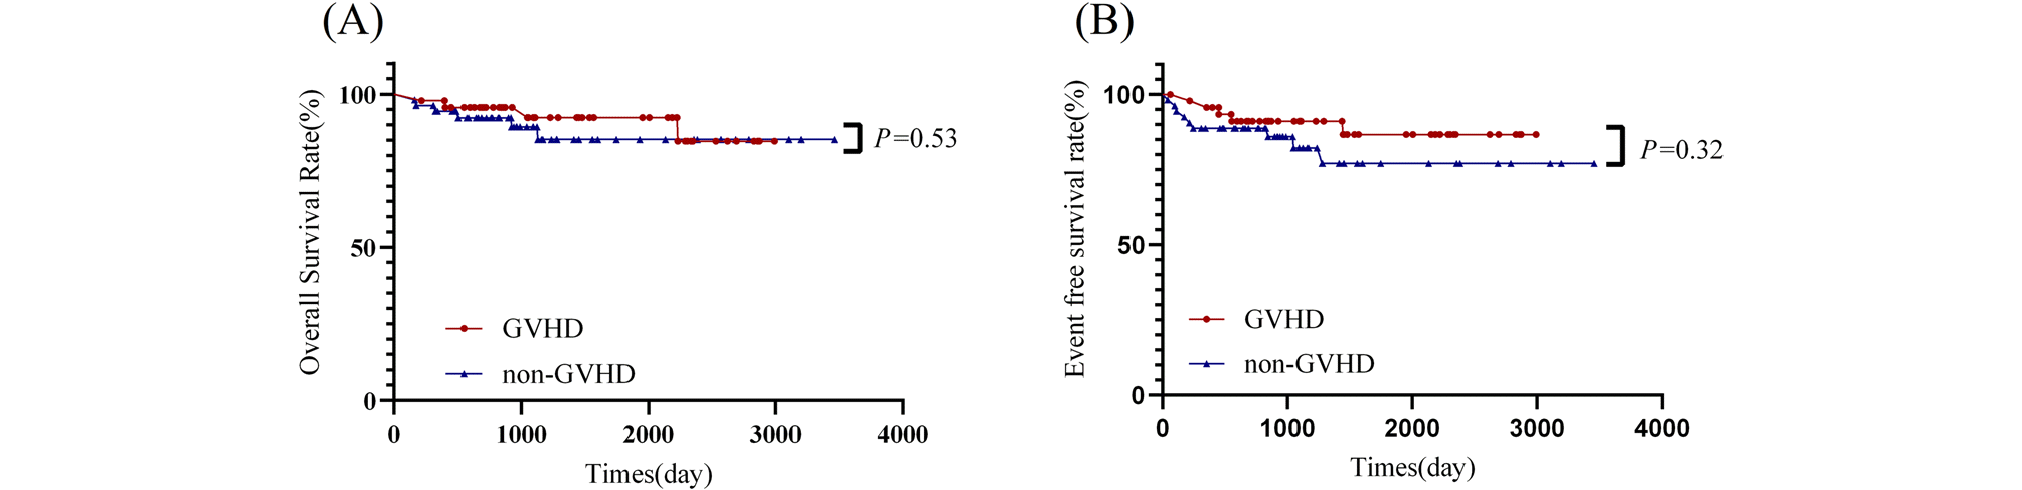
To assess prognostic factors following prophylactic DLI, patients were stratified according to the occurrence of post-DLI GVHD. Our study found that the EFS in patients with GVHD after prophylactic DLI was higher than that in the non-GVHD group, but without statistical significance (84.90% ± 5.87% vs. 74.63% ± 7.73%, χ2 = 0.98, P = 0.32) (Fig. 5B). Moreover, difference in the OS between GVHD group and non-GVHD group was also without statistical significance (85.20% ± 5.91% vs. 84.70% ± 8.37%, χ2 = 0.39, P = 0.53) (Fig. 5A). Receiver operating characteristic (ROC) analysis identified a cumulative DLI dose > 4.75 × 10⁷/kg as predictive of favorable outcomes (AUC 0.67, 95% CI 0.51–0.83, sensitivity 81.3%, specificity 69.4%, P = 0.03). No correlation was observed between the time to the first DLI and prognosis.
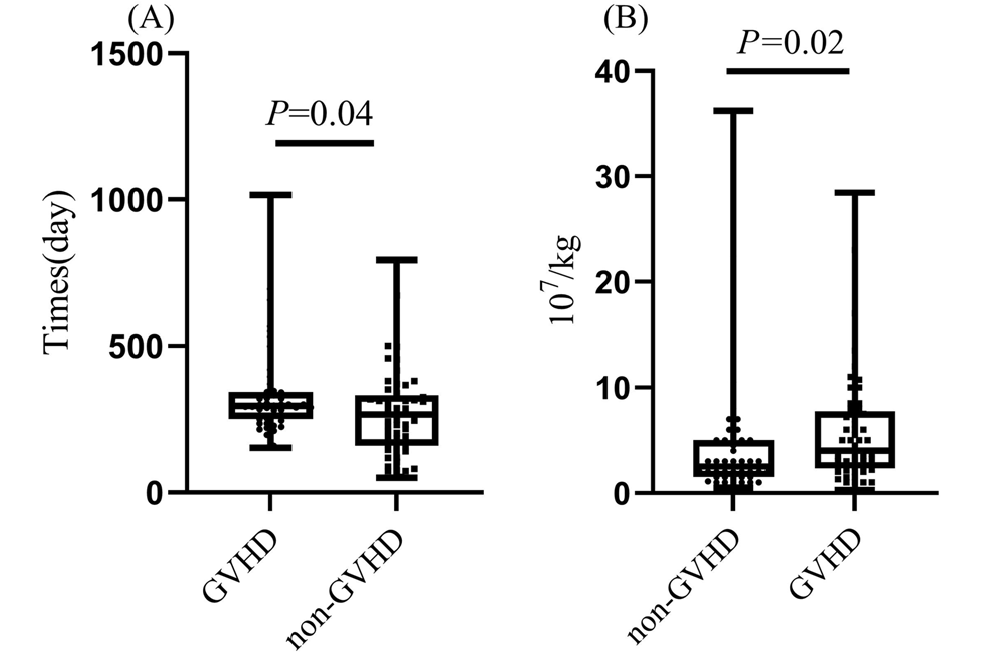
Comparative analysis revealed delayed DLI initiation increased GVHD risk; median time to first DLI was 335.50 days (153.00–1016.00) in patients with GVHD vs. 272.50 days (51.00–793.00) in patients without GVHD (U = 2.00, P = 0.04) (Fig. 6A). However, cumulative DLI dose in patients with GVHD after DLI transfusion were higher than in patients without GVHD (5.73 × 107/kg (0.29–28.44) vs. 4.28 × 107/kg (0.50–36.20), U = 2.39, P = 0.02) (Fig. 6B). The chi-square test demonstrated that patients who had GVHD prior to DLI showed a significantly higher incidence of GVHD post-DLI compared to that of those without prior GVHD (51.90% vs. 27.27%, χ2 = 4.19, P = 0.04).

Discussion

This single-center study investigated the impact of prophylactic DLI following allogeneic HSCT on pediatric AL outcomes, focusing on OS and EFS. Our analysis demonstrated that prophylactic DLI after HSCT significantly improved OS and reduced relapse rates in pediatric patients with AL compared to that in those without prophylactic DLI in the literature [11, 12], which is consistent with previous adult studies showing DLI-enhanced GVL effects [13, 1415]. The mechanism likely involves DLI-mediated GVL effects through donor-recipient histocompatibility antigen disparities, activating donor-derived T/NK cells to eliminate residual leukemic clones. DLI may also restore T-cell function by reversing exhaustion and enhancing T-cell receptor diversity, thereby conferring superior antitumor capacity compared to recipient cells [16].
Notably, while prior studies have predominantly focused on the efficacy of DLI in AML, limited data exist for ALL, particularly pediatric ALL and MPAL. Our cohort included 46 pediatric patients with ALL/MPAL who underwent prophylactic DLI. Strikingly, both OS and EFS reached 100.00% in patients with MPAL, with patients with ALL achieving 97.37% OS. In contrast, despite higher median DLI doses in AML, inferior outcomes persisted (AML 3-year OS and EFS: 73.42% ± 8.93% and 69.34% ± 7.77%, respectively), potentially attributable to both inherent disease aggressiveness and reduced DLI sensitivity in AML. However, we need to pay attention to the fact that OS and EFS in patients with AML who received prophylactic DLI reach quite promising values of approximately 70%.
Differential responsiveness may be related to immunophenotypic profiles; ALL blasts expressing high CD19/CD22 levels may enhance recognition by DLI-induced immune effectors [17]. The biphenotypic nature of MPAL may increase alloantigen exposure and amplify GVL responses. These findings suggest that prophylactic DLI should be considered for high-risk patients with AL who undergo allogeneic HSCT, regardless of the subtype, to improve EFS. Emerging studies combining azacitidine/lenalidomide with DLI show promise for enhanced GVL induction, although the limited sample sizes necessitate further investigation [18, 1920].
Although DLI mitigates the risk of leukemia relapse, it also increases the incidence of GVHD. However, literature on prophylactic DLI and GVHD outcomes in pediatric patients is limited. We observed a substantial incidence of any grade GVHD (46.53%) following prophylactic DLI compared with rates previously described. Bader et al [21] reported that 51.6% of 31 pediatric patients with ALL developed aGVHD following prophylactic DLI transfusion. In a comparable study, only 22% of 35 children with AL developed GVHD after receiving prophylactic DLI post-haploid HSCT [22]. Similarly, findings from Rujkijyanont et al. demonstrated a 26% incidence of GVHD in patients with myeloid malignancy treated with prophylactic DLI [23]. A large retrospective study on EBMT analyzed the outcomes of 173 patients with hematological malignancies treated with DLI after allogeneic HSCT. The rates of grade II–IV acute GVHD and chronic GVHD rates were 20–21% and 17–24%, respectively [13, 19]. The relatively high incidence of GVHD observed in our cohort following prophylactic DLI may be correlated with the CD3+ lymphocyte doses. Previous reports typically utilized DLI doses of 104–10⁶/kg, whereas this study employed a median dose of 5.00 (range 0.50–36.20) × 10⁷/kg. Notably, although a high incidence of GVHD was observed after DLI in this study, most cases were mild-to-moderate in severity. This favorable clinical profile allows for effective GVL activity, resulting in significantly reduced relapse rates among patients with AL post transplantation. It is also crucial to consider the transfusion dose. To the best of our knowledge, this study is the first to demonstrate through retrospective analysis that a cumulative DLI dose > 4.75 × 10⁷/kg was predictive of favorable outcomes. This finding underscores the need to strike a balance between the effects of GVL and GVHD risk.
Reportedly, GVHD of any grade post-DLI is significantly associated with a lower risk of relapse [20]. Our findings demonstrated no prognostic impact of post-DLI GVHD development, suggesting that prophylactic DLI may exert potent GVL effects without inducing GVHD or with only mild manifestations. This observation could also be influenced by heterogeneous treatment protocols, a limited sample size, or confounding factors in our cohort, necessitating validation with larger clinical datasets. Additionally, neither the DLI cell dose nor disease type significantly affected the incidence of GVHD in this study. We observed a low risk of DLI administration in the early post-transplantation period. Our data indicate that 9 months before HSCT, continuing with DLI is safe, with minimal GVHD risk. Therefore, the incidence of GVHD after early DLI post-transplantation was not significantly higher than that after late DLI. The discrepancy between this study and previous reports might be attributed to the prophylactic administration of anti-GVHD agents post-transplantation, which potentially suppresses GVHD development following early DLI [22]. Our study also demonstrated that patients who developed GVHD before DLI had a significantly higher incidence of GVHD post-DLI compared to that of those without prior GVHD. This study suggests that in pediatric patients who develop or have severe GVHD after HSCT, DLI following the discontinuation of immunosuppressive therapy should be approached with greater caution because of the potentially higher risk of GVHD. In this study, the GVHD episodes post-DLI were transient and mild, with no GVHD-related mortality, supporting the safety of prophylactic DLI following allogeneic HSCT.
This study had some limitations. First, as a retrospective analysis, this investigation may be subject to selection bias. Second, this was a single-center, pre-post design without a matching analysis. Future studies should incorporate larger sample sizes and adopt prospective designs to further validate the findings of this study.

Conclusion

Our preliminary results suggest that post-HSCT maintenance therapy with prophylactic DLI in the pediatric setting is feasible and safe, and may contribute to improved event-free survival. Although the limitations of our study include its single-center, retrospective, and pre-post design without matching analysis because of the small sample size, these results support further studies on post-HSCT maintenance therapy in clinical trial settings.

Acknowledgements

We thank all the patients and their families for their kind cooperation. We thank all the members of the clinical team who provided care to the patients.

Notes

Authors’ contributions

YHL and AW designed and performed the literature search and drafted the manuscript. YBW, GHZ, CGJ, JY, JZ, MZ, and YFJ analyzed the data, and verifed and discussed the studies. YHL and MQQ amended the paper, designed the research, proofread the manuscript, supervised and approved the study.

Funding

This work was supported by the Beijing Natural Science Foundation (No. 7254351).

Data availability

The data that support the findings of this study are available on request from the corresponding author.

Declarations

Ethics approval and consent to participate

This study was conducted in accordance with the Declaration of Helsinki and approved by the Institutional Review Board (IRB) of Beijing Children’s Hospital, Capital Medical University. Informed consent to participate in the study was obtained from the parents or legal guardians of children under 16 years of age.

Competing interests

The authors declare no competing interests.

Publisher’s Note

Springer Nature remains neutral with regard to jurisdictional claims in published maps and institutional affiliations.

References

1. Kolb HJ. Graft-versus-leukemia effects of transplantation and donor lymphocytes. Blood. 2008; 112(12):4371–4383. DOI: 10.1182/blood-2008-03-077974. PMID: 19029455.
2. Creutzig U, van den Heuvel-Eibrink MM, Gibson B, et al. Diagnosis and management of acute myeloid leukemia in children and adolescents: recommendations from an international expert panel. Blood. 2012; 120(16):3187–3205. DOI: 10.1182/blood-2012-03-362608. PMID: 22879540.
3. Hasle H. A critical review of which children with acute myeloid leukaemia need stem cell procedures. Br J Haematol. 2014; 166(1):23–33. DOI: 10.1111/bjh.12900. PMID: 24749666.
4. Lucchini G, Labopin M, Beohou E, et al. Impact of conditioning regimen on outcomes for children with acute myeloid leukemia undergoing transplantation in first complete remission. An analysis on behalf of the pediatric disease working party of the European Group for Blood and Marrow Transplantation. Biol Blood Marrow Transplant. 2017; 23(3):467–474. DOI: 10.1016/j.bbmt.2016.11.022. PMID: 27916512.
5. Rovatti PE, Gambacorta V, Lorentino F, Ciceri F, Vago L. Mechanisms of leukemia immune evasion and their role in relapse after haploidentical hematopoietic cell transplantation. Front Immunol. 2020; 11:147. DOI: 10.3389/fimmu.2020.00147. PMID: 32158444. PMCID: 7052328. PMID: f7f3e159ce3945388ae637cd8cf85315.
6. Kolb HJ, Schattenberg A, Goldman JM, et al. European Group for Blood and Marrow Transplantation Working Party Chronic Leukemia Graft-versus-leukemia effect of donor lymphocyte transfusions in marrow grafted patients. Blood. 1995; 86(5):2041–2050. DOI: 10.1182/blood.V86.5.2041.bloodjournal8652041. PMID: 7655033.
7. Dholaria B, Savani BN, Labopin M, et al. Clinical applications of donor lymphocyte transfusion from an HLA-haploidentical donor: consensus recommendations from the acute leukemia working party of the EBMT. Haematologica. 2020; 105(1):47–58. DOI: 10.3324/haematol.2019.219790. PMID: 31537691. PMCID: 6939532. PMID: c78e0176ca4848d983f2814ad0142a70.
8. Jedlickova Z, Schmid C, Koenecke C, et al. Long-term results of adjuvant donor lymphocyte transfusion in AML after allogeneic stem cell transplantation. Bone Marrow Transplant. 2016; 51(5):663–667. DOI: 10.1038/bmt.2015.234. PMID: 26437060.
9. Harris AC, Young R, Devine S, et al. International, multicenter standardization of acute graft-versus-host disease clinical data collection: a report from the Mount Sinai Acute GVHD International Consortium. Biol Blood Marrow Transplant. 2016; 22(1):4–10. DOI: 10.1016/j.bbmt.2015.09.001. PMID: 26386318.
10. Jagasia MH, Greinix HT, Arora M, et al. National Institutes of Health consensus development project on criteria for clinical trials in chronic graft-versus-host disease: I. the 2014 diagnosis and staging working group report. Biol Blood Marrow Transplant. 2015; 21(3):389–401.e1. DOI: 10.1016/j.bbmt.2014.12.001. PMID: 25529383.
11. Tian J, Wei A, Wang B, et al. Allogeneic hematopoietic stem cell transplantation for pediatric acute lymphoblastic leukemia. Ann Hematol. 2024; 103(1):297–305. DOI: 10.1007/s00277-023-05506-w. PMID: 37991510.
12. He H, Li J, Li W, et al. Clinical features and long-term outcomes of pediatric patients with de novo acute myeloid leukemia in China with or without specific gene abnormalities: a cohort study of patients treated with BCH-AML 2005. Hematology. 2024; 29(1):2406596. DOI: 10.1080/16078454.2024.2406596. PMID: 39361146. PMID: 715ad85e678145d39a1564a0dfb98e29.
13. Santoro N, Mooyaart JE, Devillier R, et al. Donor lymphocyte infusions after haploidentical stem cell transplantation with PTCY: a study on behalf of the EBMT cellular therapy &amp; immunobiology working party. Bone Marrow Transplant. 2023; 58(1):54–60. DOI: 10.1038/s41409-022-01839-8. PMID: 36216975.
14. Tsirigotis P, Byrne M, Schmid C, et al. Relapse of AML after hematopoietic stem cell transplantation: Methods of monitoring preventive strategies A review from the ALWP of the. EBMT Bone Marrow Transpl. 2016; 51(11):1431–1438. DOI: 10.1038/bmt.2016.167.
15. Dominietto A, Pozzi S, Miglino M, et al. Donor lymphocyte infusions for the treatment of minimal residual disease in acute leukemia. Blood. 2007; 109(11):5063–5064. DOI: 10.1182/blood-2007-02-072470. PMID: 17522340.
16. Orti G, Barba P, Fox L, Salamero O, Bosch F, Valcarcel D. Donor lymphocyte infusions in AML and MDS: enhancing the graft-versusleukemia effect. Exp Hematol. 2017; 48:1–11. DOI: 10.1016/j.exphem.2016.12.004. PMID: 28027963.
17. Maude SL, Laetsch TW, Buechner J, et al. Tisagenlecleucel in children and young adults with B-cell lymphoblastic leukemia. N Engl J Med. 2018; 378(5):439–448. DOI: 10.1056/NEJMoa1709866. PMID: 29385370. PMCID: 5996391.
18. Minculescu L, Reekie J, Petersen SL, et al. Donor lymphocyte infusion is a feasible way to improve survival in patients with acute myeloid leukemia and myelodysplastic syndromes who relapse after allogeneic stem cell transplantation. Acta Haematol. 2024; 147(3):325–332. DOI: 10.1159/000534315. PMID: 37827141.
19. Huschart E, Miller H, Salzberg D, et al. Azacitidine and prophylactic donor lymphocyte infusions after hematopoietic stem cell transplantation for pediatric high-risk acute myeloid leukemia. Pediatr Hematol Oncol. 2021; 38(2):154–160. DOI: 10.1080/08880018.2020.1829220. PMID: 33150833.
20. Chandar R, Meena S, Varla H, et al. Post-transplant strategies to improve relapse-free survival in childhood leukemia: whole blood donor lymphocyte infusions and lenalidomide for inducing graft-versus-leukemia effect. Pediatr Transplant. 2022; 26(5):e14293. DOI: 10.1111/petr.14293. PMID: 35437875.
21. Bader P, Kreyenberg H, et al. Increasing mixed chimerism is an important prognostic factor for unfavorable outcome in children with acute lymphoblastic leukemia after allogeneic stem-cell transplantation: possible role for pre-emptive immunotherapy. J Clin Oncol. 2004; 22(9):1696–1705. DOI: 10.1200/JCO.2004.05.198. PMID: 15117992.
22. Liou A, Wahlstrom JT, Dvorak CC, Horn BN. Safety of pre-emptive donor lymphocyte infusions (DLI) based on mixed chimerism (MC) in peripheral blood or bone marrow subsets in children undergoing hematopoietic stem cell transplant (HSCT) for hematologic malignancies. Bone Marrow Transplant. 2017; 52(7):1057–1059. DOI: 10.1038/bmt.2017.45. PMID: 28394367.
23. Rujkijyanont P, Morris C, Kang G, et al. Risk-adapted donor lymphocyte infusion based on chimerism and donor source in pediatric leukemia. Blood Cancer J. 2013; 3(8):e137. DOI: 10.1038/bcj.2013.39. PMID: 23995046. PMCID: 3763390.

Fig. 1
DLI transfusion condition. The median dose of 1st and 2nd DLI transfusion were 1.00 (0.10–5.00) × 107/kg and 1.00 (0.50–5.00) × 107/kg, respectively. Patients received a median cumulative dose of 5.00 × 10⁷/kg (0.50–36.20) (Figure A). Patients with AML received higher cumulative DLI doses compared to patients with ALL (P = 0.01). No significant differences emerged between patients with AML and MPAL (P = 0.98) or patients with ALL and MPAL (P = 0.19) (Figure B). Note: DLI, Donor lymphocyte infusions; AML, acute myeloid leukemia; MPAL, mixed-phenotype acute leukemia
br-61-1-f1.tif
Fig. 2
Complication situation. The cumulative post-DLI GVHD rate was 46.53%. Note: DLI, Donor lymphocyte infusions; GVHD: Graft versus host disease
br-61-1-f2.tif
Fig. 3
Survival analysis. The 3- and 5-year OS rates were 990.66% ± 3.24% and 88.74% ± 3.70%, respectively after prophylactic DLI transfusion (Figure A). And the 3- and 5-year EFS rates were 84.23% ± 3.99% and 79.66% ± 4.92%, respectively (Figure B). Patients with AML receiving prophylactic DLI demonstrated significantly inferior EFS compared to that by ALL and MPAL cohorts (69.34% ± 7.77% vs. 90.48% ± 5.59% vs. 100.00%; χ2 = 6.36, P = 0.04) (Figure C). Similarly, AML showed worse OS versus those of ALL and MPAL groups (73.42% ± 8.93% vs. 97.37% ± 2.60% vs. 100.00%; χ2 = 6.11, P = 0.047) (Figure D). Note: OS, overall survival; EFS: event-free survival; DLI, Donor lymphocyte infusions; AML, acute myeloid leukemia; MPAL, mixed-phenotype acute leukemia
br-61-1-f3.tif
Fig. 4
Relapse after pro-DLI. The 5-year cumulative relapse rate was 15.84%
br-61-1-f4.tif
Fig. 5
Correction between GVHD after prophylactic DLI and survival rate. The EFS in patients with GVHD after prophylactic DLI was higher than that of the non-GVHD group, but without statistical significance (84.90% ± 5.87% vs. 74.63% ± 7.73%, χ2 = 0.98, P = 0.32) (Figure B). Moreover, there was no statistically significant difference in OS between the GVHD and non-GVHD group (85.20% ± 5.91% vs. 84.70% ± 8.37%, χ2 = 0.39, P = 0.53) (Figure A). Note: DLI, Donor lymphocyte infusions; GVHD: Graft versus host disease
br-61-1-f5.tif
Fig. 6
Risk factors of GVHD after DLI. Delayed DLI initiation increased GVHD risk (335.50 days (153.00–1016.00) vs. 272.50 days (51.00–793.00), P = 0.04) (A). Cumulative DLI dose was correlated with GVHD incidence (5.73 × 107/kg (0.29–28.44) vs. 4.28 × 107/kg (0.50–36.20), P = 0.02) (B). Note: DLI, Donor lymphocyte infusions; GVHD: Graft versus host disease
br-61-1-f6.tif
Table 1
Characteristics of the patients
Characteristics
ALL (N = 42)
MAPL (N = 5)
AML (N = 54)
Sex
 Male (%)
25(59.52%)
4(80.00%)
36(66.67%)
 Fusion gene positive (%)
22(52.38%)
3(60.00%)
47(87.04%)
Status at transplantation
 CR1(%)
27(64.29%)
4(80.00%)
47(87.04%)
 CR2(%)
15(35.71%)
1(20.00%)
6(11.11%)
 MRD+(%)
0
0
1(1.85%)
Donor type
 Father(%)
29(69.05%)
2(40.00%)
38(70.37%)
 Mother(%)
6(14.28%)
2(40.00%)
7(12.96%)
 Sibling(%)
7(16.67%)
1(20.00%)
9(16.67%)
Conditioning Regimen
 TBI + Cy + ATG ± Me-CCNU ± Flu(%)
13(30.95%)
0
14(25.92%)
 Bu + Cy + ATG ± Flu(%)
2(4.76%)
1(20.00%)
4(7.41%)
 Ara-C + Bu + Cy + ATG + Me-CCNU(%)
25(59.52%)
4(80.00%)
36(66.67%)
 Bu + Cy + TT + ATG ± Flu(%)
2(4.76%)
0
0
Number of stem cell
 MNC (108/kg)
8.53(4.92–31.14)
7.29(4.9–20.14)
9.04(5.18–25.38)
 CD34+ (106/kg)
9.39(5.48–18.46)
9.58(8.11–15.10)
9.01(1.96–51.43)
 HLA matched
3(7.14%)
1(20.00%)
6(11.11%)
TOOLS
Similar articles