



 PDF
 Citation
 Print


Introduction
Chronic lymphocytic leukemia (CLL)/small lymphocytic lymphoma (SLL) is a lymphoproliferative disorder characterized by the clonal expansion and accumulation of mature CD5-positive B lymphocytes within the blood, bone marrow (BM), and secondary lymphoid organs.
Although CLL is the most prevalent type of leukemia in Western countries, comprising approximately 25–30% of leukemia cases in the United States [1], it has been relatively rare in Korea. Recent epidemiologic data, however, indicate a significant rise in the incidence of CLL in Korea, with an annual percentage increase of 4.17% from 1999 to 2010 compared to just 0.68% in the US during the same period [2].
The rarity of CLL in Korea has historically limited hematologists’ opportunities to gain extensive clinical experience in managing this disease. This, in turn, may hinder familiarity with contemporary diagnostic tools and novel treatment strategies. Despite recent advancements in therapeutic options, including the approval of targeted agents such as ibrutinib and zanubrutinib, realworld treatment practices in Korea often diverge from international guidelines. A recent multicenter retrospective study revealed that among 141 Korean patients diagnosed with CLL/SLL between 2010 and 2020, fludarabine, cyclophosphamide, and rituximab (FCR) were used most frequently as first-line therapy (46.8%), followed by chlorambucil (19.9%) and obinutuzumab plus chlorambucil (12.1%) [3]. These findings suggest the persistent reliance on conventional chemoimmunotherapy, reflecting limited adoption of novel agents due to sparse real-world evidence, constrained clinical exposure, and insurance reimbursement barriers.
In Korea, ibrutinib was reimbursed for relapsed/refractory CLL beginning in 2018, but first-line reimbursement was only granted in September 2023. Zanubrutinib was subsequently approved for first- or second-line use in June 2024. Delays in reimbursement and restricted access have likely contributed to suboptimal utilization of these agents, with potential implications for patient outcomes. Therefore, understanding Korean hematologists’ current decision-making processes, perceptions, and perceived barriers in CLL management is essential to bridging the gap between local practice and global standards. The present nationwide survey aims to assess these factors, providing insights to inform strategies for optimizing CLL diagnosis and treatment in the Korean context.
Patients and methods
Study design
This study was a nationwide online questionnaire survey conducted among hematologists treating CLL in Korea.
The questionnaire was developed and reviewed by members of the Korean Lymphoma Working Party (KLWP), a subgroup of the Korean Society of Hematology (KSH); those involved in its development and review were not eligible to participate in the main survey. The survey was performed from May 29 to June 19, 2023, and was coordinated by the KLWP. Participants included hematologists registered with the KSH who were actively involved in the clinical management of CLL. A total of 89 hematologists completed the survey and were included in the analysis. The survey was administered via an online platform provided by the KLWP, ensuring participant anonymity and confidentiality.
Survey content
The questionnaire comprised 15 structured items designed to capture insights into clinical experience, treatment approaches, utilization of Bruton tyrosine kinase inhibitor (BTKi), familiarity with clinical guidelines, and perceived challenges in the management CLL.
Initial questions focused on current clinical practices, including the number of CLL patients managed over the past six months, the proportion receiving active treatment, and whether there were patients who required but did not receive therapy, along with the reasons for such undertreatment. Items related to BTKi use explored the proportion of patients previously treated with these agents, as well as physicians’ perceptions of the key limitations or concerns associated with their use. To assess awareness and implementation of prognostic tools, respondents were queried about their use of the CLL–International Prognostic Index (CLL-IPI) and the International Prognostic Score for Early-stage CLL (IPS-E). Additional questions addressed the timing of BM examinations and imaging studies during the disease course. Diagnostic and therapeutic challenges were further examined by assessing the availability and application of immunoglobulin heavy-chain variable region gene (IGHV) mutation testing, TP53 aberration assessment, and minimal residual disease (MRD) monitoring. Respondents were then asked to indicate which firstline therapies should be prioritized for reimbursement in Korea, selecting from options including ibrutinib, second-generation BTKi, venetoclax, or other regimens. Finally, participants were asked whether there is a need for Korea-specific clinical guidelines for the diagnosis and treatment of CLL. The full questionnaire is available in the Online Supplement (Supplementary data 1).
Results
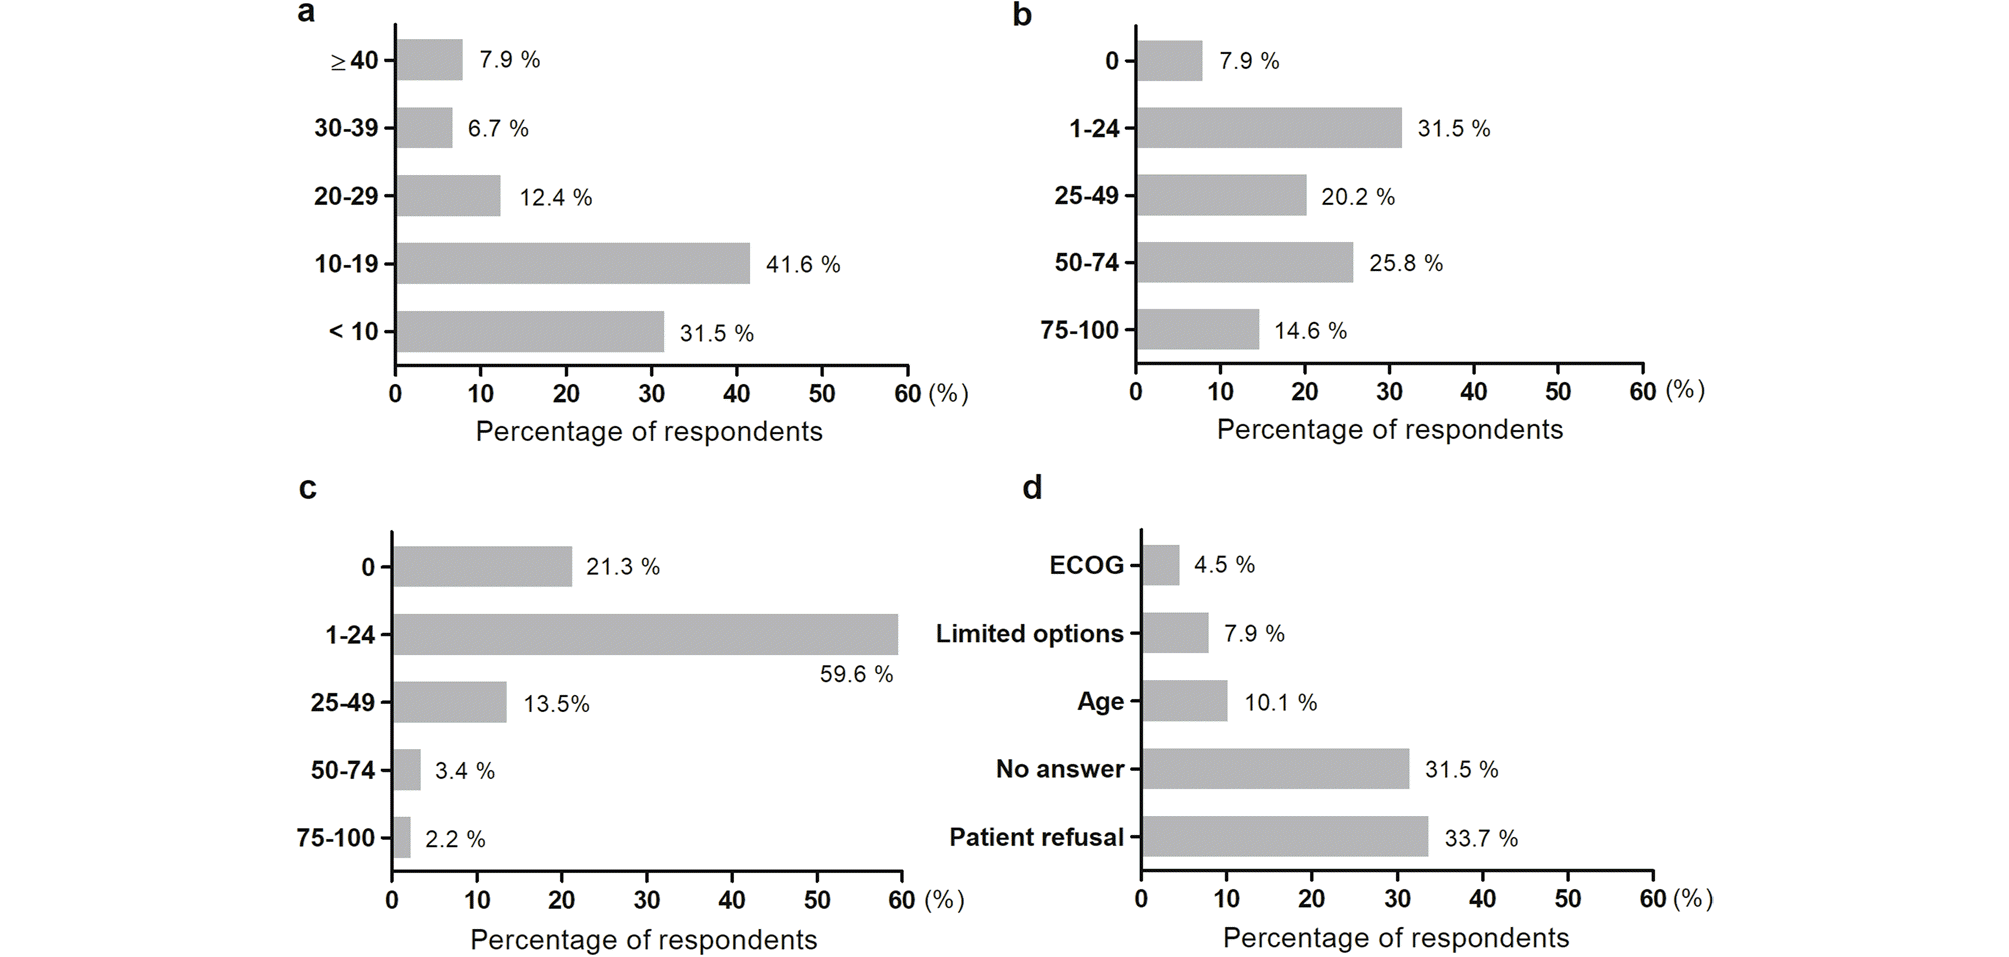
Among the 89 hematologists who participated in the nationwide survey, the number of CLL patients managed in the preceding six months varied widely (Fig. 1a). The most frequently reported patient volume was 10–19 patients, cited by 41.6% of respondents (n = 37). A further 31.5% (n = 28) reported managing fewer than 10 patients. Higher patient volumes were less common: 12.4% (n = 11) managed 20–29 patients, and 6.7% (n = 6) managed 31–39. Notably, 7 hematologists reported treating over 40 patients, including one who managed more than 100 and another who reported over 200 CLL patients during this period (data not shown).
Reports on the proportion of each clinician’s patient population actively receiving therapy exhibited substantial heterogeneity (Fig. 1b). Although the most frequently reported category was 1–24% of patients treated, a notable subset of clinicians indicated treatment rates between 50–74%, with responses spanning the entire spectrum—from 0% to ≥ 75%—highlighting considerable variability across clinical practices.
Patients who met treatment criteria but were not receiving therapy were commonly observed, though they generally represented a small proportion of the patient population, most often within the 1–24% range (Fig. 1c). Physicians reported multiple reasons for not initiating treatment, as multiple responses were permitted (Fig. 1d). The most frequently cited reason was patient refusal (33.7%), followed by advanced patient age (10.1%), unavailability of appropriate therapeutic options (7.9%), and poor performance status (4.5%). Less commonly reported factors (each < 5%) included asymptomatic disease, financial limitations, coexisting medical conditions, unfavorable prognosis, drug hypersensitivity, and long distance from the treatment center. Notably, approximately one-third of respondents did not specify a reason. This non-response may reflect the multifactorial nature of treatment decisions, difficulties in attributing undertreatment to a single predominant factor, or variability in interpretation of treatment indications.
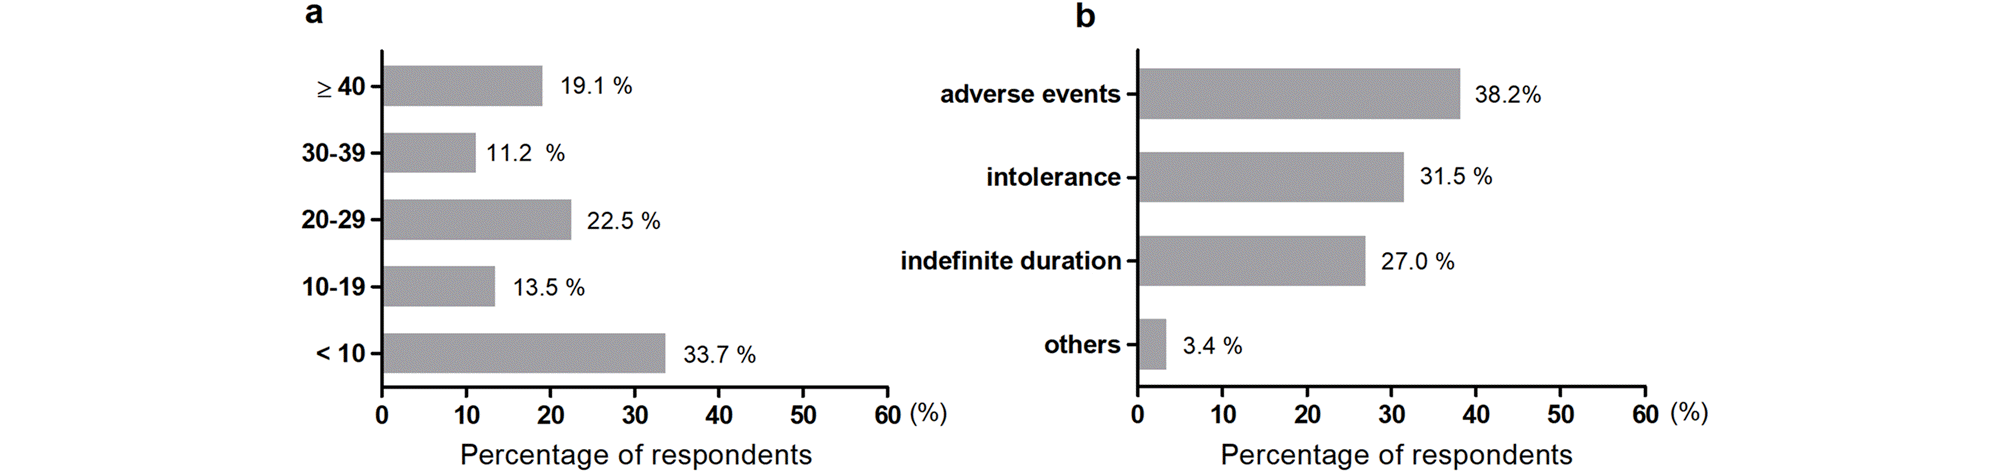
At the time of the survey, BTKis were not reimbursed as first-line therapy in Korea, although partial reimbursement was available in the relapsed or refractory setting. Despite this limitation, exposure to BTKi was relatively work-up, many clinicians still reported performing these tests at diagnosis. These findings indicate that, while prognostic indices were broadly recognized, their routine uptake remained inconsistent, and the timing of imaging and BM examinations was heterogeneous across practices.
Access to essential molecular and prognostic assays—integral to pretreatment risk stratification and therapeutic decision-making—varied substantially across participating institutions (Fig. 4). TP53 testing was broadly available, most frequently conducted via fluorescence in situ hybridization (FISH) alone (29%), next-generation sequencing (NGS) alone (24%), or a combination of both methods (30%); only 3% of centers reported lacking access. In contrast, IGHV mutation analysis was not available in over half of the centers surveyed (53%). MRD assessment was not performed in 43% of institutions; among centers with testing capacity, 31% utilized flowcytometry alone, 18% employed NGS-based assays (e.g., clonoSEQ), and 8% implemented both modalities. These findings highlight an uneven landscape of molecular testing access, where TP53 assays are relatively well integrated, yet the limited availability of IGHV and MRD testing may hinder the delivery of risk-adapted, guideline- concordant care in Korean practice.
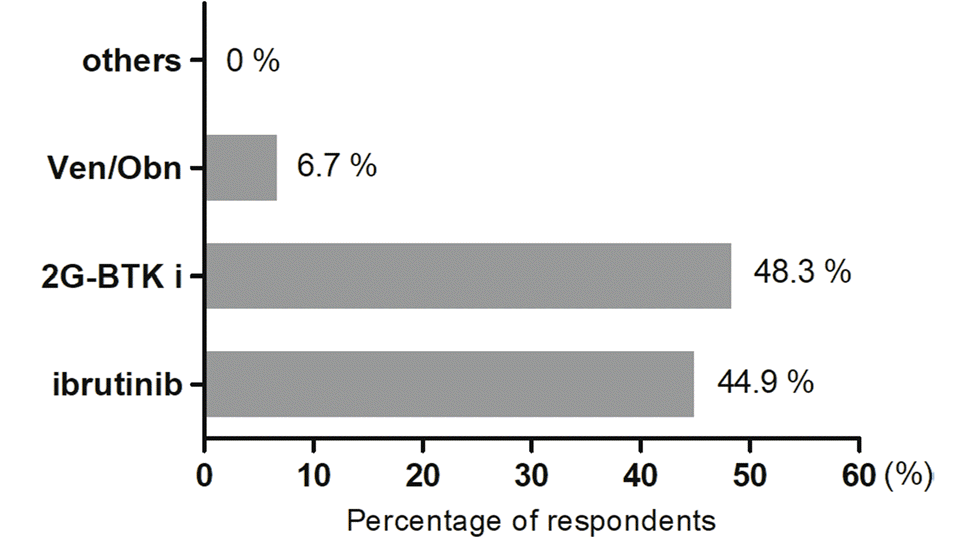
When asked which front-line regimen should be reimbursed with the highest priority, nearly half of physicians selected a second-generation BTKi (48.3%), followed closely by ibrutinib (44.9%) (Fig. 5). Venetoclax-based first-line therapy—defined in this survey as the venetoclax + obinutuzumab regimen—was chosen by only 6.7%, and no respondents selected other options. These findings indicate that Korean hematologists most strongly favored broader reimbursement of BTKi, with a preference for second-generation agents over first-generation ibrutinib.
Finally, respondents were asked whether dedicated national guidelines for the diagnosis and treatment of CLL should be developed in Korea. A striking 94.4% of hematologists answered affirmatively, underscoring a strong consensus for the need to establish Korean-specific guidelines that reflect local epidemiology, diagnostic accessibility, and reimbursement environments.
Discussion
This nationwide survey is the first to assess the clinical patterns and perceptions of Korean hematologists regarding CLL management. Although CLL remains relatively rare in Korea, its incidence is gradually rising, underscoring the growing need for accurate diagnosis and evidence-based treatment. Our survey revealed variability in treatment practices, with instances of undertreatment frequently influenced by patient preferences and specific clinical contexts in Korea. Furthermore, while Korean hematologists are aware of prognostic indices and novel therapies at a conceptual level, their consistent application in clinical decision-making remains limited, reflecting gaps in diagnostic access and practice integration.
A notable finding from our survey was the considerable heterogeneity in treatment rates among Korean hematologists. The proportion of each clinician’s CLL population actively receiving therapy varied widely, from none to more than 75%, with most respondents reporting that only a small fraction of their patients required treatment (Fig. 1b). Nevertheless, undertreatment was observed even among patients who met accepted indications (Fig. 1c). Physicians most frequently attributed this to patient refusal, advanced age, or the absence of suitable therapeutic options, whereas less common explanations included comorbidities, financial limitations, or geographic barriers (Fig. 1d). However, as the undertreatment-related question was an open-ended item without asking respondents to specify the underlying reasons, factors contributing to patient refusal or the perception of limited therapeutic options could not be definitively identified. This limits the depth of interpretation, as important considerations—such as concerns about toxicity, the burden of continuous therapy, financial barriers, or logistical challenges—may not have been comprehensively captured. These observations highlight how, beyond guideline-defined criteria, real-world treatment decisions are shaped by a complex interplay of patient preferences, physician judgment, and healthcare system constraints, ultimately contributing to variability in care delivery.
Although first-line reimbursement was unavailable during the study period, BTKis have been widely used in real-world practice in Korea. Clinicians reported that clinical issues—specifically AEs, treatment intolerance, and the requirement for indefinite therapy—were considered to be more significant barriers than cost (Fig. 2). In an exploratory subgroup comparison of physicians with high (≥ 40%) versus minimal (< 10%) BTKi exposure, both groups identified adverse events as the predominant pitfall (47.1% and 56.7%, respectively, data not shown) suggesting a shared perception that toxicity is the principal barrier to BTKi use, irrespective of clinical experience level. Similar trends were reported from Japan, where 82.2% of hematologists chose BTKis as their first-choice first-line treatment, with the rationale being strong clinical evidence (61.4%) and ease of administration (56.8%) with substantial out-of-pocket costs and no regimen endpoint as the main factors controlling treatment choices [4]. Comparable trends have been seen in the United States, where real-world data show a shift toward next-generation BTKis, based on improved tolerability, increased physician comfort around safety, and acknowledgment of cardiovascular toxicities as an important trade-off with ibrutinib [5].
Importantly, our survey further revealed that Korean hematologists overwhelmingly regarded second-generation BTKi as the therapeutic class most in need of reimbursement expansion (Fig. 5), reflecting both their familiarity with ibrutinib’s toxicity profile and the perceived safety advantages of newer agents, consistent with evidence from pivotal trials such as ELEVATE-RR and ALPINE [6, 7]. By contrast, venetoclax and obinutuzumab received relatively low prioritization in Korea, despite compelling trial data demonstrating high efficacy and durable remissions [8]. This finding is most plausibly attributable to reimbursement restrictions under the Korean National Health Insurance system, which, during the study period, limited venetoclax use to relapsed or refractory settings. These policy constraints likely limited both physician familiarity and practical access to venetoclax in the front-line setting. While logistical challenges— such as the need for inpatient monitoring during dose ramp-up and the risk of tumor lysis syndrome—may contribute to hesitancy in clinical adoption, reimbursement limitations appear to be the predominant factor influencing respondents’ prioritization in our survey.
Awareness of prognostic indices such as the IPS-E and the CLL-IPI was virtually universal among Korean hematologists, with 93.3% and 100% reporting familiarity, respectively. Their integrated adoption into daily practice, however, was much lower (Fig. 3a–b). Of note, this difference does not appear to reflect a lack of physician awareness but rather institutional limitations in the availability of requisite diagnostic tools, which restrict their systematic application. In addition, our data showed significant heterogeneity regarding the timing of BM evaluations and radiographic staging studies (Fig. 3c–d). Notably, although international guidelines explicitly state that bone marrow biopsy and imaging studies are not routinely required for the initial diagnostic work-up of CLL [9–11], a substantial proportion of Korean hematologists reported performing these procedures at diagnosis. While our survey did not assess the underlying rationale for this practice, and no prior studies have systematically examined it, bone marrow examination is often conducted in Korea to support documentation required for insurance approval processes. This administrative factor may contribute to the observed discrepancy between guideline recommendations and real-world practice.
Although these results reflect deficiencies in prognostic index application and traditional diagnostic evaluation, the most notable discrepancy may be the availability of molecular testing. IGHV mutation testing was unavailable in more than half of centers, and MRD assessment was lacking in 43%. Testing for TP53, in contrast, was widely performed. As IGHV and MRD tests are critical for risk stratification for treatment choice and prognostic estimations, their lack poses a significant limitation. Indeed, the Surveillance, Epidemiology, and End Results Patterns of Care analysis in the US highlighted similar limitations in the adoption of molecular testing: IGHV mutation status was assessed in fewer than 20% of cases, MRD evaluation was largely restricted to academic centers, and IGHV testing was recommended but ultimately not performed in nearly 40% of eligible patients, indicating that these disparities are not specific to Korea [12]. Regional Asian data also support the underuse of molecular testing in routine practice, reflecting a challenging issue of translating recommendations into real-world practice [13].
In addition, although TP53 testing was widely accessible across centers, the survey did not ask whether physicians incorporated 17p deletion or TP53 mutation into first-line BTKi selection. As a result, genotype-guided therapeutic decision making—an increasingly important component of modern CLL management—could not be evaluated. This represents an additional limitation of the survey design and may underestimate the extent to which Korean clinicians individualize treatment on the basis of high-risk genomic features.
Finally, the overwhelming response (94.4% of responding hematologists) that Korean-specific guidelines are needed highlights the limitations of direct adoption of western standards. While international guidelines provide high-level recommendations, their applicability is constrained by local realities such as low disease prevalence, diagnostic test availability, and insurance coverage. Importantly, regional expert consensus statements from the Asia–Pacific, including those by the Asia–Pacific Leukemia Consortium, have emphasized the importance of developing contextually relevant treatment strategies that align with available healthcare infrastructure and economic constraints, while still harmonizing with global standards [10]. Epidemiological and clinical data also support that it is crucial to adopt region-specific strategies. The frequency of CLL in the East Asian population is over 20-fold lower than that in the Western population [2, 14, 15]. Korean patients often present with atypical immunophenotypes such as strong surface Ig expression, FMC7 positivity, and weak or absent CD23, and these features have been associated with a relatively aggressive clinical course. In that cohort, patients with atypical immunophenotype had a significantly shorter time-totreatment and inferior survival, with 5-year OS of 61.3% compared with 84.5% in those with typical immunophenotype (p = 0.045), highlighting the prognostic significance of these biologic distinctions [16]. Differences in disease biology and clinical patterns between Asian and Western patients indicate that Western treatment frameworks may not fully meet the needs of Asian populations. These variations highlight the need for local clinical studies to refine strategies that reflect Korea’s epidemiology and practice environment.
Moreover, developing Korean-specific guidelines would help standardize care while ensuring equitable, evidencebased treatment. Their role would be to bridge the gap between international recommendations and the practical constraints of the Korean healthcare system—including limitations in diagnostic infrastructure, variability in test availability, and reimbursement policies. By distinguishing minimal essential from optimal recommended testing and proposing reimbursement-aligned treatment pathways, these guidelines would support consistent, equitable, and evidence-based clinical decision-making across diverse practice settings in Korea.
In conclusion, Korean hematologists were well informed about prognostic tools and novel agents but were not able to overcome the barriers to apply guideline- based diagnostic tests and new treatment strategies because of structural and compensation limitations. The broad consensus on the need for Korean-specific guidelines highlights the urgent need to establish standardized, locally adapted recommendations to optimize CLL care. These findings provide critical groundwork for developing national strategies that bridge the gap between global standards and the realities of Korean clinical practice.


 XML Download