



 PDF
 Citation
 Print


Introduction
Conventional external-beam radiotherapy delivers a relatively uniform dose across the target volume, with modern techniques emphasizing geometric conformality and the sparing of normal tissues [1-4]. However, in bulky, hypoxic, or inherently radioresistant tumors—and in re-irradiation settings—normal-tissue tolerance often limits dose escalation, necessitating trade-offs between tumor control and toxicity [5]. Spatially fractionated radiation therapy (SFRT) represents an alternative paradigm that employs non-uniform dose delivery through multiple narrow beamlets or localized high-dose vertices [1-4]. This approach generates a dose distribution characterized by high-dose peaks alternating with low-dose valleys. By distributing dose spatially—and in some approaches temporally—SFRT can enhance the therapeutic index, allowing high peak doses to target tumors while using valley regions to preserve normal-tissue function and support biological recovery [6-10].
In the following sections, we describe the major SFRT modalities and summarize key radiobiological mechanisms. We also review clinical and preclinical evidence and discuss essential medical physics considerations, including dosimetry, dose reporting, and quality assurance (QA). Finally, we highlight ongoing challenges and outline future research priorities for clinical translation.
Current Delivery Methods
Among the four SFRT modalities, GRID and Lattice therapy have been clinically implemented on standard linacs, whereas minibeam radiation therapy (MBRT) and microbeam radiation therapy (MRT) remain primarily preclinical due to small-field dosimetry challenges and limited source availability.
1. GRID therapy
GRID therapy represents the earliest clinical implementation of SFRT [2,5,8]. Historically delivered using perforated screens and later with megavoltage linear accelerators, GRID generates a two-dimensional (2D) sieve pattern of pencil-beam openings across a large treatment field. Contemporary approaches include: (1) custom brass or Cerrobend blocks mounted on the linear accelerator (linac) head; (2) multileaf collimator-based step-and-shoot patterns; (3) helical tomotherapy or volumetric-modulated arc therapy (VMAT)-based virtual grids; and (4) proton GRID delivered using pencil-beam scanning [5,8]. Typical physical patterns feature openings approximately 1–2 cm in diameter with 2–4 cm center-to-center spacing, yielding low peak-to-valley dose ratios (PVDRs ~2–5). These characteristics represent the coarsest SRFT modulation and reflect its role as a clinically deployed, palliative or priming technique. In practice, GRID is often delivered as a single high-dose fraction (often 10–20 Gy) either before or after a course of conventional radiotherapy. Its key advantages include conceptual simplicity, broad compatibility with existing linacs, and short commissioning times. Its limitations include depth-dependent dose attenuation and limited three-dimensional (3D) selectivity, as peak regions inevitably pass by superficial tissues on their way to deep targets [2,5-8].
2. Lattice therapy
Lattice therapy extends spatial fractionation into three dimensions. Within the gross tumor volume, multiple spherical high-dose regions, or “vertices,” are planned and delivered while maintaining lower doses in the tumor periphery and surrounding normal tissues [6,7,9]. Vertex diameters typically range from 1–2 cm, with a spacing of 2–4 cm. This parameter selection parallels that of GRID but extends modulation into three dimensions. Lattice therapy is commonly delivered using VMAT, intensity-modulated radiotherapy (IMRT), or tomotherapy. It can serve as a priming regimen, with single or a few fractions (e.g., 15–20 Gy to the vertices) administered before conventionally fractionated therapy [10]. Lattice plans are generated by defining spherical high-dose vertices within the GTV and optimizing VMAT/IMRT arcs to deliver ≥15–20 Gy to these vertices while keeping peripheral doses in the surrounding tumor and adjacent organs at risk substantially lower. Typical implementations use 2−4 highly modulated arcs. Several published planning workflows, including VMAT-based GRID/Lattice approaches, provide detailed examples of vertex placement and dose-painting strategies [11].
Variants include metabolism-guided vertex placement, such as at interfaces between high- and low-uptake regions on fludeoxyglucose-18 positron emission tomography, as well as simultaneous integrated Lattice boosts incorporated into conventional plans. Compared with GRID, Lattice therapy provides improved 3D dose conformity, avoids superficial hotspots, and maintains higher modulated intratumoral dose distributions [12,13].
In clinical practice, implementing GRID or Lattice therapy requires several workflow steps beyond those used in conventional IMRT and VMAT. These steps include selecting an appropriate spatial modulation scale, verifying peak-valley patterns in the treatment planning systems (TPS), and performing additional dosimetric QA to confirm vertex placement and dose heterogeneity. However, the overall clinical workflow for patient setup and treatment delivery largely parallels that of standard IMRT and VMAT therapy.
3. Minibeam radiation therapy
MBRT employs arrays of narrow beams with sub-millimeter widths (~0.5–1.0 mm) and 1–4 mm spacing, producing moderate spatial modulation with typical PVDRs of 10–20 [14-18]. MBRT has been investigated using both X-rays and charged particles. X-ray MBRT typically employs static or modular collimators, whereas proton and heavy-ion MBRT can, in principle, leverage magnetic focusing or dynamic collimation to enhance flexibility and delivery efficiency [15,18]. Preclinical studies have demonstrated remarkable normal-tissue tolerance, with peak doses of up to 50–100 Gy causing no loss of function. Tumor control is maintained or even improved compared with uniform-beam irradiation at the same mean dose. Clinical implementation requires careful consideration of small-field dosimetry, beam alignment tolerances, and overall deliverability [5-10,19].
4. Microbeam radiation therapy
MRT represents the extreme of spatial dose modulation, employing micro-planar beams approximately 50–100 μm wide and spaced 200–400 μm apart, achieving very high PVDRs (>50) [14-16,19]. To preserve the microbeam pattern through tissue, MRT requires high dose rates and low-divergence beams, which are typically available only at synchrotron facilities. In rodents and large-animal models, MRT enables peak entrance doses of several hundred gray while remarkably sparing normal tissues, particularly in the central nervous system (CNS) [19]. Technical challenges, including source availability, micrometer-scale beam modeling and dosimetry, and integration into clinical workflows, remain the principal barriers to clinical translation, although the development of compact sources continues to advance [14-16]. Since their beam widths are below 1 mm, MBRT and MRT necessitate small-field dosimetry, which involves high-resolution film, microdiamond detectors, and Monte Carlo dose calculation. This requirement sets them apart from SFRT modalities currently used in clinical practice.
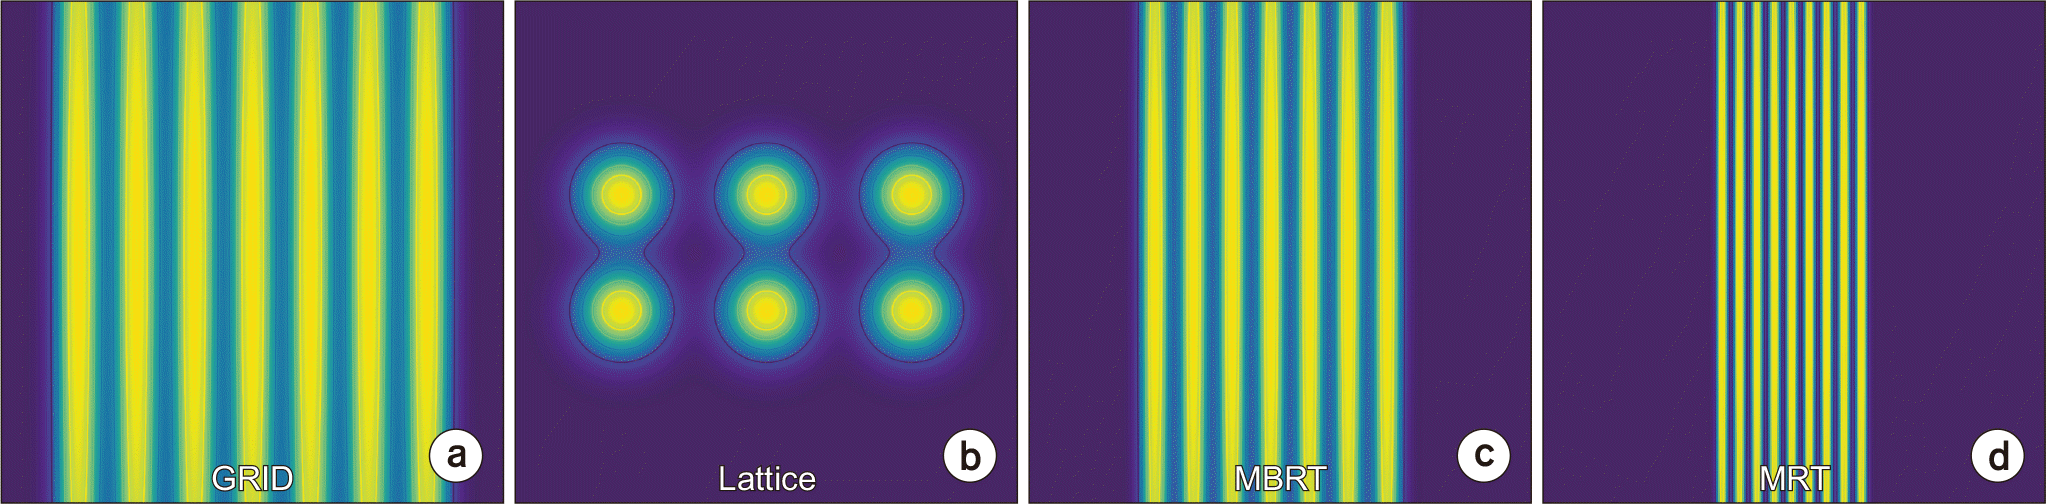
Table 1 summarizes the SFRT techniques—GRID therapy, Lattice therapy, MBRT, and MRT—along with their characteristic geometric and dosimetric parameters. These parameter ranges are commonly selected because they balance achievable mechanical accuracy with biological objectives. For clinical GRID and Lattice applications, larger beam widths and lower PVDRs are sufficient. In contrast, MBRT and MRT use narrow beams and high PVDRs to enhance normal-tissue sparing, as demonstrated in preclinical studies. Fig. 1 provides an overview comparing the spatial patterns of four SFRT techniques.
Radiobiology
The biological effects of SFRT extend beyond direct clonogenic cell kill to encompass tissue-level and systemic responses. Multiple, non-exclusive mechanisms likely act synergistically [12,13,20].
1. Dose-volume and tissue-sparing effects
Narrow, high-dose peaks spare a critical fraction of normal parenchyma within valleys. Surviving functional units and stem/progenitor cells can repopulate the irradiated regions, supporting organ tolerance at peak doses that would otherwise be prohibitive.
2. Vascular responses
High-dose peaks preferentially damage immature tumor vasculature while relatively sparing mature vessels in normal tissues. This can create transient permeability windows and promote vascular remodeling, which may enhance drug delivery and facilitate immune cell trafficking.
3. Immunomodulation
SFRT can function as an in-situ vaccine. High-dose peaks induce immunogenic cell death and promote neoantigen release, while the valleys preserve resident immune cells and facilitate rapid infiltration. Enhanced CD8+ T-cell recruitment and improved tumor control in immunocompetent models support a distinct immune contribution.
4. Bystander and abscopal effects
Cytokines, danger signals, and intercellular communication can trigger responses in unirradiated tumor regions (bystander effects) as well as in distant lesions (abscopal effects). In multiple preclinical models, partial-volume irradiation has produced greater systemic control than uniform irradiation at equivalent mean doses.
5. Biochemical mediators
Spatial gradients of reactive oxygen species (e.g., H₂O₂) and redox signaling are thought to contribute to both tumor control and immune priming. However, definitive in vivo validation and precise quantification of these effects remain active areas of investigation.
Substantial MRT and MBRT animal data support dose–volume sparing and selective vascular preservation. In contrast, effects such as immune activation, bystander and abscopal signaling, and modulation by biochemical mediators remain largely hypothesis-generating and may vary across modalities. For example, in rodent CNS models, MRT can deliver peak entrance doses exceeding 300–600 Gy while preserving neurological function, illustrating the remarkable normal-tissue sparing observed under high PVDR conditions.
Clinical and Preclinical Application
Clinical experience with SFRT currently focuses on GRID and Lattice therapy, primarily for large, symptomatic, or radioresistant tumors. Institutional series have reported single-fraction GRID or Lattice doses in the range of 10–20 Gy. When delivered at higher doses or as hypofractionated regimens followed by conventional radiotherapy, SFRT can achieve high rates of symptom relief and promising local control, all while maintaining acceptable toxicity profiles [2,5]. Emerging prospective efforts, including stereotactic Lattice boosts and protocolized vertex prescriptions, aim to standardize SFRT delivery and determine benefit beyond those observed in historical controls [8,19]. In addition to single-fraction GRID and Lattice boosts, several centers have adopted multi-fraction Lattice schedules or stereotactic Lattice boosts (SABR-Lattice) reflecting increasing variability in clinical implementation [21,22]. Several single-institution clinical studies have reported high symptom-relief rates (60%−90%), early tumor shrinkage in bulky tumors, and acceptable toxicity profiles following single-fraction GRID or Lattice boosts of 1−20 Gy. For instance, Huhn et al. [8]. reported marked symptom improvement in 80% of patients with advanced neck disease, while Amendola et al. [9] observed favorable local control in large non-small cell lung tumors treated using Lattice therapy. Although prospective comparative trials remain limited, these numerical outcomes suggest a meaningful therapeutic benefit compared with historical controls [8,9].
Preclinical studies, particularly in MRT and MBRT, provide mechanistic insights and proof-of-principle for widening the therapeutic window. In brain and sarcoma models, MBRT and MRT demonstrate remarkable normal-tissue sparing at peak doses several-fold higher than those tolerated with uniform beams. They achieve tumor control that is equal to or superior to comparable average doses [1-4]. Notably, pooled analyses of single-fraction animal studies indicate that valley dose and the fraction of tumor volume directly irradiated correlate more strongly with outcome than peak dose alone. These findings underscore the importance of both reporting and ultimately optimizing spatial dosimetry parameters in clinical studies.
Medical Physics Aspects of Spatially Fractionated Radiation Therapy
1. Dosimetry and quality assurance
For GRID and Lattice techniques, centimeter-scale modulation patterns can generally be modeled using conventional TPS algorithms commissioned for stereotactic body radiation therapy or stereotactic radiosurgery. These patterns can be accurately modeled, with verification using 2D or 3D dosimeters (e.g., film, electronic portal imaging device-based QA, or diode arrays) [11]. In contrast, MBRT/MRT involves sub-millimeter beamlets, extending dosimetry into the small-field regime beyond standard clinical practice [21,22]. The sub-millimeter beams used in MBRT and MRT violate the lateral charged-particle equilibrium assumptions of conventional algorithms, necessitating small-field commissioning and Monte Carlo simulations. Film remains the reference standard for relative dosimetry, provided issues related to dynamic range and scanner uncertainty are carefully managed [23]. While film offers high spatial resolution, practical limitations—including scanner non-uniformity, dose-saturation at high peaks, and energy dependence—must be addressed. Micro-diamond and other solid-state detectors are well suited for point measurements, whereas dedicated complementary metal–oxide–semiconductor systems can capture high-frequency spatial dose profiles [24,25]. For dose calculation, Monte Carlo-based dose engines with fine voxelization and appropriately defined transport thresholds are recommended to ensure accurate modeling of steep dose gradients [11,25].
GRID/Lattice fields, which feature centimeter-scale apertures, can be commissioned using standard stereotactic datasets. In contrast, MBRT/MRT, with sub-millimeter beamlet widths, require dedicated small-field commissioning, high-resolution detectors, and Monte Carlo validation.
2. Dose reporting and prescription
In SFRT, dose reporting should extend beyond conventional dose–volume histogram (DVH) metrics to include spatial parameters that characterize the modulation pattern. These parameters include beam or vertex width, center-to-center spacing, peak dose, valley dose, and the PVDR [1,2,26]. Historically, dose prescriptions were often based on the peak entrance or depth-of-maximum dose, a practice inherited from early GRID therapy [26]. Peak and valley doses are typically measured using high-resolution film or microdetectors, and the PVDR is calculated from line-profile analyses of the microbeam or minibeam arrays. However, radiobiological evidence and preclinical studies indicate that the valley dose and the proportion of tumor volume directly irradiated may more accurately predict both treatment response and toxicity. Equivalent uniform dose models should be applied with caution, as they do not fully capture non-targeted effects, such as immune activation [1-4]. The development of new metrics and radio-immune models that connect spatial dose distributions to immune recruitment and tumor control is warranted.
3. Planning and delivery considerations
Practical planning principles include: (1) selecting a modulation scale that is appropriate for the tumor size and its proximity to organs at risk; (2) ensuring robust beam/vertex placement to account for setup and motion uncertainties; (3) validating TPS calculations against experimental measurements for the chosen technique; and (4) documenting SFRT-specific spatial parameters alongside standard DVH metrics. For proton or heavy-ion SFRT, beam scanning and energy selection can confine dose peaks to the target while reducing both proximal and distal valley doses compared with photon beams [21,27-29]. Nevertheless, the sensitivity of particle beams to range uncertainty, tissue heterogeneity, and alignment errors requires careful consideration in robustness analyses.
Future Research
Key near-term priorities include: (1) establishing consensus standards for SFRT plan reporting and clinical outcome documentation, encompassing modulation scale, PVDR, valley dose, directly irradiated tumor fraction, and relevant immune or vascular biomarkers; (2) conducting prospective, indication-specific clinical trials that compare standardized GRID/Lattice priming regimens with the best available conventional therapies; (3) conducting correlative studies that integrate spatial dosimetry with immune phenotyping and advanced imaging; (4) developing and validating fast, accurate dose calculation engines and optimization frameworks tailored to MBRT, MRT, and particle-based SFRT; and (5) designing rational combinations of SFRT with systemic therapies, particularly immunotherapies, guided by mechanistic models. Translation efforts should prioritize workflow simplification and QA harmonization to support SFRT implementation across a broad range of clinical settings.
 XML Download