



 PDF
 Citation
 Print


Introduction
Brachytherapy is a form of radiation-based cancer treatment in which radioactive sources are inserted into or attached directly to the body, in contrast to external beam radiation therapy. This technique enables the delivery of highly localized radiation to the tumor site, thereby minimizing adverse effects on surrounding healthy tissues. Due to this advantage, brachytherapy is commonly employed in the management of several malignancies, including cervical cancer, prostate cancer, breast cancer, esophageal cancer, and skin cancer [1-5]. Since brachytherapy delivers a high radiation dose over a short period of time, precise positioning of the radioactive source and accurate control of the dwell time are critical. Inaccuracies in either parameter may increase the risk of tumor recurrence and cause severe side effects in normal tissues. Therefore, an accurate and systematic assessment process to verify the position and dwell time of the source is essential for both patient safety and treatment effectiveness. In brachytherapy, dosimetric quality assurance (QA) is performed by verifying the source strength using a well-type chamber, measuring the ionization current, and subsequently calculating and documenting the dose rate [6-8]. For mechanical verification, positional QA is typically performed by confirming the source position using a check ruler or radiochromic film [9-13]. Dwell time verification within positional QA is conducted either mechanically, using a check-cable test with the device’s dummy source, or with independent instruments specifically designed for this purpose. Before patient treatment, the overall applicator and source arrangement is assessed using C-arm fluoroscopy before delivery.
However, the aforementioned mechanical verification procedures can be prone to setup and analysis errors, and the measurement and evaluation process may be time-consuming, diminishing the efficiency of the radiotherapy workflow. Therefore, in this study, a scintillator-based mechanical QA system was developed to enable efficient and accurate positional and temporal verification in brachytherapy. This system was implemented in a clinical setting, and independent QA was performed and validated over an extended period.
Materials and Methods
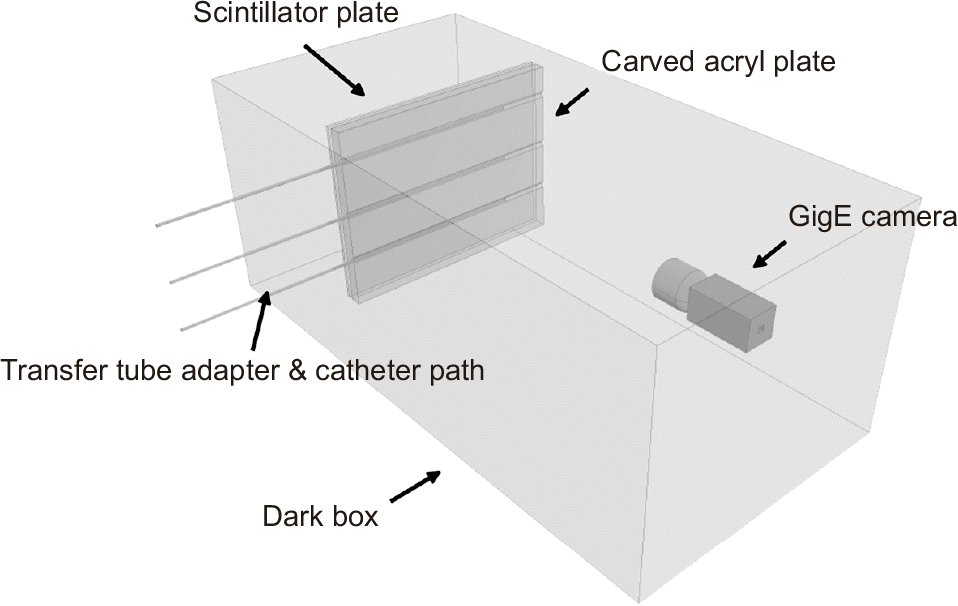
To develop the scintillator-based brachytherapy QA system, the hardware was configured as illustrated in Fig. 1. A GigE (Gigabit Ethernet) camera (Omron) and a scintillator plate were placed inside a dark box, and a transparent acrylic plate, carved to allow catheter passage, was positioned in front of the scintillator plate. An external adapter was mounted to connect the transfer tubes, and a dedicated pathway was created to enable the catheter to pass through the system. An adapter was mounted on the exterior of the dark box near the GigE camera to enable the connection to a standard local area network (LAN) cable. This design allows remote software control from outside the treatment room via the LAN cable embedded within the room infrastructure. The camera used had a resolution of 2,100×1,200 pixels and operated at a frame rate of 15 frames per second. Images were acquired within a defined region of interest, encompassing the scintillator area (15×10 cm2) at a resolution of 1,800×1,000 pixels.
To accurately acquire scintillator images within the dark box, the camera was first calibrated using Zhang’s method [14], which estimates intrinsic and extrinsic parameters as well as lens distortion coefficients using a chessboard pattern. A custom aluminum checkerboard measuring 15×10 cm with 5 mm square widths was used for this calibration. Subsequently, to calculate the actual displacement of scintillator light generated by radiation, the pixel size of the checkerboard squares detected by the camera was mapped to their real dimensions, enabling determination of the physical distance represented by each camera pixel. Additionally, the catheter tip dwell position, defined as the maximum reach of the catheter through the transfer tube, was marked on the camera image. This enabled direct mapping to the absolute catheter position specified by the brachytherapy machine. Based on the above elements, the developed system was employed in a clinical environment for daily positional and temporal QA over approximately one year.
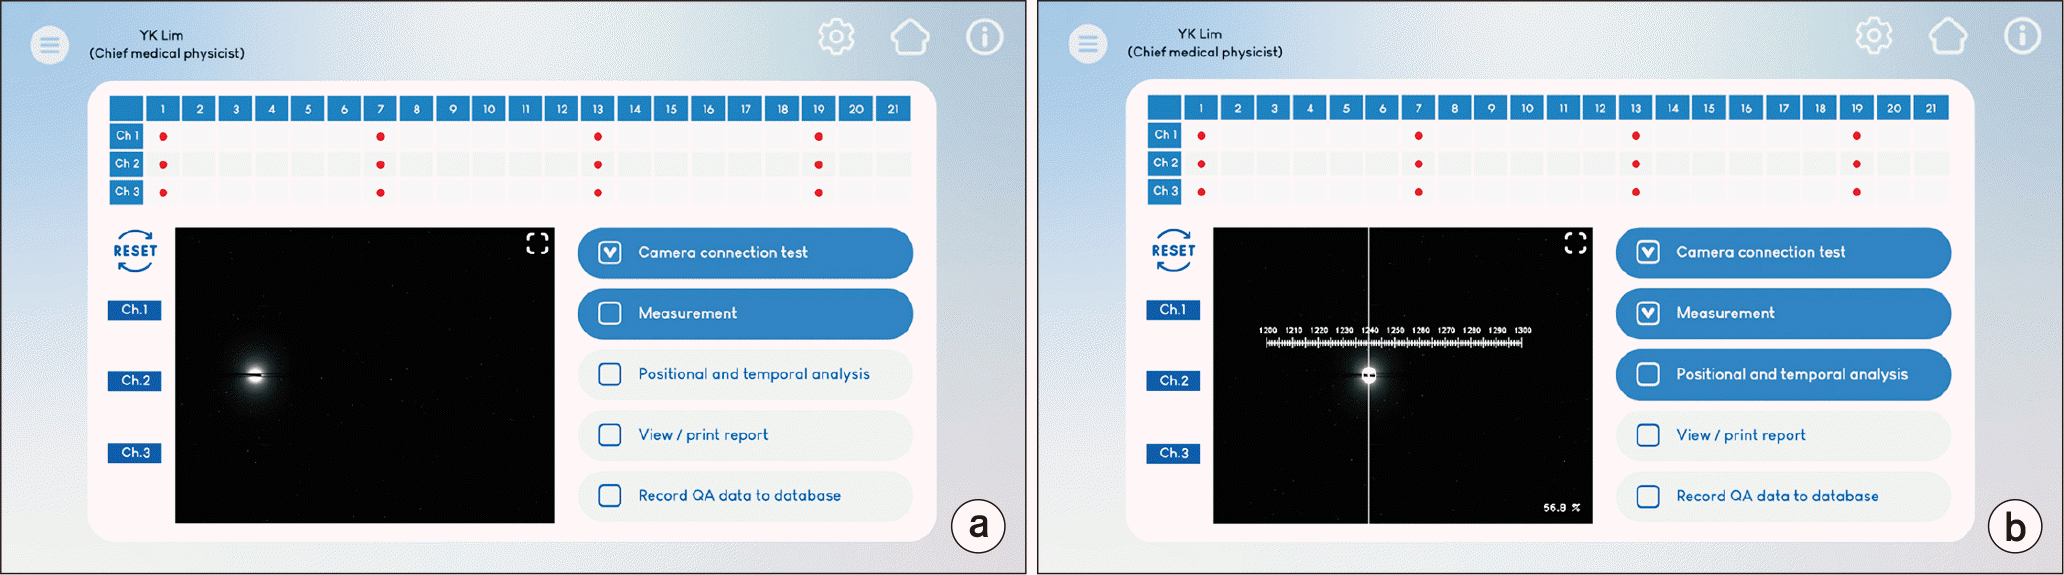
First, catheter positions were planned for three channels using the brachytherapy machine (Flexitron; Elekta). For each channel, dwell times of 5 seconds were assigned at four positions: 1,300, 1,270, 1,240, and 1,210 mm. Camera images of scintillator emissions generated by the radiation source were then acquired, as shown in Fig. 2. Scintillator noise was removed in advance through image processing techniques. The system calculated the absolute catheter location by identifying the centroid of scintillator emission at each specified position, which was then compared to the planned coordinates. Dwell time was determined from the camera frame count and frame rate, allowing direct comparison with the planned dwell time.
Results
Daily verification data for position and dwell time were systematically recorded in a structured database using structured query language, and the data collected over one year were analyzed.
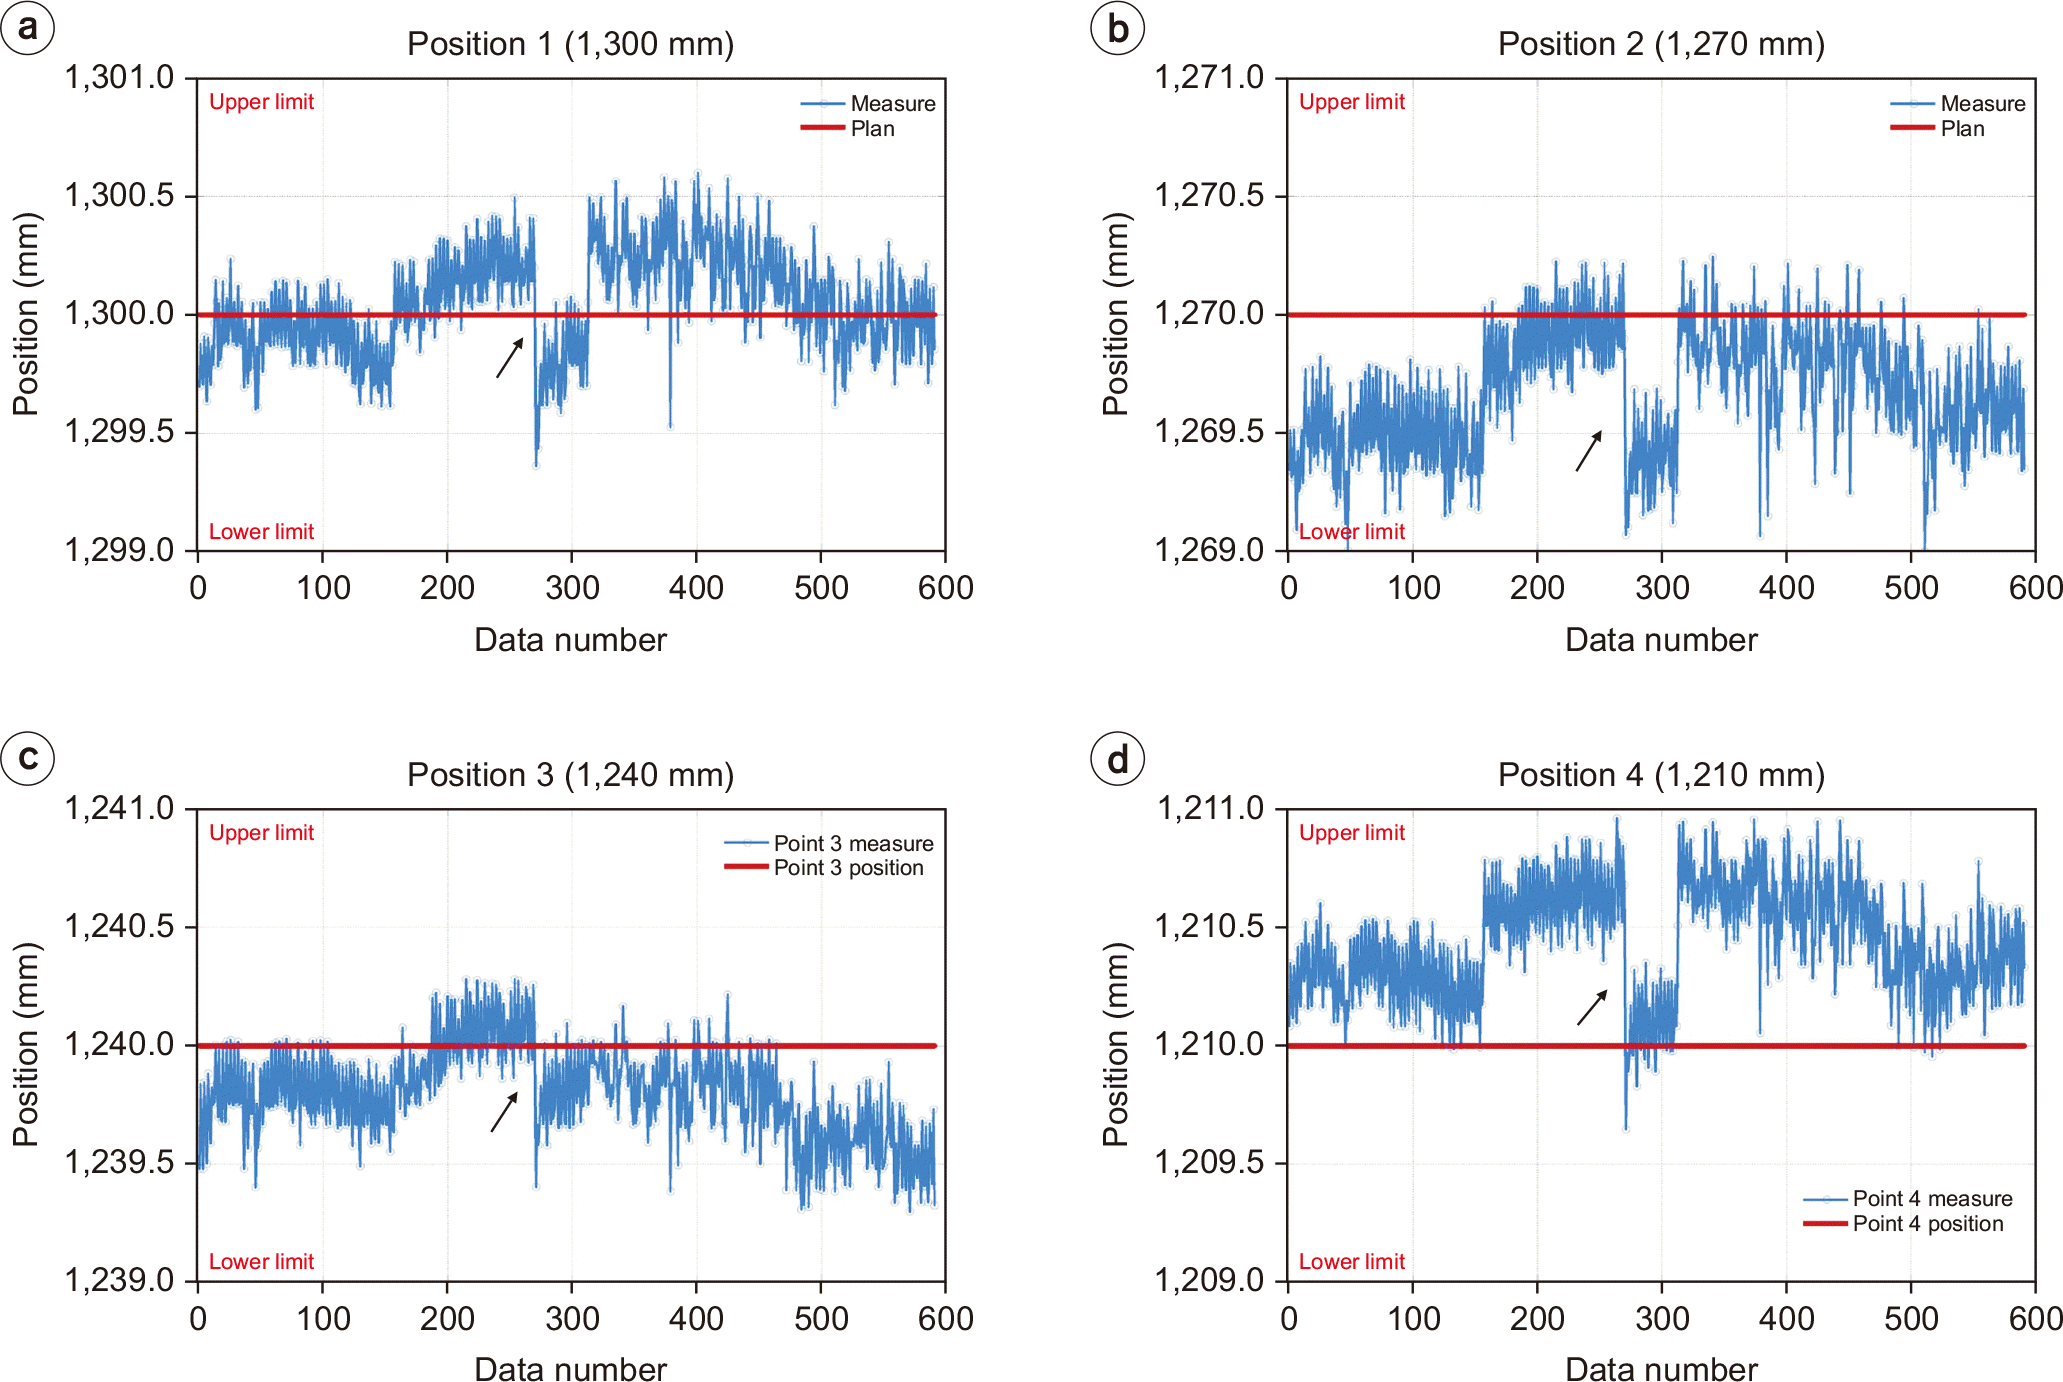
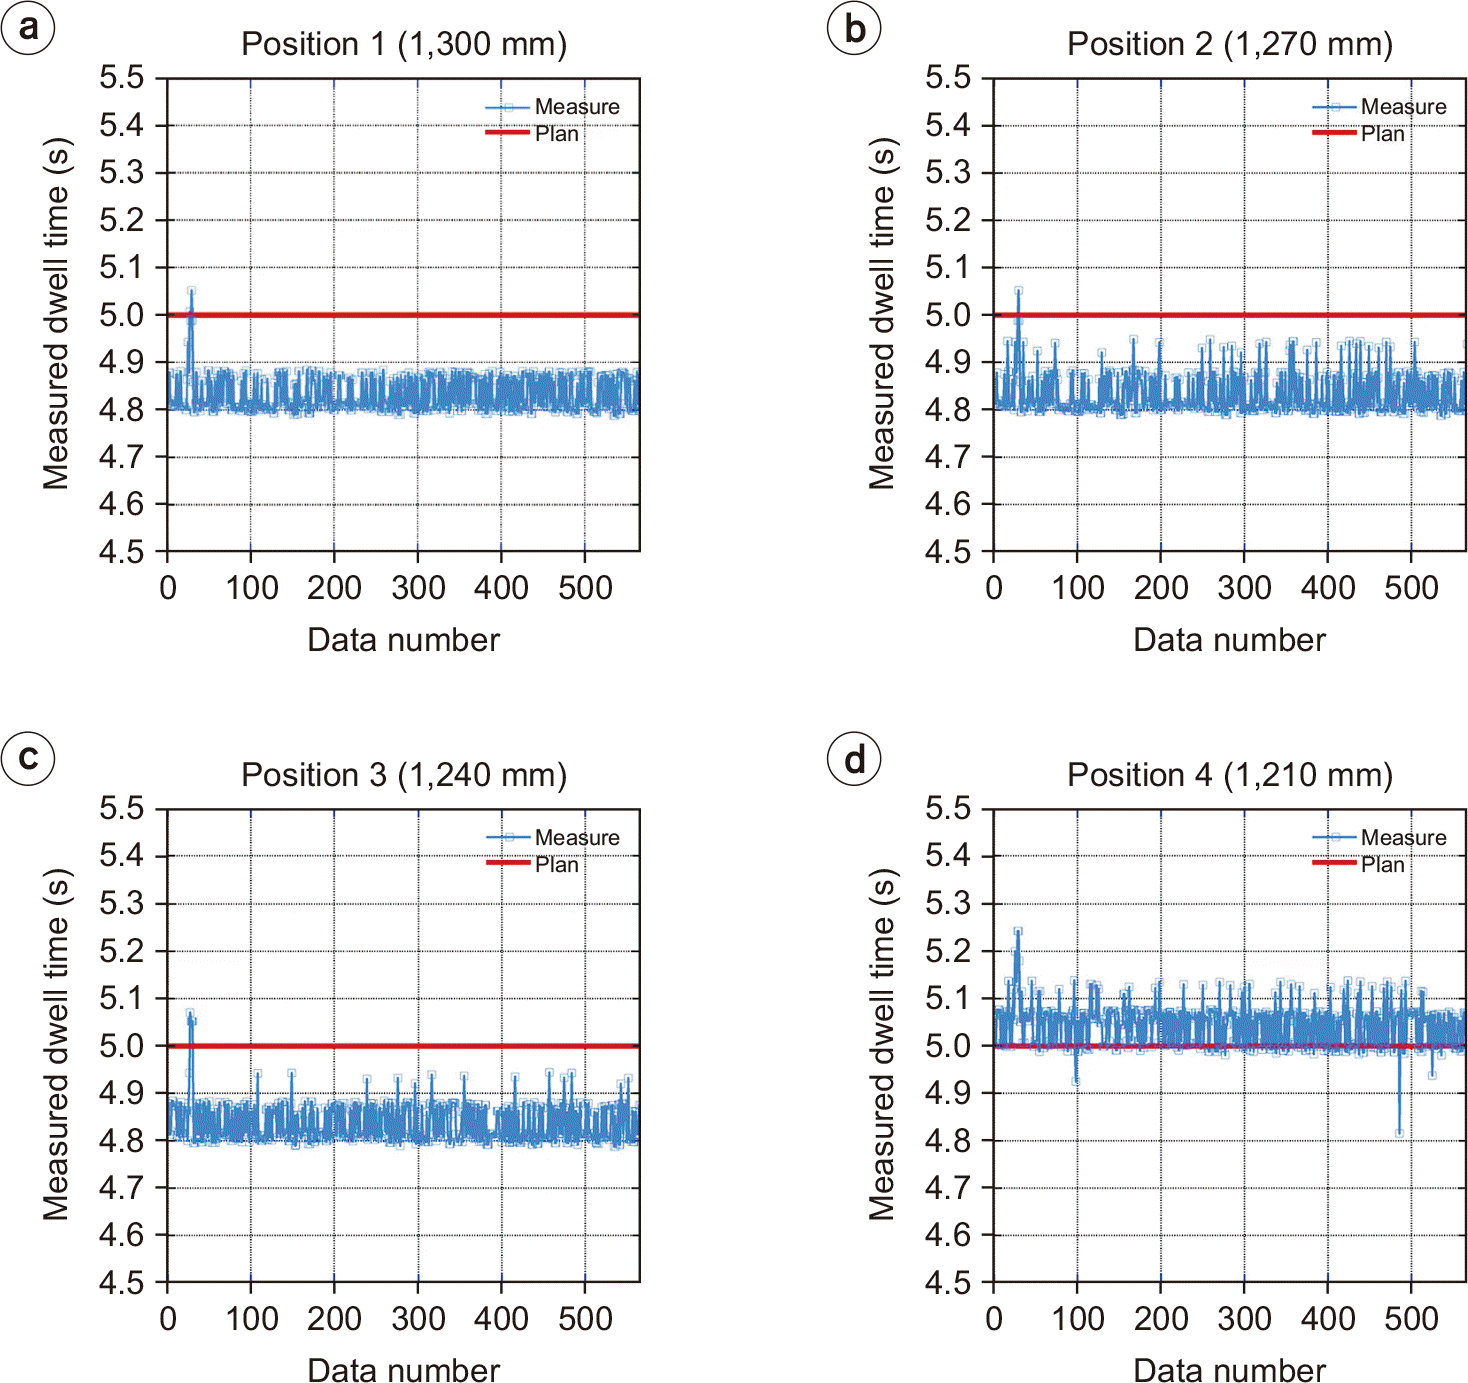
As a result of continuous independent daily verification performed using the developed system as described above, positional QA showed an accuracy within ±1 mm compared to the planned positions, as demonstrated in Fig. 3. The mean and standard deviation of the differences between the measurements and the planned positions were both within the submillimeter range, as shown in Table 1. The accuracy of the source position was confirmed through monthly film-based QA and through cross-validation with the brachytherapy machine’s camera-based alignment system during source exchange. Continuous temporal QA measurements indicated that most dwell times were consistently 0.1–0.2 seconds shorter than those specified in the treatment plan. For position 4, as depicted in Fig. 4d, the measured dwell time was longer than at the other positions. This positional discrepancy is likely because position 4 represents the initial location where the catheter deploys the radiation source, a trend that remained consistent throughout the measurement period. This phenomenon, known as the “transit time effect,” occurs when the dwell time observed at the first position is slightly longer than at subsequent positions due to source transit, as has been previously reported [15].
When four dwell positions (1,300, 1,270, 1,240, and 1,210 mm) with a dwell time of 5 seconds each were assigned to three channels, a full cycle of positional and temporal QA was performed. This process, including analysis and automatic saving to the database, required approximately 1 minute and 30 seconds to 2 minutes.
Discussion
The independent QA system based on a scintillator and GigE camera developed in this study demonstrated sustained accuracy and reliability over extended measurements in the clinical environment. The scintillator- and GigE camera-based independent QA system developed in this study demonstrated sustained accuracy and reliability during extended measurements in a clinical setting. Moreover, compared with conventional daily verification techniques, such as radiochromic film and check rulers, the system offered greater operational efficiency in both setup and analysis. These findings further underscore the system’s practicality and value for routine clinical application in high dose rate (HDR) brachytherapy.
An accurate and stable calibration of the camera is essential for any QA system based on a scintillator and image capture, particularly for high-precision tasks like HDR brachytherapy. Using a lens with minimal distortion and applying detailed lens correction procedures is highly recommended. The camera calibration process, typically performed under bright lighting, can differ significantly from image acquisition in the dark box. Therefore, maintaining a consistent aperture setting that prevents brightness-related artifacts and signal saturation during both calibration and measurement is critical for obtaining reliable results.
In this study, the selected GigE camera used a LAN connection rather than the more commonly employed USB interface. Although USB connections provide good compatibility and high data rates, their effective cable length is limited by signal attenuation, delays, and error rates—limitations that become pronounced with longer cable runs or higher versions, such as USB 3.0 [16]. In radiotherapy clinical settings, where the treatment room and control room are physically separated, these cable length constraints make USB less feasible. Conversely, LAN-based GigE cameras are better suited for the long-distance, high-data-rate transmission required in such environments. Furthermore, their support for Power over Ethernet enables simultaneous data transmission and power supply through a single cable. This simplifies the installation process and reduces maintenance costs, which is well-suited for clinical environments. However, GigE cameras may experience data loss if the host computer’s CPU is overloaded or if the data storage speed is not sufficiently fast [17]. To prevent this, all measurements in this study were performed using a dedicated laptop running no background processes other than the data acquisition software, ensuring data integrity throughout the experiments.
In a camera-based system, geometric calibration is essential to correct for lens aberrations, particularly radial and tangential distortions. Without such correction, measurement errors in the source position increase significantly toward the periphery of the scintillator image, thereby degrading the reliability of position verification. In this study, we employed Zhang’s camera calibration method [14], a widely adopted technique available through the OpenCV library, known for its ease of use and accessibility. After calibration, the absolute displacement of the source captured by the camera was determined by mapping pixel coordinates to physical dimensions using the known size of a checkerboard pattern. Long-term verification of the system using this approach confirmed its stability and robustness.
The scintillator-based QA system developed in this study was utilized exclusively for mechanical QA. This approach was adopted because the pixel values in the scintillator images ranged from 0 to 255, resulting in a relatively small image size that enables rapid data acquisition and processing. However, this limits the system’s utility for cross-verifying the dose rate of the radiation source, as the intensity resolution is insufficient for accurate dosimetric evaluation. If a procedure utilizes images with an extended pixel value range (e.g., 0–65,535) and analyzes them over time, the system could be adapted as an independent method for cross-verifying the source dose rate.
In this study, temporal QA performed using the developed system revealed discrepancies between the planned dwell times and those measured by the system. Such differences may arise from multiple factors. First, the treatment planning system assumes that the source reaches each dwell position instantaneously, whereas the afterloader requires a finite mechanical transit time to advance and retract the source along the drive wire. Consequently, the measured dwell times inherently include mechanical delays and the device’s intrinsic timing tolerances. In addition, the camera used in this study acquires one frame every 0.06 seconds; hence, the discrete sampling imposed by its frame rate may introduce a small uncertainty in the reconstructed timing of the source motion, particularly during periods of rapid source movement.
Conclusions
This study developed and validated an independent QA system using a scintillator and GigE camera for daily mechanical verification in HDR brachytherapy. Extended clinical use demonstrated high accuracy and reliability, supporting the suitability of this approach for routine clinical QA. Future work will focus on adapting and validating the system for intensity modulated brachytherapy to meet the demands of more advanced irradiation protocols.
 XML Download