



 PDF
 Citation
 Print


Introduction
Accurate patient-specific quality assurance (PSQA) is a critical component of modern radiation therapy. With the increasing complexity of treatment techniques, such as intensity-modulated radiation therapy (IMRT), the need for reliable quality assurance (QA) has grown significantly. Effective QA is essential for ensuring patient safety and maximizing treatment efficacy [1-3].
Electronic portal imaging devices (EPIDs), originally developed for patient positioning, have evolved into promising tools for dosimetric verification [4]. Electronic portal images (EPIs) are converted into dose or fluence through vendor algorithms and then used to verify treatment plans. Compared to other QA devices, such as 2D diode or ion chamber arrays, EPIDs provide higher-resolution measurements and require no additional phantom setup, making them well-suited for efficient clinical workflows [4-6].
EPI-based PSQA software is validated through a commissioning process to ensure performance and reliability. During this process, tests should be conducted across multiple treatment sites in accordance with the institution’s clinical indications. EPIDs have limitations in measurable field size; hence, guidelines must be established through verification using representative cases, particularly for cancers that require large treatment fields.
In this study, we aimed to clinically validate the EPIbeam (DoSIsoft, ThinkQA version 1.0.6.35) as a patient-specific pretreatment QA system. The study was conducted in two phases: (1) verification using large square fields to assess system performance under controlled conditions, and (2) validation with various patient cases to examine its applicability across multiple treatment sites before clinical implementation.
Materials and Methods
1. Quality assurance system configuration
In EPIbeam, QA is performed by comparing two planar doses: a reference dose plane calculated from the IMRT plan (predicted dose) and an EPI acquired during plan delivery, which is then converted into a dose plane under reference conditions (acquired dose). IMRT plans were delivered using a Harmony Pro linear accelerator (Elekta AB). Portal images were obtained using Elekta iViewGT, and EPIbeam was integrated with the iViewGT database to retrieve and utilize these images. After an EPI is imported into EPIbeam, it is converted to a dose plane under reference conditions using a kernel-based algorithm. This algorithm incorporates pixel-value–to–absorbed-dose calibration and models for factors, such as ghosting/lag, gantry sag, and field-size dependence for dose conversion. The acquired dose is evaluated against the predicted dose using gamma analysis [7]. EPIbeam then reports the gamma passing rate (GPR) and displays the corresponding two-dimensional dose distribution. Detailed commissioning procedures for EPIbeam [5,6,8] have been described in other publications and are beyond the scope of this study.
2. Verification with a square field
During commissioning, gamma analysis was performed for a 10×10 cm2 field, and the EPI-to-dose conversion algorithm accounted for field-size–dependent output factors. Due to the physical limitations of the Elekta iView EPID, the maximum valid field size in EPIbeam is 24×24 cm2. However, some clinical cases involve field sizes at Source to Axis Distance=100 cm that exceed 24×24 cm2, or use an isocenter positioned outside the tumor, so that the tumor is not fully contained within 12 cm of the field center. In these situations, the QA result includes a dose derived from an out-of-range conversion algorithm. As a result, it is not clinically applicable. In this study, we determined the maximum field size suitable for clinical use with EPIbeam by testing large square fields. Fields were expanded from 22×22 cm2 to 25×25 cm2, and both 6- and 10-MV beams were delivered. Plans were configured to deliver 200 cGy to the isocenter. Gamma analysis was then performed for all fields using 3%/3 mm, 3%/2 mm, 2%/2 mm, and 2%/1 mm criteria, with global normalization and a 10% dose threshold applied. The corresponding two-dimensional dose distributions were subsequently reviewed.
3. Verification for patient treatment plans
1) Comparison of patient-specific quality assurance results: EPIbeam vs. MapCHECK3
Based on the clinical indications treated at our institution using an Elekta LINAC, we selected 54 IMRT plans across treatment sites. The IMRT cohort included both static IMRT and volumetric modulated arc therapy (VMAT), with the number of plans for each treatment site presented in Table 1.
PSQA was performed using EPIbeam for IMRT plans based on composite dose distributions. VMAT plans were evaluated with a 2%/2 mm gamma criterion, while static IMRT plans were assisted using a 3%/2 mm criterion. Using the same criteria, PSQA was also performed for VMAT plans with MapCHECK3 (Sun Nuclear Corporation), and the results were compared with those from EPIbeam. The Wilcoxon signed-rank test was used to compare EPIbeam and MapCHECK3 for the VMAT plans. This test was not conducted for the 6 MV static IMRT plans due to the small sample size (n=8). In addition, EPIbeam was further evaluated under various gamma criteria combinations—3%/3 mm, 3%/2 mm, 2%/2 mm, and 2%/1 mm—with global normalization and a 10% dose threshold. All analyses were conducted on composite dose distributions.
2) Extended field size with patient treatment plans
EPIbeam PSQA was performed for five treatment sites involving large treatment fields: T-spine, prostate, stomach, pelvic bone, and whole pelvis. The original patient plans were delivered using a single-field VMAT technique. For each original plan, the target margin was incrementally expanded until the field size at the isocenter approached 24 cm, generating three additional plans for each case. Each case was adjusted along a single field direction, considering whether such modifications could realistically occur in clinical practice. For example, the T-spine treatment field was not extended laterally. A total of 20 large–field-size patient plans underwent PSQA. Each plan was evaluated using gamma criteria of 3%/3 mm, 3%/2 mm, 2%/2 mm, and 2%/1 mm, with global normalization and a 10% dose threshold applied.
Results
1. Verification for square fields
Tables 2 and 3 present QA results for 6- and 10-MV beams using square fields ranging from 22×22 cm2 to 25×25 cm2. For 6 MV, all plans achieved a GPR above 90% with the 3%/3 mm criterion, and all plans, except the 25×25 cm² field, exceeded 90% with the 3%/2 mm criterion. Under the stricter 2%/2 mm criterion, GPRs declined noticeably for field sizes larger than 24×24 cm2. With the 2%/1 mm criterion, GPR fell below 90% for all field sizes except 22×22 cm2. Notably, once the field size exceeded 24×24 cm2, GPR declined more sharply, indicating that the image-to-dose conversion algorithm is reliable up to 24×24 cm². A similar sharp decline was observed for 10 MV beyond 24×24 cm2, although overall GPRs remained higher than those for 6 MV. Fig. 1 shows the dose distribution and GPR map for a 6 MV beam with a 23×23 cm2 field. At the four corners of the square field, the predicted dose was underestimated compared to the acquired dose, likely reflecting a limitation in the dose-conversion modeling process.
2. Patient plan verification using EPIbeam and MapCHECK3
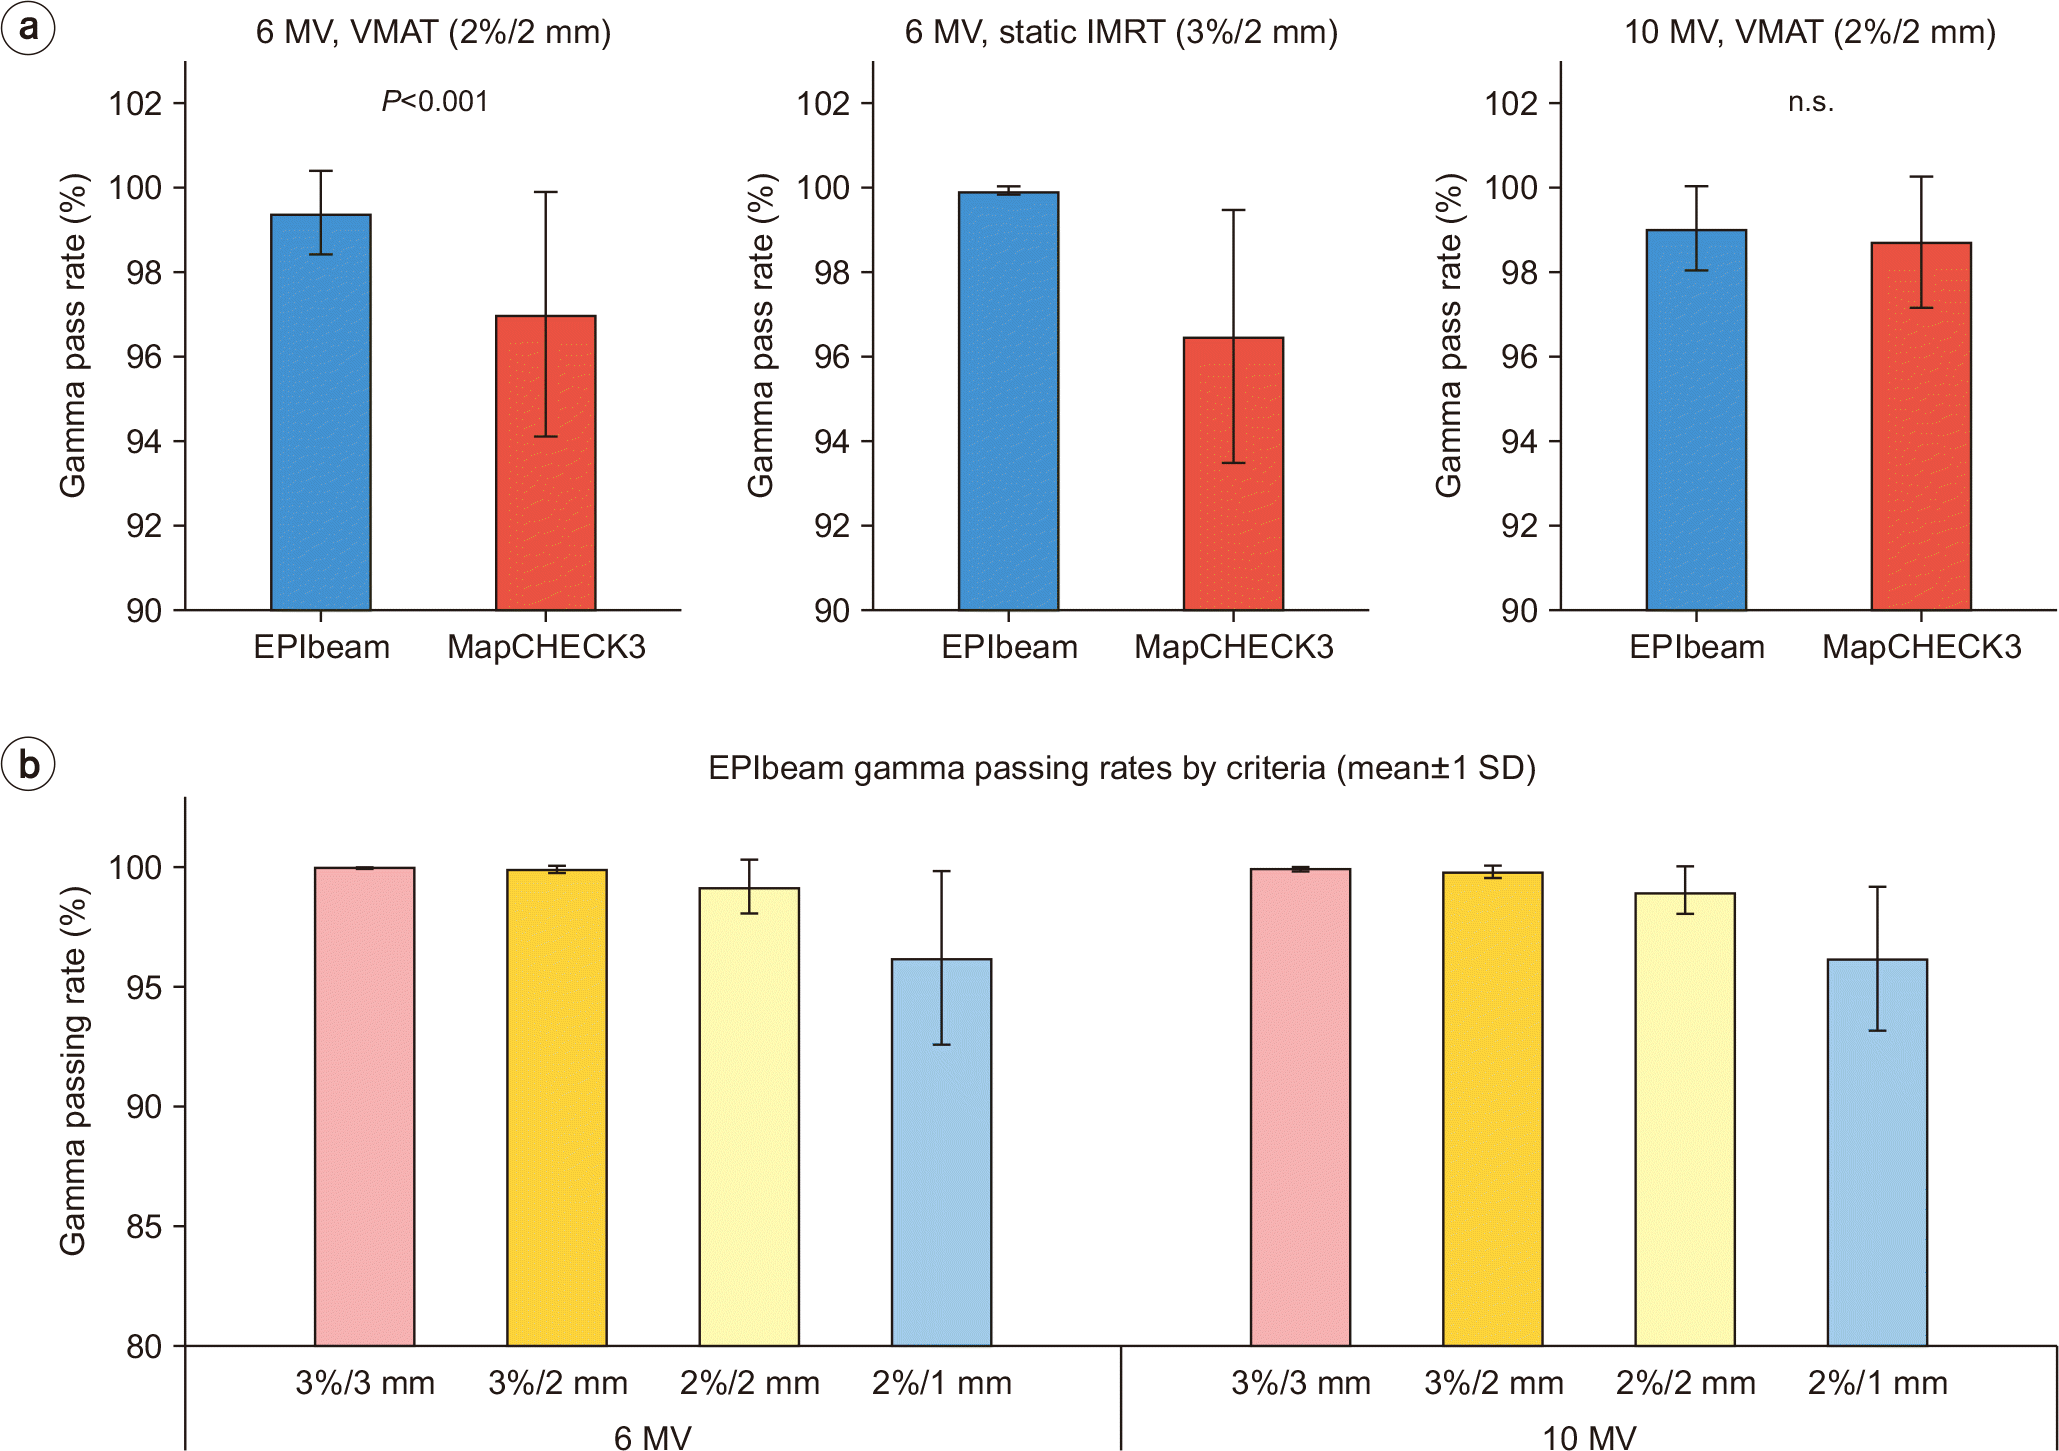
Fig. 2a shows the PSQA results of EPIbeam and MapCHECK3 for patient treatments using 6 MV–VMAT, 6 MV–static IMRT, and 10 MV–VMAT techniques. For the 6 MV–VMAT plans, the mean GPR was 99.40%±1.00% for EPIbeam and 96.98%±2.92% for MapCHECK3, representing a statistically significant difference (P<0.001). For the 6 MV–static IMRT plans, EPIbeam demonstrated a higher mean GPR (99.93%±0.10%) compared with MapCHECK3 (96.48%±2.99%), corresponding to an average difference of approximately 3.5%±3.0%. In contrast, for the 10 MV–VMAT plans, the mean GPRs of EPIbeam (98.19%±4.28%) and MapCHECK3 (98.67%±1.53%) showed no significant difference.
Subsequently, Fig. 2b shows the variation in GPRs for 6 MV and 10 MV beams using EPIbeam under different gamma evaluation criteria. For 6 MV, the mean GPRs were 99.99%±0.03% (3%/3 mm), 99.92%±0.17% (3%/2 mm), 99.21%±1.12% (2%/2 mm), and 96.22%±3.64% (2%/1 mm). For 10 MV, the corresponding mean values were 99.96%±0.07%, 99.83%±0.25%, 99.05%±0.98%, and 96.19%±3.03%, respectively. Based on the gamma criteria employed at our institution, all plans met the clinical tolerance. Even under the strict 2%/1 mm criterion, the mean GPR remained above 90%, with only three failures for 6 MV and one for 10 MV. These results suggest that EPIbeam demonstrates robust performance. However, its use for highly precise techniques, such as stereotactic ablative radiotherapy, should be approached with caution and supported by additional verification. The relatively large standard deviation observed for the 10 MV beam in EPIbeam can be attributed to the same T-spine case described above.
3. Verification with extended treatment field size
Table 4 presents the PSQA results for plans generated from representative treatment sites with clinically large field sizes, where target margins were expanded to approach the maximum field size measurable with EPIbeam. GPRs were evaluated using various gamma criteria, and all plans achieved GPRs above 90% across all criteria.
Even for large field sizes, no failure was observed at the field edges, as illustrated in Fig. 1. These results indicate that partial gamma failures may occur at the corners of square fields within the valid modeling range (Section 3.1), but their impact on PSQA outcomes for actual clinical cases is negligible.
Discussion
In this study, the performance of the EPIbeam pretreatment QA system was evaluated through gamma analysis, ranging from simple square fields to patient-specific plans of varying field sizes. Due to the physical limitations of the Elekta iView EPID, the maximum valid field size in EPIbeam for 24×24 cm2. Therefore, validation was performed near this upper limit to confirm the system’s accuracy at its maximum applicable range.
As shown in Fig. 1 and discussed in Section 3.1, discrepancies between the predicted and acquired doses were observed at the corners of the square fields, even for field sizes smaller than the maximum. These discrepancies occurred despite the commissioning process, which included validation using a 10×10 cm2 field and output factor corrections across different field sizes. Considering that the GPR distribution exhibited circular symmetry around the central axis [9,10], this behavior may be attributed to the modeling of the scatter dose kernel as a function of distance from the central axis, which can lead to slight inaccuracies outside the modeled region. This interpretation aligns with the scatter dose kernel modeling described in the manufacturer’s proprietary technical documentation. The observed reduction in gamma values at the field edges necessitated further evaluation during the patient-specific verification. Accordingly, extended field sizes were additionally assessed for the patient cases in Section 2.3.
Using clinical patient plans delivered on Elekta linear accelerators, PSQA was performed with both EPIbeam and MapCHECK3 according to the institutional gamma criteria, and the results were compared. As shown in Fig. 2, EPIbeam achieved comparable or higher GPR values than MapCHECK3, and all cases exceeded a 90% passing rate. The two QA systems differ in both detector configuration and dose accumulation: EPIbeam uses a perpendicular composite approach, whereas MapCHECK 3 acquires measurements using a true composite (TC) approach. In the TC setup, portions of several VMAT beams may not fully traverse the detector plane, especially when only a limited range of leaf pairs irradiates the panel. As a result, some beam segments are not sampled, which can contribute to differences in gamma evaluations between the two systems.
To further assess the impact of large field sizes, five treatment sites with relatively wide fields were selected, and the target margins were systematically expanded so that the planned field size approached 24×24 cm2. Despite the discrepancies observed in square fields as early as 23×23 cm2 (Fig. 1), all adjusted clinical plans achieved GPRs above 90%, even under the strictest acceptance criterion (2%/1 mm). This indicates that minor deviations may occur in large square fields; however, their impact on the PSQA results for actual clinical cases remained minimal. Overall, EPIbeam can be considered a reliable PSQA tool for treatment plans with field sizes up to 24 cm per side at the isocenter.
One limitation of this study is that intentional multi leaf collimator (MLC) errors were not introduced to assess the sensitivity of EPIbeam to delivery inaccuracies. However, prior investigations have assessed EPIbeam under controlled MLC error conditions and reported detection performance comparable to diode- and ion-chamber–based IMRT QA systems [11,12]. The EPID utilized in EPIbeam provides submillimeter spatial sampling, offering higher resolution than the coarser detector spacing found in diode arrays, such as MapCHECK3. This high spatial resolution enables more accurate gamma evaluation and is well suited for QA of treatment plans with steep dose gradients [1], such as those encountered in stereotactic radiosurgery and stereotactic body radiation therapy. However, rigorous validation remains essential for these high-precision techniques. When films are scanned at commonly used settings [13,14], their resolution becomes comparable to that of EPID-based QA systems [15], and previous studies have reported comparable IMRT QA results between the two modalities [16]. Given these considerations, the absence of intentional MLC error testing in this study is unlikely to affect the overall conclusions regarding the clinical applicability of EPIbeam. In addition, patient plans using flattening filter–free beams were not evaluated because these are not yet used in our institution’s clinical practice. Nevertheless, because this study focused on assessing the clinical applicability of EPIbeam, these limitations do not compromise the validity of the findings.
Conclusions
Based on PSQA results across treatment sites, EPIbeam demonstrated GPRs comparable to or higher than those of MapCHECK3, confirming its clinical validity and performance reliability. Although slight dose underestimation was observed at the corners of square fields—even within EPIbeam’s maximum valid field size—this effect was negligible during treatment plan verification. Overall, these results support EPIbeam as a clinically validated and reliable patient-specific pretreatment QA system.

 XML Download