



 PDF
 Citation
 Print


Introduction
Radiation therapy has evolved from basic conformal static fields to sophisticated techniques like intensity-modulated radiation therapy (IMRT) and volumetric-modulated arc therapy (VMAT), in which dynamically moving multi-leaf collimators (MLCs) directly influence dose delivery [1,2]. This evolution underscores the need for more accurate MLC motion modeling and evaluation of its dosimetric impact [3,4].
The Eclipse dose calculation algorithm, widely used in clinical practice, relies on fluence maps to represent beam intensity. MLC modeling applied to beam shaping directly influences the accuracy of fluence calculation [5]. Until Eclipse version 17 (v17), the MLC was simplified as a thin, uniform attenuating layer that either transmitted or blocked the beam depending on a user-defined transmission factor. To account for discrepancies between the dosimetric and geometric field widths caused by radiation transmission through the rounded leaf ends, users were also required to measure and define the dosimetric leaf gap (DLG) [6,7]. With the upgrade to AcurosXB v18, a new approach called enhanced leaf modeling (ELM) was introduced, extending from the simplified uniform-layer assumption to incorporate the actual geometric design of MLC leaves. The ELM has been implemented in commonly used Varian Medical Systems MLCs, including the Millennium 120, HD-MLC, and dual-layer MLC. Previous studies have reported that this geometry-based attenuation model improves the accuracy of dose delivery for both static and dynamic MLC fields [5,8].
Although the DLG is generally determined by measurement, in clinical practice, it often requires site-specific optimization due to the characteristics of the detectors used in patient-specific quality assurance (PSQA). This optimization is typically performed by testing multiple DLG values across a set of plans and selecting the value yielding the highest pass rate [9,10]. Consequently, the clinically applied DLG may differ from the raw measurement. Therefore, with the upgrade to Eclipse v18, we conducted a preliminary comparative evaluation of the dose calculation algorithm between the newly introduced ELM and MLC modeling from v16 to verify the previously used beam model. Since the two models are implemented with entirely different functions, the measured data for ELM of v18 were scaled to match the same reference dose for v16 in the test plan provided by the manufacturer, allowing a direct comparison.
The comparison was performed with the AcurosXB dose calculation algorithm, which is widely used in most treatment units and clinical cases at Seoul National University Hospital. Patient treatment plans delivered with VitalBeam (VB) and TrueBeam (TBX) linear accelerators (LINACs) were analyzed. The scaled DLG and transmission factor values were compared with those obtained from v16. Furthermore, the plan monitor units (MUs) were compared using the same treatment plans with the scaled parameters applied, and the gamma passing rates (GPRs) were evaluated with portal dosimetry to assess the clinical validity of the optimized parameters.
Materials and Methods
1. Enhanced leaf modeling measurement
ELM parameter measurements were performed using the vendor-provided test plan (MLCparam_ELMconfig, Varian Medical Systems). The measurements were taken on multiple LINACs available at Seoul National University Hospital, including two VB units and one TBX unit, using a 30×30 cm² solid water phantom at a source-to-surface distance of 90 cm. The detailed configuration of the test plan is summarized in Table 1. Each field was delivered with 500 MU, and the measured values were scaled by a factor of 0.2 to correspond to 100 MU for beam configuration use. The jaws were fixed at 10×10 cm² under all conditions.
The center of the phantom was aligned with the isocenter, and an ionization chamber was inserted along the longitudinal axis. Depending on the setup, either a medium-sized chamber (0.125 or 0.3 cc) or a Farmer-type chamber (0.6 cc) was recommended. In this study, a farmer-type ionization chamber (TN30013, PTW) was used to take the VB measurements, whereas a 0.125 cc ionization chamber (TN31010, PTW) was used to obtain the TBX measurements. All measurements were performed at a depth of 10 cm, which served as the designated reference point for dose calculations in the treatment planning system.
2. Measured charge scaling
With the upgrade to Eclipse v18, the vendor suggested that entering the measured charge (nC) at each reference point into Eclipse allows the system to calculate and apply the transmission factor and DLG value automatically. Conversely, in v16, users could manually calculate these two parameters (transmission factor and DLG) based on measured data and directly input or modify them. Additionally, unlike in v16, the leaf modeling algorithm in v18 has been modified, allowing negative DLG values to occur. Therefore, to enable a direct comparison between the two versions, we applied a scaling factor (SF) to the measured charge in v18 so the calculated dose at the reference point would be comparable between versions. The SF was calculated as follows:
where DV16 and DV18 represent the doses calculated at a reference depth of 10 cm at the isocenter of each plan in versions 16 and 18, respectively. The SF were calculated for all photon energies available on each LINAC.
3. Plan parameter comparison between AcurosXB v16 and v18
Treatment plans delivered in 2024 at Seoul National University Hospital were used. For the TBX, 45 cases (9 patients per energy setting) were included. For the VB, 40 cases were analyzed for VB1 and 30 cases for VB2. Target sites were selected with an emphasis on the anatomical regions most frequently treated with each machine. The MU values calculated with AcurosXB v16 were compared to those recalculated with v18 for dose computation only. Additionally, the GPR from the PSQA performed in v16 during treatment in 2024, and those recalculated in v18 under the same conditions, were analyzed. GPR was calculated using the portal dose image prediction (PDIP). A dose threshold of 10% was applied. The same evaluation criteria previously used in AcurosXB v16 were consistently adopted for each plan. The acceptance criteria were 1 mm/2% for stereotactic ablative body radiotherapy (SABR) treatments and 2 mm/3% for VMAT and IMRT, evaluated using the relative dose.
Results
1. Calculated scaling factor, dosimetric leaf gap, and transmission factor
Tables 2 and 3 summarize the calculated SF, DLG, and transmission factor for each LINAC and photon energy. The SF is defined as the ratio of the reference point dose calculated in AcurosXB v16 to that calculated in AcurosXB v18 for the same test plans. The transmission factor and DLG are the final values recalculated in the beam configuration after applying the SF. The transmission factors were generally comparable between the two versions, with differences of up to 0.0002. However, a noticeable discrepancy was observed in both magnitude and sign due to the different DLG implementations.
2. Monitor unit comparison
The patient treatment plans were initially optimized using photon optimization (PO) in AcurosXB v16. Then, the same plans were recalculated using the ELM-based dose calculation algorithm in AcurosXB v18. Because the total MU varied among plans, the MU difference between v16 and v18 was calculated for each treatment field and normalized to the MU from v16 for comparison. The statistical significance of the normalized MU differences (%) was analyzed using a paired t-test, with P <0.05 set as the significance threshold. Table 4 summarizes the mean MU difference, 95% confidence interval (CI), and paired t-test P-values for each beam energy setting. Although several beam energies, including VB 6X, VB 10X, and TBX FFF, showed statistically significant differences, the magnitude of the relative MU change remained within ±1% for all cases except TBX 10XF (−1.5%). Therefore, the MU differences between v16 and v18 were statistically detectable but clinically negligible, confirming the clinical equivalence of the two calculation models.
3. Gamma passing rate calculation
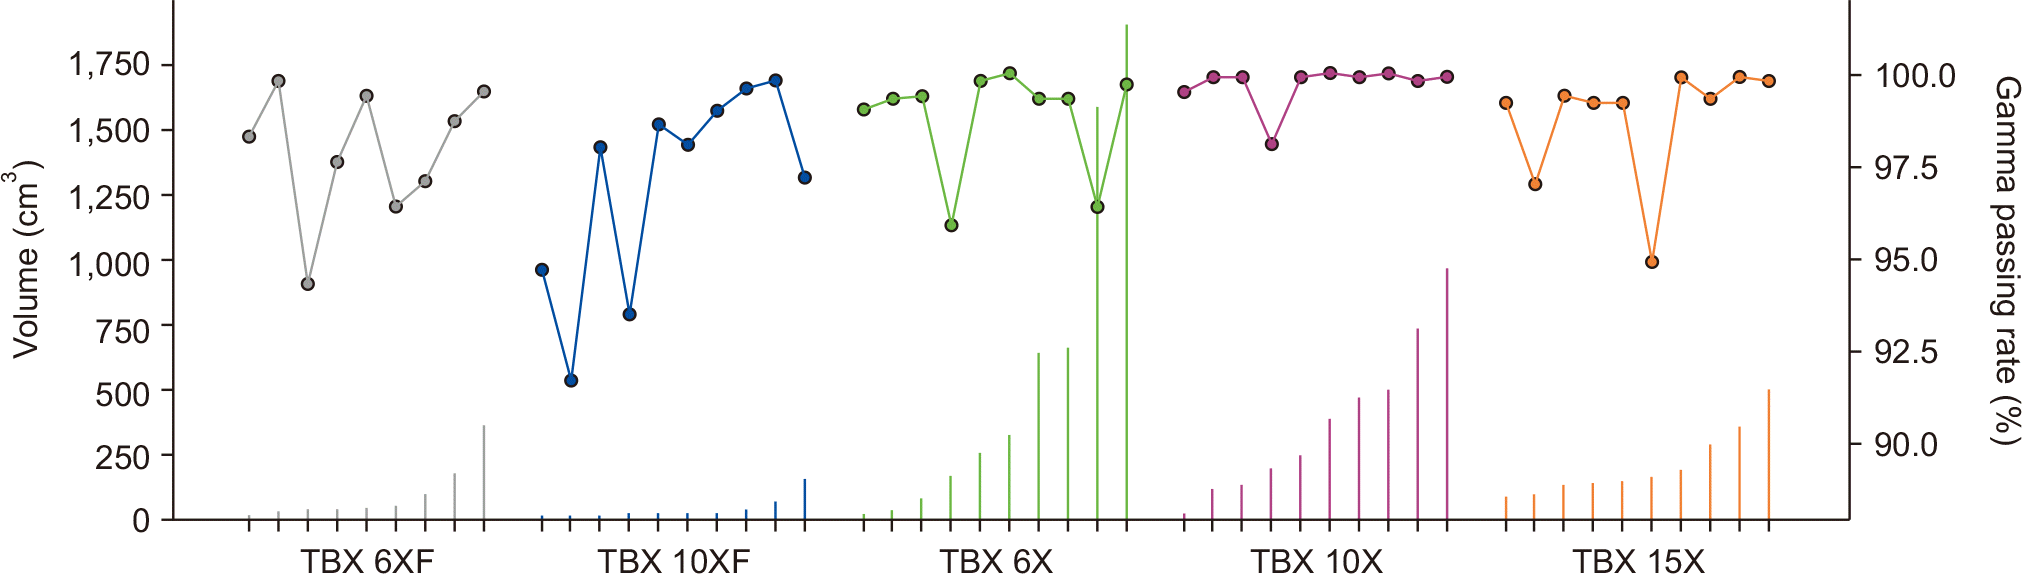
GPRs were calculated for each LINAC in AcurosXB v18. All plans achieved a GPR of at least 90% under their respective criteria and were clinically delivered. Fig. 1 presents the results for VB, and Fig. 2 presents the results for TBX, with the planning target volume (PTV) volumes of each plan also indicated. Various plans targeting different PTV volumes were compared, and no distinct correlation was observed between PTV volume and GPR. All v18 plans achieved a GPR exceeding 90%.
Discussion
With the upgrade to Eclipse v18, a new MLC modeling algorithm, ELM, was introduced. Unlike the previous version, the ELM algorithm incorporates rounded leaf tip geometry, enabling a more realistic representation of the MLC structure. This enhancement improves the accuracy of beam modeling, especially in reproducing fluence distributions near the leaf edges. In earlier versions, the geometric simplifications of the MLC model often required the use of empirically optimized transmission and DLG values that produced acceptable GPRs during PSQA, rather than accurately representing physical leaf behavior. In this study, previously optimized parameters were re-examined using the upgraded ELM model to assess their validity under the new modeling conditions.
Because the algorithms underlying MLC modeling in v16 and v18 fundamentally differ, both the applicable range and the sign convention of the DLG values changed. In particular, the v18 model allows negative DLG values (down to –0.1 cm), which is consistent with the range recommended by Varian Medical Systems. To enable a direct comparison, the measured data in the ELM model were scaled to deliver the same dose at the reference point in v16, ensuring that the evaluation reflected only modeling differences rather than variations in absolute dose. Measurement uncertainty was minimized by applying consistent setup and calibration procedures across all beam energies. With scaling, the transmission factors in v18 and v16 showed only minor deviations from the previous values. Conversely, the DLG values exhibited marked differences between versions. Even after scaling, many of the DLG values calculated in v18 had opposite signs compared to those used in v16, indicating a fundamental difference in the dose calculation methodology between the two versions.
When comparing the clinical plans, all beam conditions except TBX 10X FFF yielded comparable MU results between v16 and v18, with differences within ±1%. For TBX 10XF, a maximum deviation of –1.5% in the normalized MU differences was observed. This difference likely arose from changes in MLC leaf modeling, despite scaling applied to equalize the calculated dose at the reference point between the two algorithms. Because the ELM in v18 reproduces the curvature of the leaf ends more precisely, it provides a more realistic simulation; thus, minor discrepancies can occur due to leaf motion. Whereas this study primarily evaluated the effect of ELM based on MU comparisons, other studies have reported that ELM-based DLG calculations demonstrate good agreement with point-dose measurement data [5,11]. Specifically, improved dose-prediction accuracy has been observed at the tongue-and-groove interfaces and the distal leaf edges. These findings suggest that subtle variations in dose prediction near leaf ends may also be reflected in the MU calculations in this study. Although several beam energies, including VB 6X, VB 10X, and TBX FFF, showed statistically significant differences, the magnitude of the relative MU changes remained within ±1% for all cases except TBX 10XF (−1.5%). Therefore, the MU differences between v16 and v18 were statistically detectable but clinically negligible, confirming that the two calculation models were clinically equivalent.
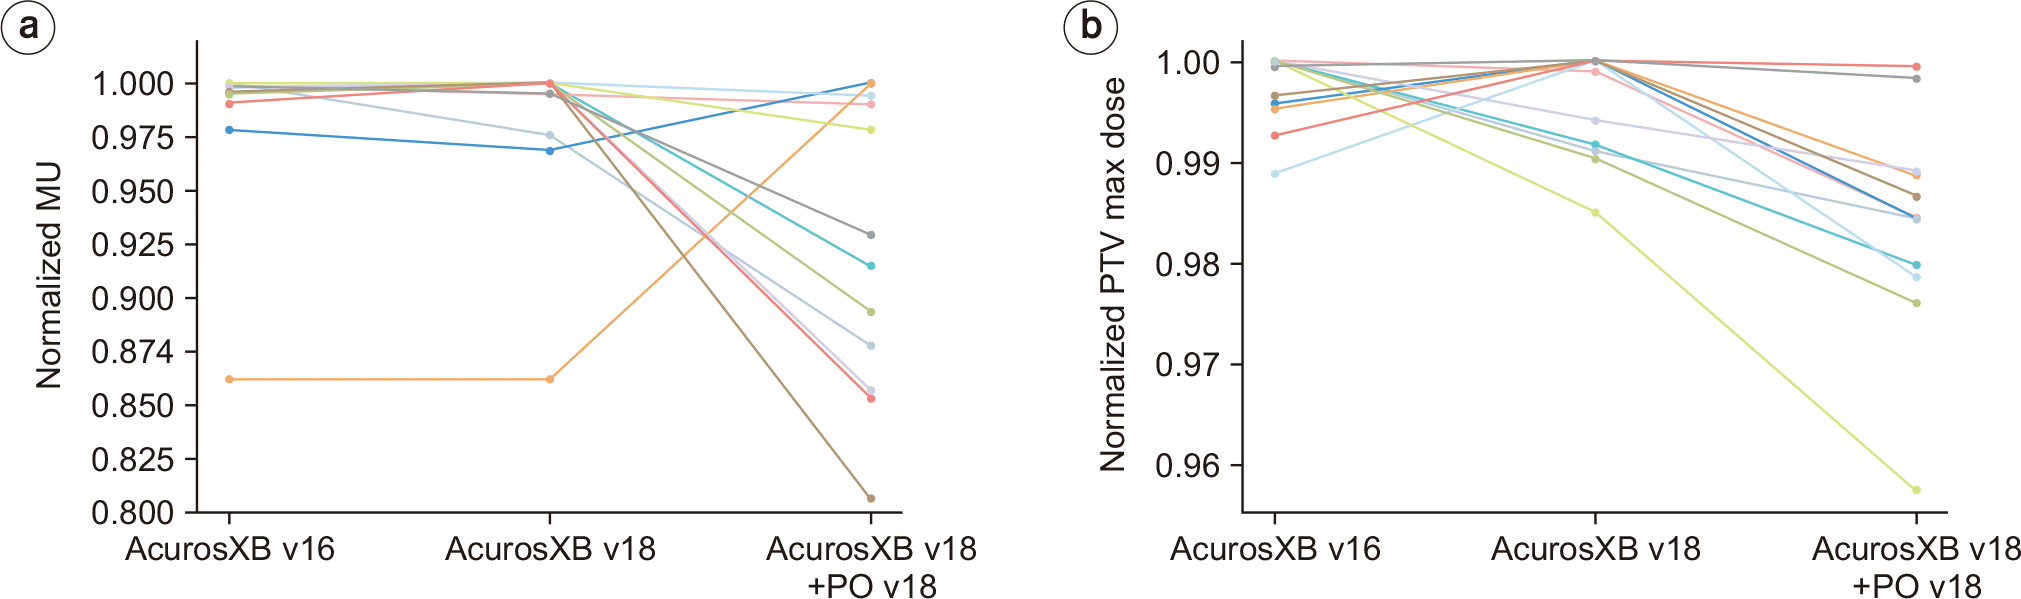
Additionally, for clinical commissioning, GPRs were calculated for the dose distributions computed with v18 and those measured using PDIP. All cases from the evaluated LINACs achieved GPRs above 90%, meeting the clinical acceptance criteria. These plans were not newly optimized but were recalculated using the same treatment parameters to isolate the impact of the dose-calculation algorithm. Furthermore, because the PO algorithm in v18 also incorporates the ELM model, a subset of the treatment plans was re-optimized to assess the potential impact of ELM-based optimization. Twelve treatment plans were reoptimized using PO in AcurosXB v18. One representative plan was selected for each beam energy and LINAC type, reflecting typical anatomical sites for each case. As shown in Fig. 3a, most plans demonstrated a reduction in MUs, except for two cases. However, Fig. 3b shows a consistent decrease in the maximum PTV dose across all cases. These results suggest that optimization using ELM in v18 can produce treatment plans with more efficient dose distributions and reduce the number of unnecessary high-dose regions, enhancing clinical efficiency [12,13].
Future work should evaluate the ELM implementation in the Anisotropic Analytical Algorithm (AAA). Because AAA and AcurosXB differ in their MLC modeling approaches, the findings observed in AcurosXB may not directly translate to AAA. Specifically, AAA employs a simplified fluence-based one-dimensional leaf transmission model. Conversely, AcurosXB uses a three-dimensional ray-tracing–based algorithm that explicitly accounts for scatter, leaf-end curvature, and tongue-and-groove effects. Therefore, comparative studies between the two algorithms would be valuable for evaluating the consistency of ELM implementation and establishing algorithm-specific clinical guidance. Furthermore, this study did not include small-field dosimetry (<3 cm), which is clinically relevant for stereotactic applications such as stereotactic radiosurgery and SABR. Although the three-dimensional ray-tracing approach of the ELM algorithm is theoretically advantageous for improving accuracy in small-field dose calculations, additional experimental validation is necessary to confirm its performance under high-dose-gradient conditions.
In terms of clinical implementation, the leaf modeling algorithm in AcurosXB v18 underwent a fundamental change. Although parameters scaled to match the dose calculated in v16 reproduced similar absolute dose values in v18, the DLG and transmission factors in the ELM algorithm no longer had the same physical meaning as in v16. Because the underlying formulation of the leaf gap and transmission modeling differs between the two versions, the v16 parameters cannot be directly applied to v18 in a physically consistent manner. The primary motivation for this re-examination was that, at our institution, the DLG and transmission factors are not based on direct measurements but are empirically refined through PSQA to improve dose agreement. These empirically tuned parameters have demonstrated clinical validity based on our evaluation of GPRs between v16 and v18. Specifically, for SABR treatments using the TBX 6X-FFF and 10X-FFF beams, the difference between the measured and optimized parameters was relatively large. Therefore, it is recommended to verify these parameters during the transition to v18, especially for beam models showing substantial divergence between measured and clinically optimized values. Since our results showed negligible MU differences between v16 and v18, and since most treatment plans are re-optimized using the PO, the manufacturer’s default beam model protocol can be followed safely during the initial clinical implementation. However, PSQA should always be performed to ensure dose agreement within tolerance levels.
Conclusions
In earlier versions of Eclipse, MLC leaf modeling required empirical optimization of the DLG and transmission values to achieve acceptable PSQA results. These parameters were often tuned to improve GPRs rather than represent the actual physical characteristics of the MLC. In this study, previously optimized parameters were re-evaluated using the upgraded ELM algorithm in Eclipse v18, which incorporates rounded leaf geometry to represent the actual MLC configuration more accurately. Our comparison between v16 and v18 demonstrated that, despite fundamental differences in the modeling functions and allowable DLG ranges, the empirically optimized parameters from the previous version remained clinically consistent when applied to the ELM model. These findings confirm that the optimization strategies used in earlier versions were physically reasonable and verify the robustness and reliability of previously established beam modeling parameters.

 XML Download