



 PDF
 Citation
 Print


INTRODUCTION
Intracranial germ cell tumors (iGCTs) are rare neoplasms, comprising approximately 2%–3% of pediatric brain tumors, with germinomas accounting for roughly two-thirds of all iGCTs [1]. They are generally classified into germinomas and non-germinomatous GCTs (NGGCTs) [234]. Germinomas are highly curable with multimodal treatment approaches, whereas NGGCTs typically exhibit less favorable prognoses and survival outcomes [245]. Notably, the 10-year overall survival (OS) of intracranial and central nervous system (CNS) germinoma is approximately 90% [2678]. Standard treatment for iGCTs includes surgery, chemotherapy, and radiation therapy, all aimed at reducing tumor burden while minimizing long-term toxic effects [2589]. The roles of these treatments differ according to tumor classification. In cases of germinoma, radiation therapy has traditionally been considered a cornerstone of treatment. Although craniospinal irradiation (CSI) has been used, efforts have been made to reduce the radiation field to minimize long-term sequelae [10111213]. Moreover, local radiation therapy alone has been associated with a higher risk of recurrence, which has led to the adoption of whole ventricular irradiation (WVI) as the standard approach. For NGGCTs, the 10-year OS rate remains significantly lower compared with that of germinomas, even when aggressive chemotherapy and high-dose radiotherapy are employed [114]. Given that a higher dose of radiation is required for NGGCTs than for germinomas, debate persists as to whether WVI could replace CSI to reduce radiation-related toxicity.
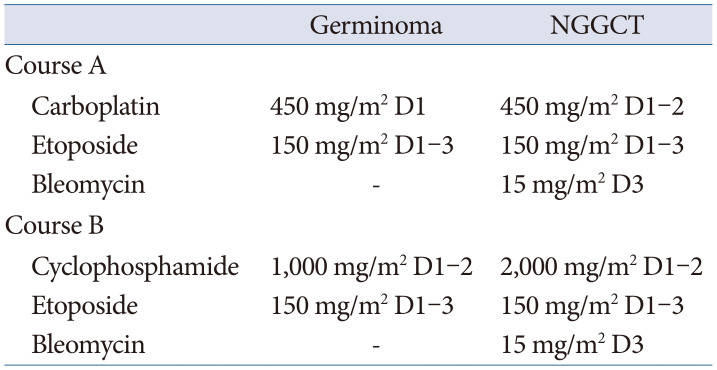
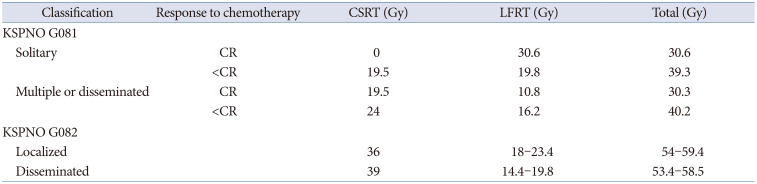
Radiation-induced complications following treatment are often unavoidable, prompting numerous researchers to explore strategies that reduce radiation doses while enhancing the role of chemotherapy to minimize adverse effects [29121516]. The Korean Society of Pediatric Neuro-Oncology (KSPNO) was first launched in 2005 to standardize treatment approaches and improve survival outcomes of iGCTs. The representative clinical trials include the KSPNO G051/G081 protocols for germinoma and the KSPNO G052/G082 protocols for NGGCTs (Table 1) [17]. The G051 protocol was designed to compare the efficacy of low-dose CSI alone versus upfront chemotherapy followed by reduced dose and volume radiation therapy. However, due to poor patient accrual, it was modified in 2008 to the KSPNO G081 protocol, which emphasized upfront chemotherapy followed by reduced-dose radiation therapy (Table 2) [17]. Subsequently, the KSPNO G082 protocol was integrated to refine this approach, ultimately unifying the G081/G082 protocols to optimize outcomes for iGCTs while removing CSI alone as treatment option. The primary objective of the KSPNO protocol was to achieve maximum tumor control while reducing the treatment-related toxicity, thereby maximizing cure rates and improving survivor’s quality of life [17]. In 2009, our institute adopted these KSPNO G081/G082 clinical trial protocol for patients with iGCTs.
This study aimed to analyze the OS and progression-free survival (PFS) of patients with iGCTs treated at our institution. Additionally, we sought to identify factors influencing these outcomes. Through this analysis, we have evaluated the efficacy and safety of the new protocol, thereby contributing to the ongoing refinement of treatment strategies for iGCTs.
MATERIALS AND METHODS
A comprehensive review of electronic medical records was conducted at Seoul National University Bundang Hospital (SNUBH)—a tertiary care center—to identify all histologically and clinically diagnosed GCTs from 2004 through 2019. Among 6,394 patients with intracranial tumors, 61 (0.95%) were diagnosed with iGCTs. After we excluded patients with incomplete medical records (n=2), those lost to follow-up (n=2), and those treated with a single treatment modality (n=8), 49 patients were included in the final analysis.
Most patients (n=38) had histologically confirmed diagnoses. For patients in whom tissue biopsy was challenging due to the tumor location, clinical diagnoses were made based on elevated tumor markers (beta-human chorionic gonadotropin levels in the serum or cerebrospinal fluid >50 mU/mL, serum alpha-fetoprotein levels >10 ng/mL, or cerebrospinal fluid serum alpha-fetoprotein levels >2.0 ng/mL) accompanied by characteristic radiological features.
The primary outcome was OS, defined as the interval from the date of diagnosis, whether diagnosed pathologically or clinically, to the date of death or last follow-up. Clinically diagnosed patients were assigned a diagnosis date based on either the date of reported serologic test results or the date of radiologic test. The secondary outcome, PFS, was defined as the period from the date of diagnosis to the date of disease progression, as confirmed by follow-up MRI. For patients with no evidence of progression, OS and PFS were considered equivalent. Significant adverse events during chemotherapy were defined as grade 3 or higher according to the Common Terminology Criteria for Adverse Events (CTCAE) version 5.0 [18]. Statistical analyses were performed using logistic regression and Kaplan–Meier survival analysis. All analyses were conducted using SPSS Statistics for Windows, version 21 (IBM Corp.).
Patients with pure germinoma were treated according to the KSPNO G081 protocol, while those with NGGCTs received treatment based on the KSPNO G082 protocol. For patients with solitary tumors, the treatment regimen consisted of chemotherapy combined with radiation therapy. Local radiation therapy was performed without CSI if a complete response was observed. CSI was applied to all cases of multiple or disseminated tumors, and a lower dose was applied to achieve complete remission (CR).
Prior to the implementation of the KSPNO protocols, the BEP (bleomycin, etoposide, and cisplatin) regimen was used for the treatment of both middle-aged adult and pediatric patients. The BEP regimen administered every 3 weeks (21 days) for a total of 4 cycles, along with pegfilgrastim (filgrastim), with dosages and schedules adjusted based on patient age and risk factors.
Ethics statements
All procedures performed in studies involving human participants were in accordance with the ethical standards of the Seoul National University Bundang Hospital research committee (IRB No. B-1106-129-803) and with the 1964 Helsinki Declaration and its later amendments or comparable ethical standards. This study was performed retrospectively; consequently, the need for informed consent was waived.
RESULTS
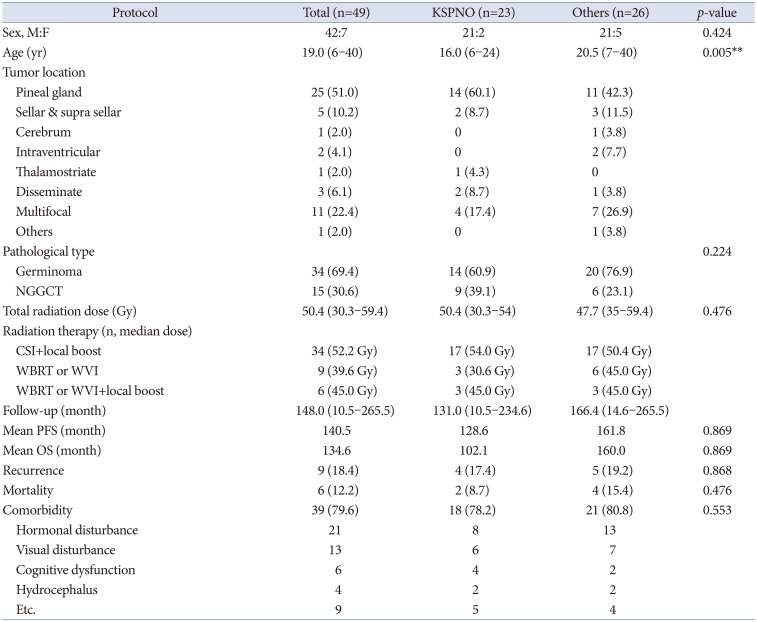
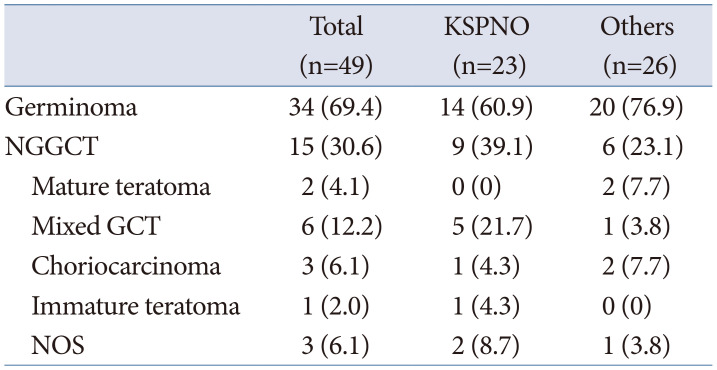
We analyzed 49 consecutive patients with iGCTs; their characteristics are summarized in Table 3. The median follow-up duration was 148.0 months (range: 10.5–265.5). Patients were predominantly male (male-to-female ratio=6:1), with a median age of 19 years (range: 6–40). The pineal region was the most common tumor location (51.0%, n=25). Germinomas were diagnosed in 34 patients (69.4%) and NGGCTs were diagnosed in 15 patients (30.6%). Histological confirmation was obtained in 82.3% (28/34) of germinoma patients and 66.7% (10/15) of NGGCT cases. The detailed distribution of tumor types, including subtypes of NGGCTs, and their allocation between KSPNO and other treatment protocols are presented in Table 4.
Treatment outcomes and survival analysis
Twenty-three patients (46.9%) were treated according to the KSPNO protocol. The median CSI dose with boost was 52.2 Gy, while the median whole-brain or ventricle radiation dose was 39.6 Gy. Within the CSI field, NGGCTs received a significantly higher median radiation dose (33.3 Gy) than germinomas (23.7 Gy; p=0.008). Total radiation doses did not differ significantly between the KSPNO group (median 50.4 Gy) and other protocol groups (median 47.7 Gy; p=0.476).
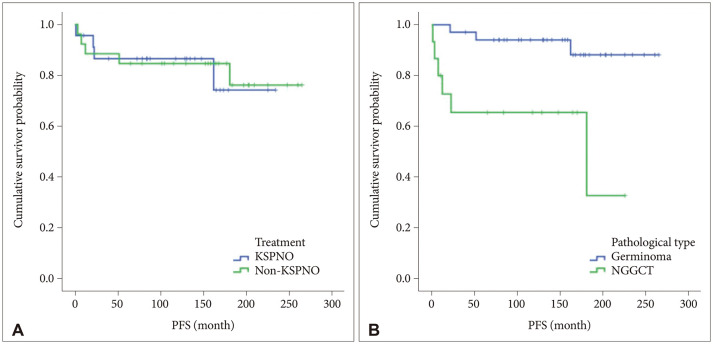
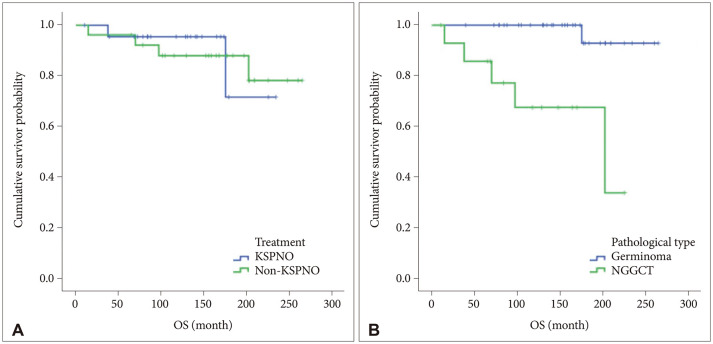
Kaplan–Meier survival curves for PFS and OS are presented in Figs. 1 and 2. The mean PFS was 140.5 months (range: 1.2–265.5) and the mean OS was 134.6 months (range: 10.5–265.5). Nine patients (18.4%) experienced disease recurrence post-treatment. The KSPNO protocol group demonstrated a lower, albeit not statistically significant, recurrence rate compared to other treatment groups (17.4% vs. 19.2%, p=0.868). Pathological subtype analysis revealed significantly improved PFS in the germinoma group compared to the NGGCT group (10-year PFS: 88.1% vs. 32.7%, p=0.003).
Forty-three patients (87.8%) survived throughout the follow-up period. Although no significant OS differences were observed between treatment protocols, a significant difference was noted between pathological subtypes (10-year OS for germinoma vs. NGGCT: 92.9% vs. 67.5%, p<0.001). Among the 49 patients, six deaths occurred during the observation period; disease progression accounted for five deaths, while one patient died of septic shock.
Morbidity and adverse events
Post-treatment morbidity persisted in 39 patients (79.6%). The most prevalent sequelae were hormonal disturbances requiring replacement therapy (53.8%, n=21), followed by visual disturbances (33.3%, n=13), cognitive dysfunction (15.4%, n=6), and hydrocephalus necessitating shunt operation (10.3%, n=4).
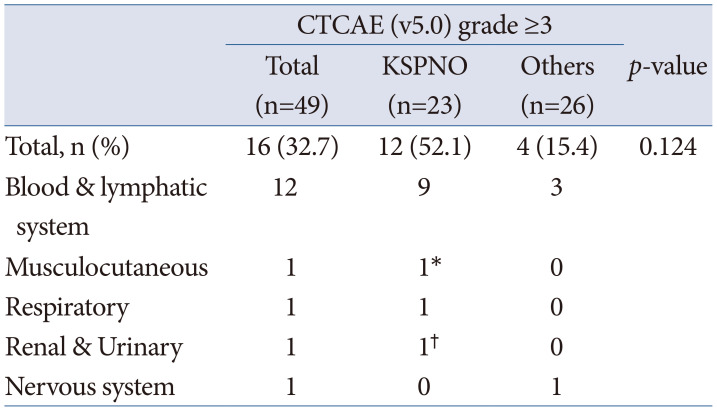
Adverse events of CTCAE grade 3 or higher were observed in 14 patients (28.6%) (Table 5). Blood and lymphatic system disorders, primarily manifesting as neutropenic fever, were the most frequent, occurring in 12 patients. Single cases of musculocutaneous, respiratory, renal, and nervous system complications were also reported. The musculocutaneous and renal system complications coincided with blood and lymphatic system disorders in the affected patients.
DISCUSSION
CNS GCTs exhibit a bimodal age distribution, with a higher prevalence among children and adolescents (particularly among Eastern population), who account for 2%–3% of all primary intracranial tumors [14192021]. These tumors are highly radiosensitive and potentially curable, with radiotherapy alone yielding cure rates of 72%–100% [82223242526]. Management of CNS GCTs may require neurosurgical interventions, such as tumor debulking or biopsy for pathological confirmation, as well as treatment of tumor-related hydrocephalus. The complexity of CNS GCT management necessitates a multidisciplinary approach. However, patients admitted to institutions without an established multidisciplinary team may receive varying treatment protocols depending on the admitting department. This inconsistency highlights the importance of standardized, collaborative care for CNS GCT patients.
The KSPNO introduced the KSPNO-G081/G082 protocol in 2009. Since its implementation, this protocol has been applied to patients diagnosed at Seoul National University Bundang Hospital. The cohort of patients treated under the KSPNO protocol comprises consecutively diagnosed individuals, forming a relatively homogeneous group. The treatment process is coordinated among departments through outpatient clinics and institutional conferences, employing a multidisciplinary approach. In this study, the authors compared and analyzed the KSPNO protocol group with other protocol groups by using shared clinical information across departments. This study was significant for its efforts to validate the effectiveness and safety of the KSPNO protocol.
In recent decades, radiation doses applied to primary sites for CNS germinomas have typically exceeded 50 Gy [1427]. However, the histological similarities among CNS germinoma, testicular seminoma, and ovarian dysgerminoma suggest that CNS germinoma might be effectively treated with lower doses of 25–30 Gy, which are standard for these related tumors [25]. This hypothesis is further supported by a case report by Sung et al. [28] documenting CR at autopsy of a pure CNS germinoma treated with 16 Gy of radiation. Moreover, some studies have demonstrated that radiation doses can be reduced to below 36 Gy in WVI without pre-irradiation chemotherapy while preserving treatment efficacy [729].
A previous study showed that radiotherapy alone is associated with a risk of new CNS relapse [30]. Despite this concern, CNS germinomas generally have a favorable prognosis, with studies reporting a 10-year OS rate of approximately 90%, which aligns with the findings of the present study [2]. While radiation therapy is a cornerstone of treatment for CNS germinomas, it has long-term risks. Radiation-induced secondary brain tumors and subsequent malignant neoplasms, although rare, have been documented in the literature [6263132]. The cumulative risk of developing brain tumors 15 years following cranial irradiation has been estimated at 2.7% [6].
CNS germinomas are highly sensitive to both radiation and chemotherapy. Platinum-based chemotherapy has been shown to reduce late complications associated with radiation therapy while allowing for a reduction in therapeutic radiation doses to 24–30 Gy without compromising treatment efficacy [29121516]. However, some studies have reported treatment failures when radiation fields were limited to the localized germinoma site rather than encompassing the whole ventricular system [10333435].
The KSPNO protocol employs neoadjuvant chemotherapy to maintain therapeutic efficacy while allowing for reduced radiation doses. Recent consensus suggests that radiation fields should encompass at least the whole ventricular system to minimize the risk of local germinoma recurrence [2]. As previously mentioned, several studies have investigated the use of chemotherapy and combination therapy to determine the necessity of CSI based on treatment response. These approaches aim to reduce the final radiation dose and mitigate long-term radiation-related complications [3536373839].
A significant proportion of germinomas occur in the pineal, sellar, and suprasellar regions. Therefore, it is crucial to reduce nephrotoxicity, as patients often experience diabetes insipidus prior to treatment. The KSPNO protocol replaces cisplatin used in traditional regimens with carboplatin, potentially reducing nephrotoxicity relative to conventional therapy. However, cyclophosphamide—also included in the protocol—carries a risk of urotoxicity. To mitigate this risk, MESNA (sodium 2-mercaptoethanol sulfonate) is added to the regimen [3740]. In the KSPNO group, only one instance of a CTCAE grade 3 or higher adverse event affecting the renal system was reported. This patient was hospitalized with gross hematuria—suspected to be hemorrhagic cystitis induced by cyclophosphamide—after completing KSPNO G082 1B. The patient was discharged after 10 days of inpatient treatment. Although patients in the KSPNO group experienced a higher incidence of adverse events, the associated mortality was notably lower. This outcome underscores the overall acceptability of the protocol as a treatment option, balancing efficacy with manageable toxicity.
The therapeutic effect of CSI in germinoma treatment is controversial. The benefit of CSI for patients diagnosed with germinoma has been reported to be approximately 15% [11]. Relapses along the neuroaxis outside the radiation field are uncommon, and the improvements in outcomes with CSI are not substantial [41]. In our study, patients with germinoma who received CSI had a mean PFS of 157.4 months, which was significantly higher than the 146.7 months for those who did not receive CSI (p=0.017). However, the morbidity rate in the CSI group (n=19/22, 86.4%) was higher than that among the patients who underwent irradiation to other sites (n=8/12, 66.7%), although this difference did not reach statistical significance (p=0.221).
These findings highlight the complex risk-benefit profile of CSI in germinoma treatment. While CSI may offer a modest improvement in PFS, it is associated with a trend towards increased morbidity. This underscores the importance of carefully weighing the potential benefits of CSI against its associated risks when determining the optimal treatment strategy for patients with intracranial germinoma. The decision to use CSI should be individualized based on factors such as disease extent, patient age, and potential long-term complications. Further research is needed to identify subgroups of patients who may derive the greatest benefit from CSI while minimizing treatment-related morbidity.
This study did not demonstrate the therapeutic superiority of the KSPNO protocol. Several limitations should be considered when interpreting these results. First, a substantial proportion of patients (47.8%, n=11) in the KSPNO group were classified as high risk, presenting with leptomeningeal seeding or elevated tumor markers. Additionally, the median age at diagnosis in the KSPNO group (16 years) was younger than that in the other group (20.5 years, p=0.005), potentially influencing the adoption of more aggressive treatment plans. Moreover, due to the rarity of the disease, the group size may not have been sufficient to elucidate statistically significant differences between treatment protocols. These factors collectively impact the interpretation of the study results and highlight the challenges in comparing treatment outcomes for rare diseases like intracranial germinomas.
Pathological type is a significant prognostic factor in CNS GCTs. The comparison of the KSPNO protocol with other treatment protocols for iGCTs at a single tertiary institution did not demonstrate its superiority, likely due to a high proportion of high-risk patients, patients being diagnosed at a young age, and the limited sample size.
Nevertheless, the KSPNO protocol remains significant, as it not only establishes a unified treatment approach for CNS GCTs but also demonstrates an acceptable safety profile. Future studies should be designed with larger cohorts, longer follow-up periods, and enhanced risk stratification to better evaluate the protocol's long-term efficacy and safety.

 XML Download