Abstract
The aim of the present study was to utilize magnetic resonance imaging (MRI) as a noninvasive tool for evaluation of the Kambin’s triangle safe zone. Lumbar MRIs of 67 healthy subjects were analyzed. On the coronal plane, the distance from the superior endplate to the nerve root exiting from the dura (distance a), the distance from the lateral aspect of the dura to the medial aspect of the nerve root (distance b), and the angle between the nerve root and plane of the corresponding disc (angle α) was measured. On the axial plane, the vertical distance from the upper facet surface to the exiting nerve root and root-disc distance was also measured. On the sagittal plane, foraminal height, diameter, nerve root-disc distance, and nerve root-pedicle distance were measured. On the coronal plane, right and left α angle was 50.78±4.43 (range, 48.52–51.84 degrees) and 51.07±4.08 (range, 49.25–51.91) degrees, respectively. Distance of right ‘a’ was 17.86±3.86 mm (range, 10.56–24.84 mm) and left ‘a’ was 18.03±3.73 mm (range, 10.98–24.82 mm), distance of right ‘b’ was 15.57±2.61 mm (range, 10.54–20.70 mm) and left ‘b’ was 15.46±2.68 mm (range, 10.93–19.23 mm). All these measurements increased as the spine level went down. Foraminal height and diameter decreased caudally. Nerve root-facet distance did not show change as the level went down. The study indicated that radiologic measurement is feasible to evaluate the anatomy of the Kambin’s triangle. At lower lumbar levels, the exiting nerve root is at risk of injury.
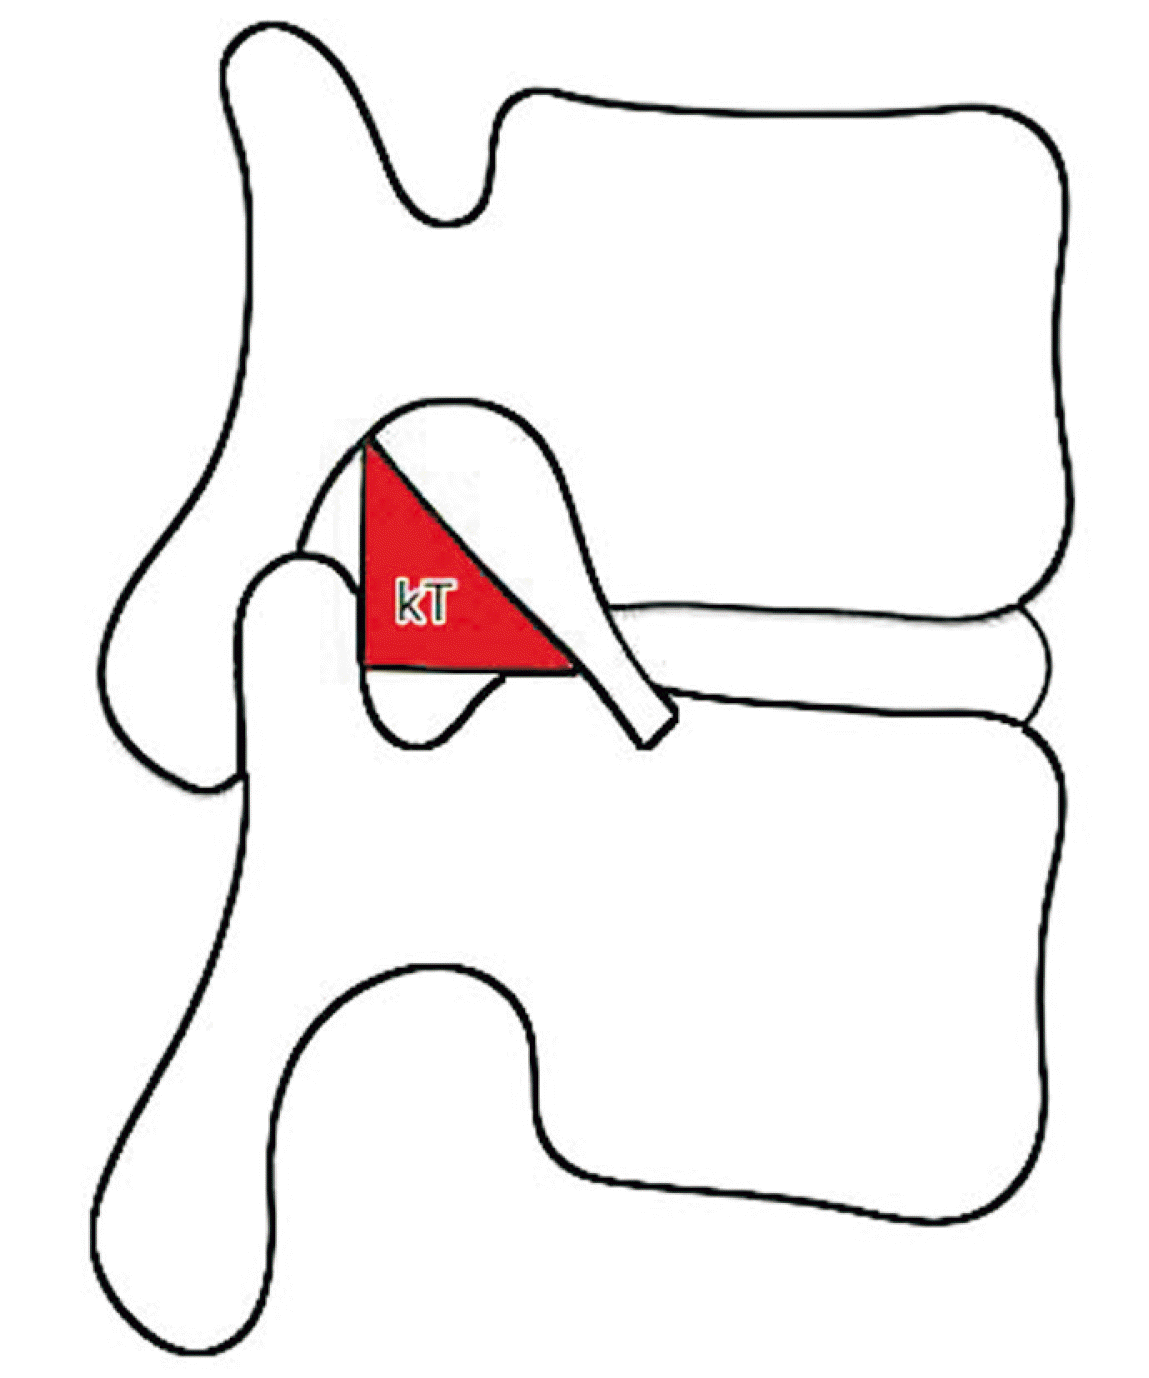
Roughly 70%–85% of individuals will experience low back pain (LBP) at least once in their lifetime. One of the primary causes is disc herniation (DH), which can result in radiculopathy due to both mechanical compression and chemical irritation [1]. Treatment for DH can be conservative or surgical. There are two main categories of surgical treatment for DH: open surgery and minimally invasive surgery [2-4]. Open discectomy approach requires dissection of anatomical structures, which increases the risk of iatrogenic morbidity [5, 6]. Percutaneous posterolateral transforaminal discectomy (PPTD) is a minimally invasive treatment for DH that was first introduced by Kambin and Gellman [7]. Current percutaneous posterolateral discectomies are based on a safe working zone in the posterolateral corner of the disc called Kambin’s triangle. Compared to traditional open surgery, percutaneous posterolateral discectomy has the following significant advantages: shortened operating time, reduced blood loss, and improved early recovery [8, 9]. However, perioperative complications limit further use of this procedure. Postoperative motor weakness due to root exiting injury is a complication of PPTD and is usually caused by the cannula placed in the Kambin’s zone near the nerve root [10-13]. According to topographical description, the Kambin triangle working zone is the region inside a right-angle triangle. The inferior border is formed by rim of the vertebral plate inferior to the target disc, the posterior border is formed by the lateral edge of the superior articular process of the next inferior vertebra, and the hypotenuse is provided by the medial border of the associated spinal nerve as it exits from the foramen (Fig. 1) [14-16]. The size of surgical equipment that can fit through Kambin’s triangle is restricted by its small dimensions.
The Kambin working zone’s dimensions and anatomic boundaries have been described by earlier studies using formalin-fixed cadavers [17-19]. However, the investigation of living individuals is rare. Furthermore, it is apparent that formalin may cause alterations in tissue and modify the Kambin triangle’s anatomical dimensions [20-22]. Therefore, radiologic evaluations are required to determine the Kambin’s zone on different anatomical planes. When compared to cadaveric studies, magnetic resonance images (MRIs) provide measurements that are more clinically accurate. It has been demonstrated that MRI has a special capacity to identify nerve architecture by suppressing fat and vascular signals [23-25].
The aim of the current study is to utilize MRI for evaluation of anatomic parameters of lumbosacral nerve root and adjacent structures in the Kambin working zone of the Iranian population, and further, to analyze the safety of PPTD procedure.
The Ethics Committee of the Ahvaz Jundishapur University of Medical Science assigned patient consent form for this research based on the ethical guidelines for medical and health study involving human subjects established by the Ministry of Health (IR.AJUMS.HGOLESTAN.REC.1401.080) (none of the patients’ identities were disclosed).
A total of 67 healthy volunteers, including 35 females and 32 males (mean age, 43.49 years old) were enrolled in this study. Patient inclusion criteria were: no symptoms or signs of lumbar radiculopathy, complete imaging data. Patients who met the following criteria were excluded: previous lumbar trauma, disc prolapse, lumbar deformity, history of lumbar spine surgery, lumbar spondylolisthesis, scoliosis, rheumatologic, or endocrine diseases. Further, radiography of anteroposterior and lateral views was performed to exclude the subjects of scoliosis, kyphosis, and other degenerative changes.
MRI protocol and measurements: MRI pulse sequences and all measurements of this study were carried out according to two investigations conducted by Guan et al. [24] and Hurday et al. [16]. Images were acquired using a 1.5 Tesla MRI scanner (Magnetom Avanto; Siemens Healthineers). Firstly, T2-weighted (T2W) sequence was performed on a sagittal plane from T12 to S2 with the following parameters: time of repetition (TR)=3,000 ms; time of echo (TE)=100 ms; section thickness, 2 mm; and field of view (FOV) 320×320 mm. On the transverse plane, T2W sequence was performed from L1 to S1 with the following parameters: repetition time TR=3,500 ms; TE=100 ms; section thickness, 3 mm; FOV with 200×200 mm. After that, MRI was done using a three-dimensional (3D) multiple echo recombined gradient echo (MEDIC) sequence on coronal plane (MR neurography). This sequence can suppress the vascular and fat signal to create nerve-selective images and demonstrate nerves in multiple anatomical sections. The imaging parameters were as follows: TR=30.0 ms; TE=12.0 ms; Flip angle=30°, section thickness, 1 mm; FOV: 320×320 mm; and matrix: 256×256 mm.
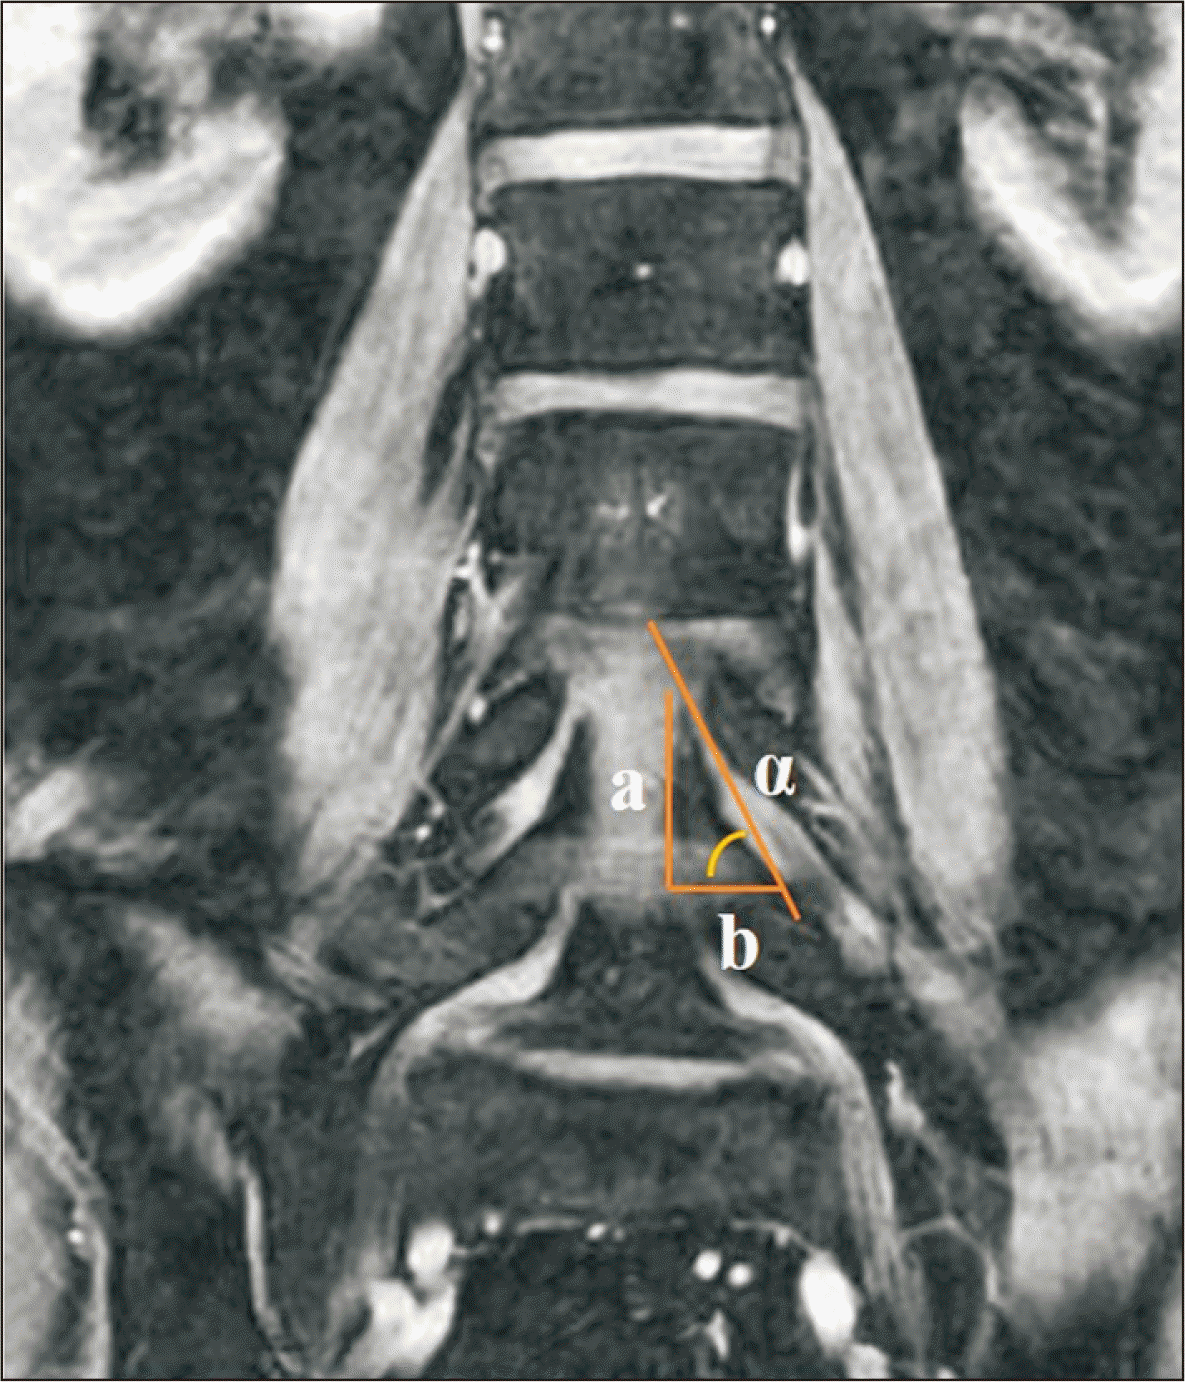
Figs. 2–4 show the measurement methods. For Kambin’s triangle assessment, the following measurements were taken on the coronal plane: 1) the distance of nerve root exiting from the dura to the superior endplate (distance a); 2) the distance from lateral aspect of the dura to the medial aspect of the nerve root along the superior endplate (distance b); and 3) the angle between the exiting nerve root and plane of the corresponding disc (angle α).
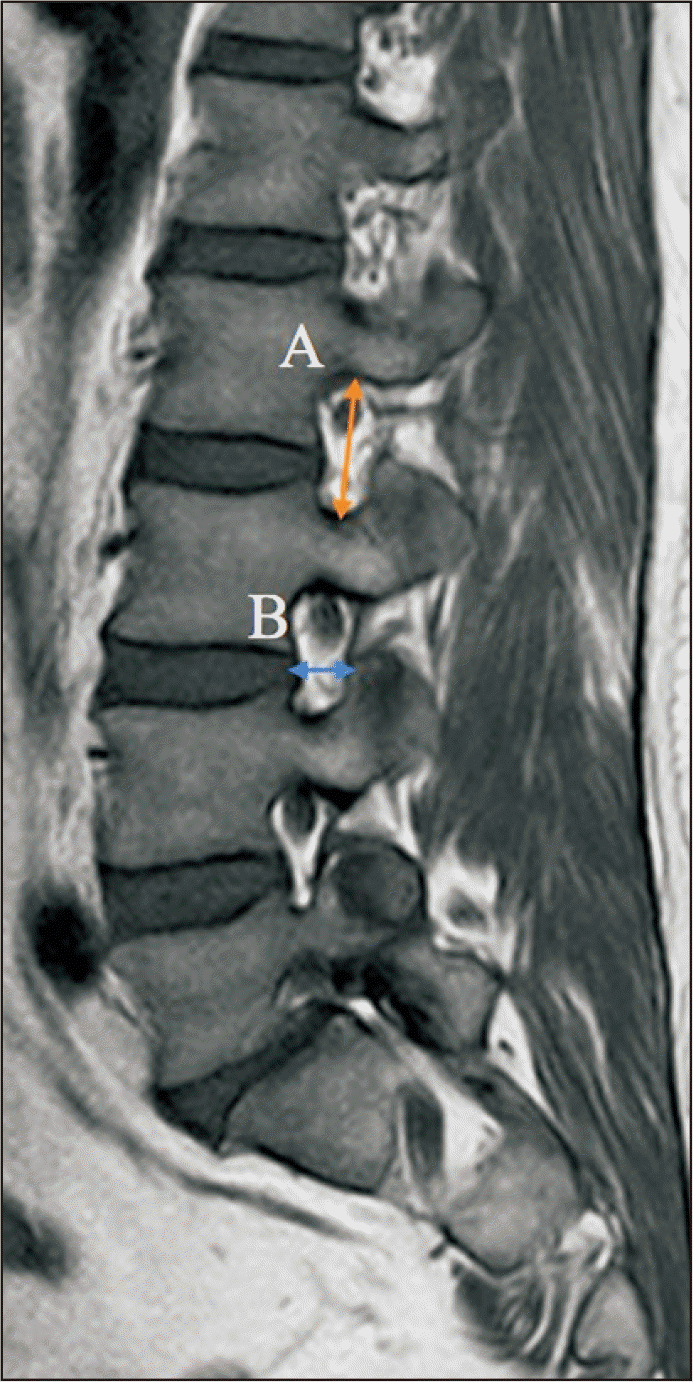
The following measurements were made on the sagittal section (Fig. 3): 1) foraminal height: distance between inferior border of upper pedicle and superior border of lower pedicle (A), 2) foraminal diameter (B): the distance between the facet’s anterior surface and the disc’s posteromiddle corner (Fig. 3).
The following measurements were conducted on the transverse section (Fig. 4): The shortest distance between the anterior surface of a facet and the posterior surface of the vertebral body is known as the foraminal width (Gs). Nerve root-disc distance (Hs): the shortest path between the disc’s posterior surface and nerve root. The smallest distance between the nerve root and the facet’s anterior surface is known as the nerve root-facet distance (Ii). In all sections, disc levels from L1–L2 to L5–S1 were evaluated bilaterally and radiologic measurements were obtained independently by 2 experienced radiologists.
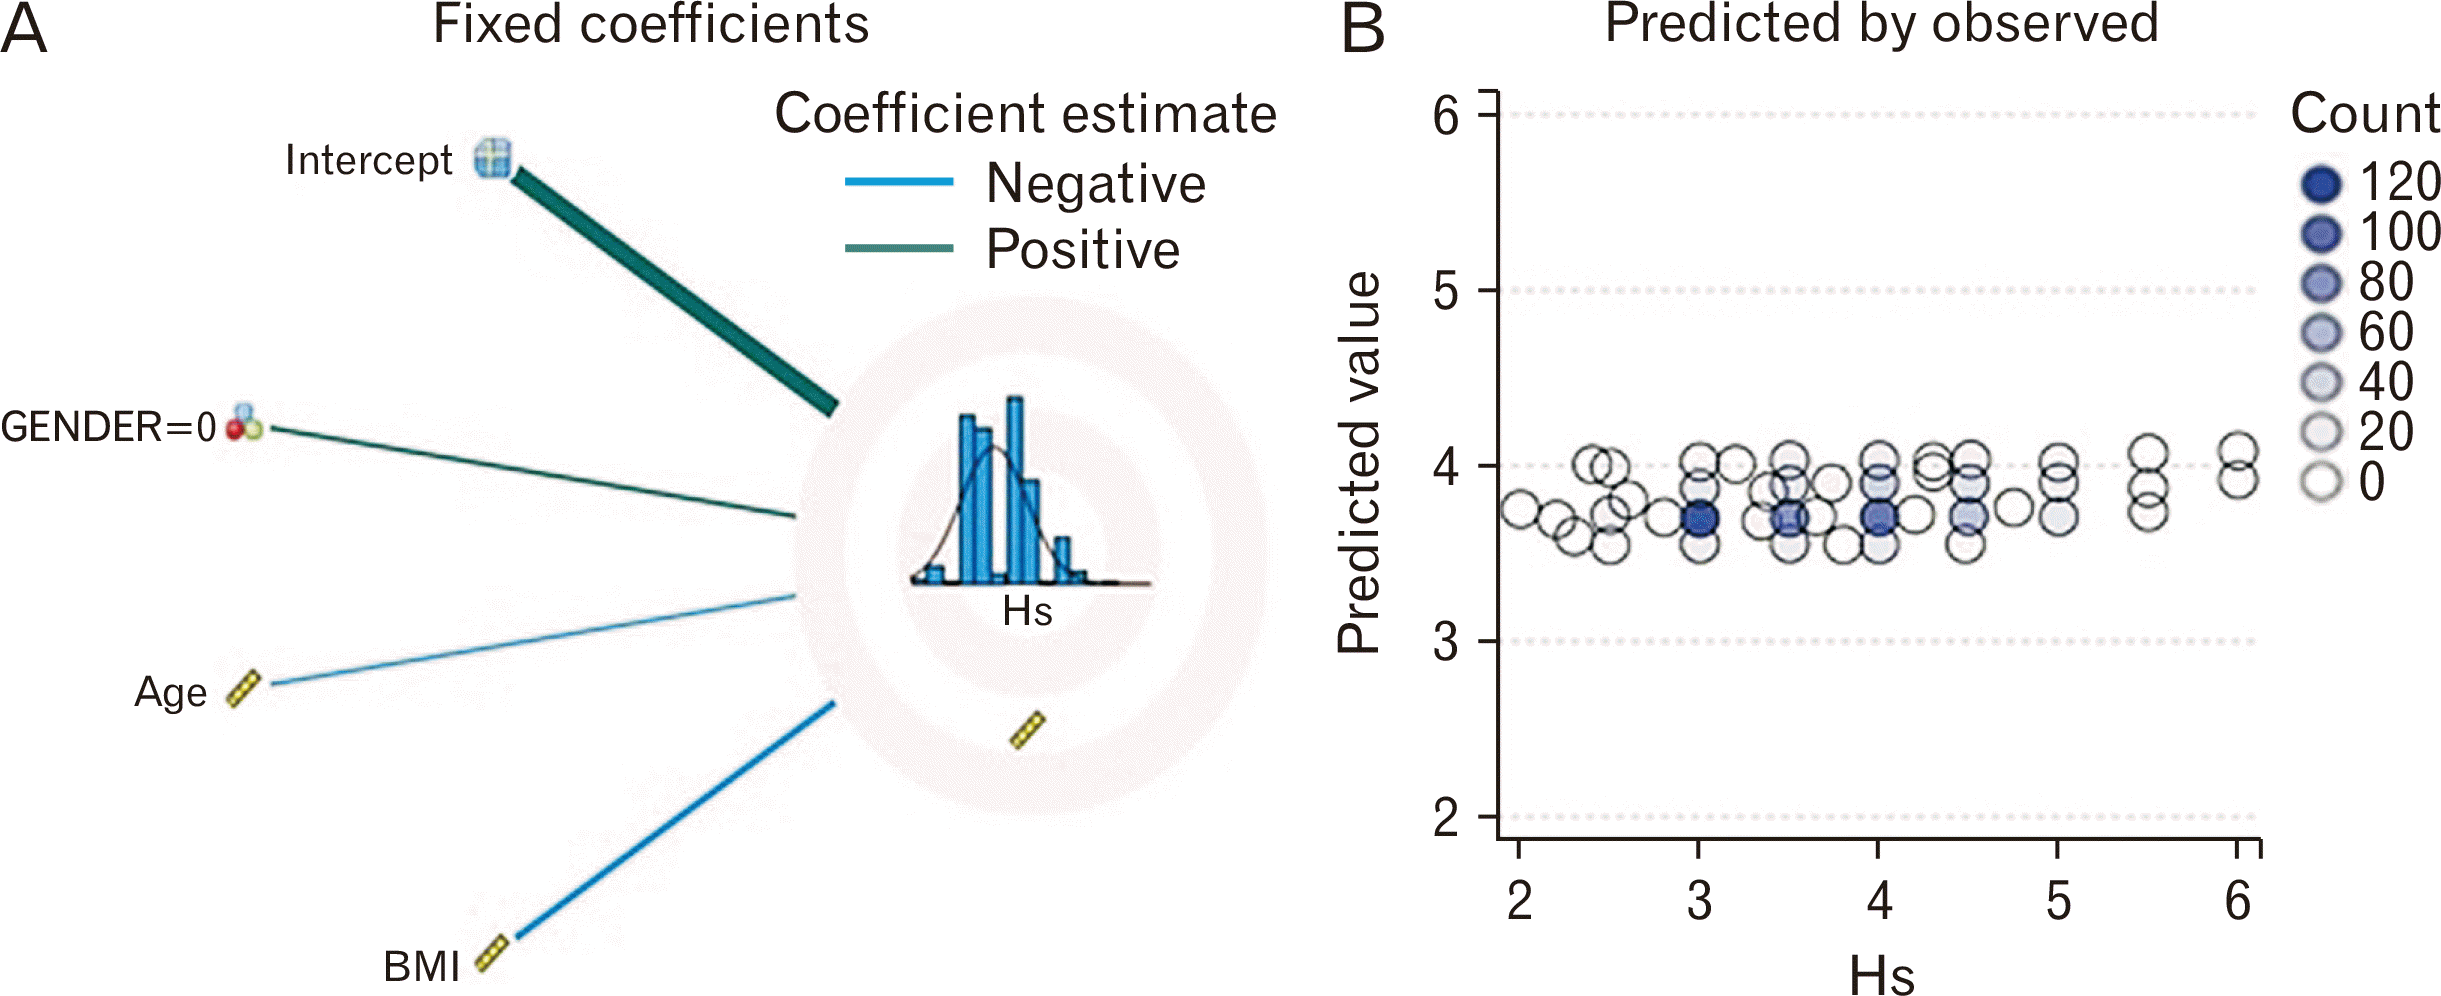
Descriptive statistics were used to report the primary results. The effects roles of age, sex and body mass index (BMI) on the outcome predictions were studied using multilevel mixed effects linear regression. Random intercept of the left and right sides nested within spine levels was added to the models. Model selection strategy involved the inclusion of all the three variables—age, sex, and BMI—in every models. P-value less than 0.1 (one-tailed significance level of 0.05) was regarded as the significance level. The sample size was considered as at least 20 individuals per each model covariate (at least 60 individuals). The statistical analyses were conducted in IBM SPSS Statistics 28 (IBM Co.).
There were a total of 67 patients, 35 females and 32 males (mean age, 43.49 years). The average values for the respective levels and planes are summarized in Tables 1-8. No significant differences were found when comparing the right and left measurements on sagittal, transverse, and coronal planes.
On the coronal plane, the average of right and left angle α was 50.78±4.43 (range, 48.52–51.84 degrees) and 51.07±4.08 (range, 49.25–51.91) degrees, respectively. Distance of right ‘a’ was 17.86±3.86 mm (range, 10.56–24.84 mm) and left ‘a’ was 18.03±3.73 mm (range, 10.98–24.82 mm), distance of right ‘b’ was 15.57±2.61 mm (range, 10.54–20.70 mm) and left ‘b’ was 15.46±2.68 mm (range, 10.93–19.23 mm). For different levels, as the level went down, the values increased. The angles at L2–L3, L3–L4, and L5–S1 levels were larger than those at the upper levels. The mean values for the respective levels were shown in Tables 1-3.
On sagittal plane, foraminal height decreased caudally, biggest foraminal height was measured at L2–L3 (19.33±1.95 mm) and smallest at L5–S1 (15.74±2.1 mm) (Table 4). Foraminal diameters did not show changes at different levels, but could be arranged from longest to closest as follows: L2–L3>L3–L4>L4–L5>L5–S1>L1–L2 (Table 5).
On the transverse plane, Gs from L1 to L5–S1 showed a decrease as the disc level went down. The mean vertical distance from the facet surface to the posterior surface of vertebral body (distance Gs) was 4.56±1.10 for the right side, and 4.49±1.08 for left side (Table 6). Hs decreased caudally, and the mean value was 3.75±0.65 for the right side, and 3.77±0.69 for left side (Table 7). Ii did not show change as the spine level went down, and the mean value was 3.76±0.64 for right side, and 4.1±0.99 for left side (Table 8).
According to the conducted multilevel mixed effects models, the predictive roles of age, sex, and BMI for the radio anatomic factors were as the following (Table 9).
α: each unit increase in BMI was associated with a 0.107-unit decrease in α (P=0.005). Age and sex did not show a considerable association (Table 9, Fig. 5).
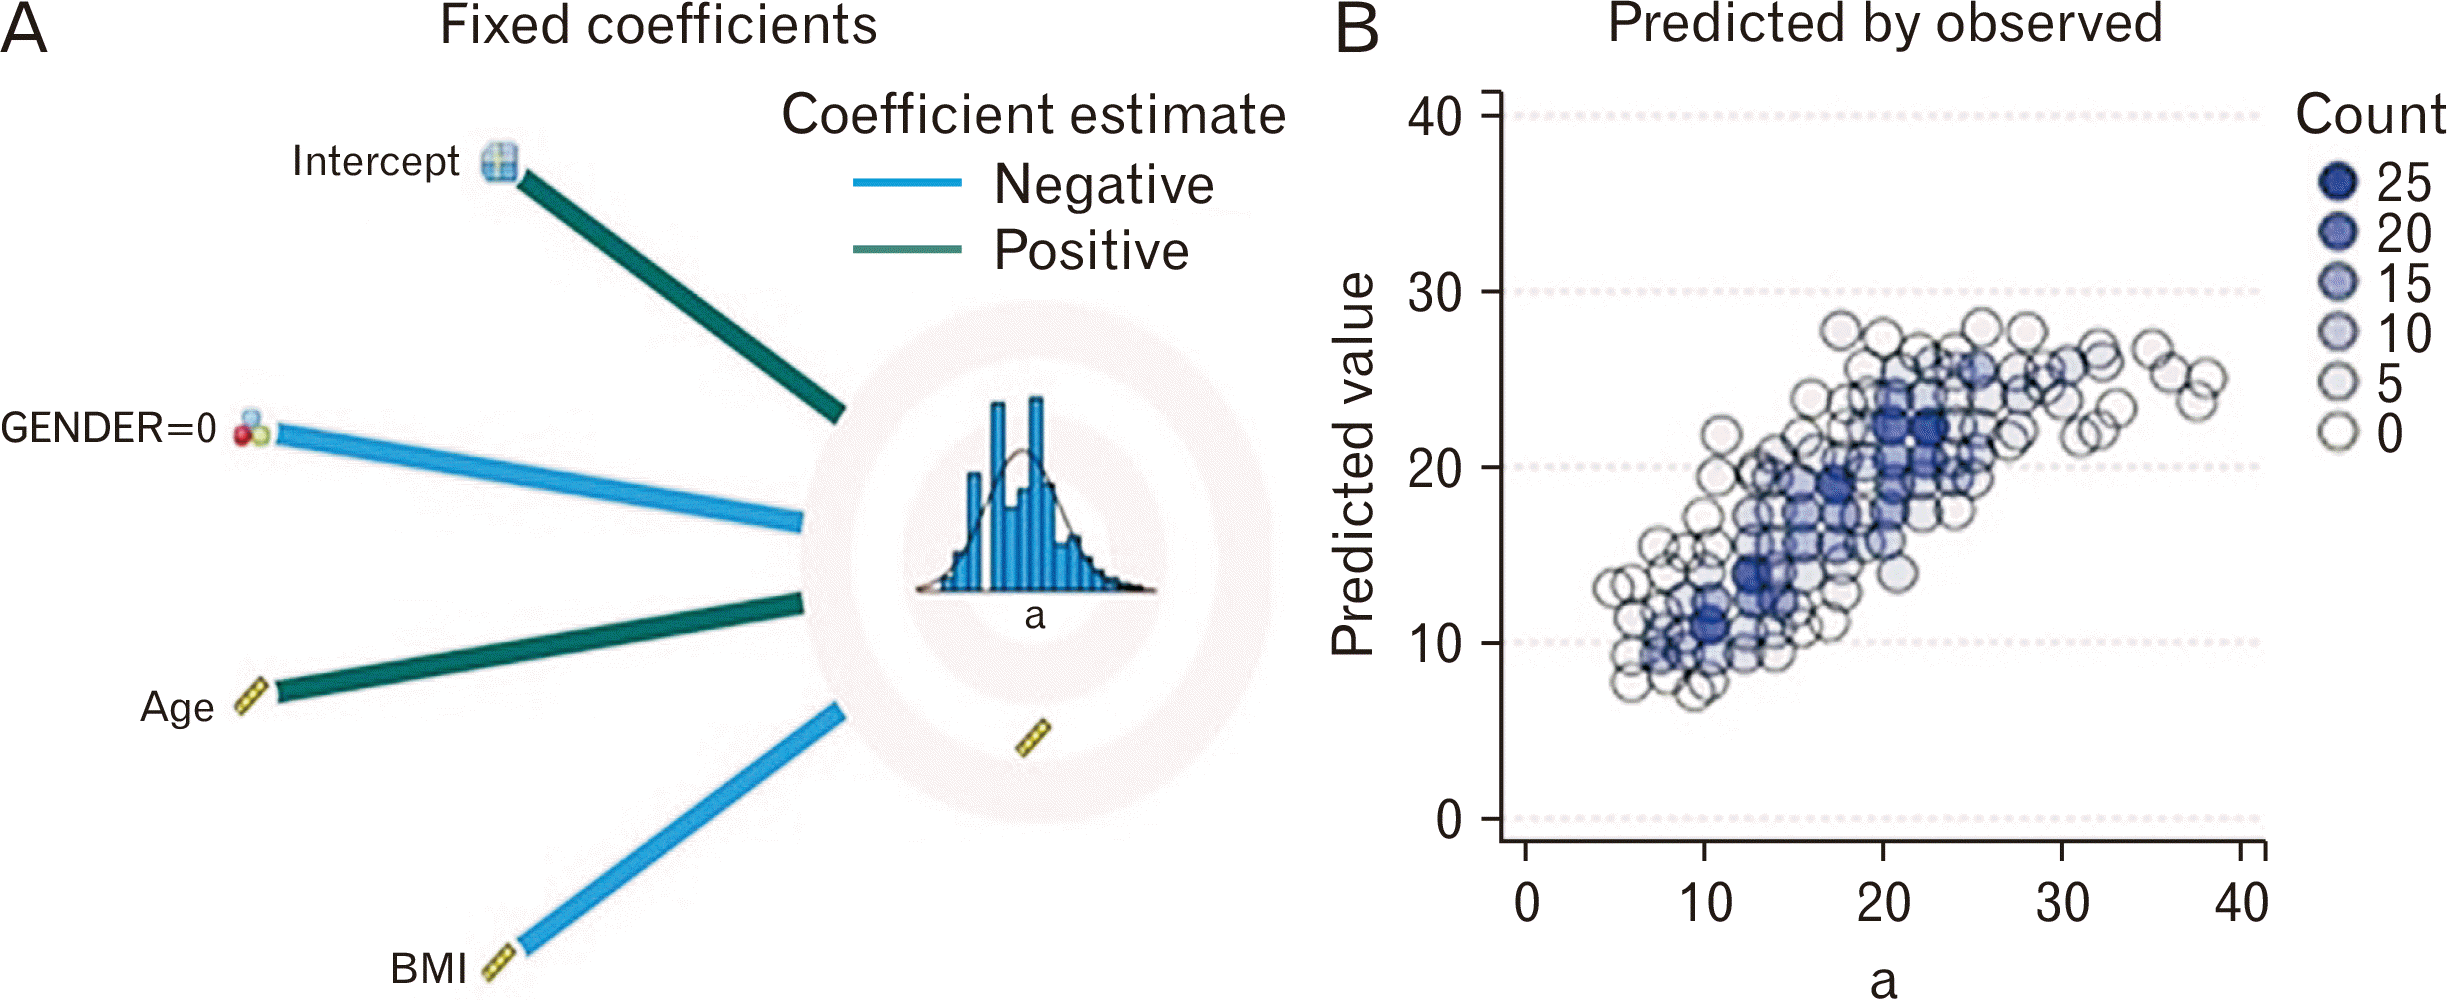
a: female caused a 1.838-unit decrease in a. Each year of increasing age caused a 0.066-unit increase in a. Each unit increase in BMI was associated with a 0.131-unit decrease in a (P>0.001) (Table 9, Fig. 6).
b: female sex caused a 0.912-unit decrease in b. Each year of increasing age caused a 0.072-unit increase in b (P>0.001). BMI did not show a significant relationship (Table 9, Fig. 7).
h: female gender caused a 0.355-unit decrease in h (P=0.024). Each year of increasing age caused a 0.034-unit decrease in h (P>0.001). Each unit increase in BMI was associated with a 0.031-unit decrease in h (Table 9, Fig. 8).
w: each year of increasing age caused a 0.014-unit decrease in w (P>0.001). Gender and BMI did not show a significant relationship with w (Table 9, Fig. 9).
The most common minimally invasive method for treating lumbar disc herniation is PPTD, particularly with regard to intraspinal decompression using the trans foraminal endoscopic spine system. The main goal of PPTD is to remove the herniated nucleus pulposus with the least damage and fewest complications to the musculoskeletal structure [15, 26].
The first definition of the safe working zone for the intervertebral foramen was given by Kambin in a 1991 study on the area of the human intervertebral foramen [27, 28]. The outer upper boundary of this area is the exiting nerve root, the medial boundary is the dural sac or traversing nerve root, the lower boundary is the upper end plate of the inferior vertebral body, and the posterior boundary is the superior articular process of the inferior vertebral body. To reduce the possibility of injury to the exiting nerve root, it is crucial to accurately identify the anatomic relationship between the outgoing nerve root and the superior articular process in Kambin’s triangle of the lumbar intervertebral foramen [27].
The majority of the literature focuses on research performed on cadavers, patients with degenerative spine, and symptomatic subjects [29]. Hoshide et al. [30] conducted an anatomic investigation on Kambin’s triangle and found that its border is a two-dimensional triangular region with an area of 60–108 mm2 which is located between the superior end plate of the inferior vertebral body, the superior articular process, and the exiting nerve root. Based on the cadaveric study, Mirkovic et al. [17] identified the “safe zone” as being 18.9 mm wide and 12.3 mm high, with the size increasing as the level went down. However, the current investigation showed a similar trend, with the largest distance observed located at the lowermost level (L5–S1). These findings are consistent with Guan et al.’s observation [24], which demonstrates the morphometric analysis of the working zone based on MR neurography. According to Guan’s research [24], the narrower Kambin’s angle at higher vertebral levels, the higher the risk of nerve root injury. The results of the current research showed that each unit increase in BMI was associated with a 0.107-unit decrease in α, which was not shown in previous studies. But no significant correlation was observed between gender and age. The investigation found that the mean distance (distance b) between the dura and the nerve root at the level of the superior endplate was 15.51±2.64 mm. This distance was comparable to the findings of Guan et al. [24] and was less than that of the cadaveric analysis. This difference might be the result of formalin fixation, tissue shrinkage and muscle traction. Furthermore, in cadaveric studies, anatomic structures greatly limit the access to L5–S1 level, thus restricting the sample size to a very small number [29].
In the present study, foraminal height decreased caudally and the biggest foraminal height was measured at L2–L3 and the smallest at L5–S1 level; This was consistent with the MRI studies done by Hurday et al. [16] and Al-Hadidi et al. [31] where they measured the mean foraminal height as 20.9±1.7 mm. In the study ahead, the mean foraminal diameters were 8.28±1.04 mm for both sides, and did not show changes at different levels. The research conducted by Min et al. [18] revealed that 15.6% of intervertebral foramens on the sagittal plane had diameters smaller than 7 mm. They concluded that the base dimension was the crucial factor when the disc space height was equal to or greater than that of the working device. According to Choi et al. [11] neural complication rates of PPTD operations decreased by 23% per each 1-mm increase in the distance based on a preoperative MRI scan.
In the current study, there was a decrease in both the Gs and Hs as the disc level went down. Due to limited visual control and the close proximity of the nerve root to the facet or disc, along with narrow Gs in the lower lumbar levels, there is a risk of injuring the exiting root. As a result, experts suggest inserting the working cannula as near as possible to the facet joint, rather than directly targeting the disc. This method should be easily accessible for the upper lumbar levels [11, 32, 33]. Therefore, it is recommended to undergo foraminoplasty in the lower lumbar region to improve the chances of a safer landing and minimize excessive manipulation of the spinal canal contents.
According to the multilevel mixed effects models, the predictive roles of age, sex, and BMI for the radio-anatomic factors showed that each unit increase in BMI was associated with a decrease in α (P=0.005). Age and sex did not show a considerable association. In the present study, ‘a, b,’ and h showed sexual dimorphism, and each year of increasing age caused increase in ‘a’ and ‘b’. Each unit increase in BMI was associated with a decrease in ‘a’ and h. These findings are compatible with previous research which found sexual dimorphism of the lumbar spine [34-36]. Compared with other studies, the unique value of this human MRI study is that we quantified sexual dimorphism in lumbar spines free of pathology and degeneration. Smith et al. [37] found no statistically significant differences between the inter vertebral foramen (IVF) dimensions of male and female in their study of cadavers. According to Vanharanta et al. [38] there is a statistically significant difference in the anterior-posterior dimensions of lumbar IVFs, with women’s IVFs being larger anterior-posterior dimensions than men’s. The findings of Cramer et al. [39] are consistent with the multistage linear regression analysis results of the current study. The different dimensions of Kambin’s triangle varies in the literature, possibly because of differences in the demographics of the study population, genetics, ethnicities, and formalin-fixed cadavers [19, 29, 40, 41]. It is difficult to analyze factors associated with the existence of a different shape of working zone separately because they may coexist in the same patient and at the same disc level. In the present study, multilevel mixed effects linear regression analysis for prediction of radio anatomic factors showed that age, gender and BMI are predictive factors for the working zone.
The present study, as the first research to evaluate the dimension of Kambin’s triangle and its related factors in Iran, reflects the inherent limitations of a cross-sectional study protocol. Firstly, a relatively small sample size may have decreased the statistical power. Therefore, a large sample, multicenter imaging study would be more helpful to analyze the Kambin’s triangle. Second, the aim was not to assess the relationship between the imaging findings and pain or disability. Third was the retrospective nature of the study, which no data exists regarding the sociodemographic condition of patients. Fourth, the inherent nature of conventional MRI which cannot detect cortical bone. Therefore, the results should be interpreted with care.
The present study showed that MR neurography is a practical, noninvasive diagnostic tool to evaluate the anatomical parameters of lumbosacral nerve root and adjacent structures in the working zone of Kambin’s triangle. On coronal plane, the average of α angle was 50.92±4.25 on both sides, and the distance of ‘a’ and ‘b’ decreased as the vertebral level went down. On sagittal plane, foraminal height decreased caudally, biggest foraminal height was measured at L2–L3 and smallest at L5–S1. On transverse plane, Gs from L1 to L5–S1 showed a decrease as the disc level went down. Additionally, this study suggests fewer maneuvers during PPTD, bearing in mind the proximity of the root to the instruments during foraminoplasty. To perform a safer procedure, 3D radiological measurement of the working zone is recommended before PPTD.
Notes
References
1. Williams KD, Park AL. Canale ST, Campbell WC, editors. Lower back pain and disorders of intervertebral discs. Campbell's operative orthopaedics. 10th ed. Mosby;2003. p. 1955–2028.
2. Lühmann D, Burkhardt-Hammer T, Borowski C, Raspe H. 2005; Minimally invasive surgical procedures for the treatment of lumbar disc herniation. GMS Health Technol Assess. 1:Doc07.
3. Nellensteijn J, Ostelo R, Bartels R, Peul W, van Royen B, van Tulder M. 2010; Transforaminal endoscopic surgery for symptomatic lumbar disc herniations: a systematic review of the literature. Eur Spine J. 19:181–204. DOI: 10.1007/s00586-009-1155-x. PMID: 19756781. PMCID: PMC2899820.
4. Tzaan WC. 2007; Transforaminal percutaneous endoscopic lumbar discectomy. Chang Gung Med J. 30:226–34.
5. Thongtrangan I, Le H, Park J, Kim DH. 2004; Minimally invasive spinal surgery: a historical perspective. Neurosurg Focus. 16:E13. DOI: 10.3171/foc.2004.16.1.14. PMID: 15264791.
6. Xin G, Shi-Sheng H, Hai-Long Z. 2013; Morphometric analysis of the YESS and TESSYS techniques of percutaneous transforaminal endoscopic lumbar discectomy. Clin Anat. 26:728–34. DOI: 10.1002/ca.22286. PMID: 23824995.
7. Kambin P, Gellman H. 1983; Percutaneous lateral discectomy of the lumbar spine: a preliminary report. Clin Orthop Relat Res. 174:127–32. DOI: 10.1097/00003086-198304000-00017.
8. Ruetten S, Komp M, Merk H, Godolias G. 2008; Full-endoscopic interlaminar and transforaminal lumbar discectomy versus conventional microsurgical technique: a prospective, randomized, controlled study. Spine (Phila Pa 1976). 33:931–9. DOI: 10.1097/BRS.0b013e31816c8af7. PMID: 18427312.
9. Hermantin FU, Peters T, Quartararo L, Kambin P. 1999; A prospective, randomized study comparing the results of open discectomy with those of video-assisted arthroscopic microdiscectomy. J Bone Joint Surg Am. 81:958–65. DOI: 10.2106/00004623-199907000-00008. PMID: 10428127.
10. Ahn Y, Lee SH, Lee JH, Kim JU, Liu WC. 2009; Transforaminal percutaneous endoscopic lumbar discectomy for upper lumbar disc herniation: clinical outcome, prognostic factors, and technical consideration. Acta Neurochir (Wien). 151:199–206. DOI: 10.1007/s00701-009-0204-x. PMID: 19229467.
11. Choi I, Ahn JO, So WS, Lee SJ, Choi IJ, Kim H. 2013; Exiting root injury in transforaminal endoscopic discectomy: preoperative image considerations for safety. Eur Spine J. 22:2481–7. DOI: 10.1007/s00586-013-2849-7. PMID: 23754603. PMCID: PMC3886527.
12. Lee SH, Kang BU, Ahn Y, Choi G, Choi YG, Ahn KU, Shin SW, Kang HY. 2006; Operative failure of percutaneous endoscopic lumbar discectomy: a radiologic analysis of 55 cases. Spine (Phila Pa 1976). 31:E285–90.
13. Yeung AT, Tsou PM. 2002; Posterolateral endoscopic excision for lumbar disc herniation: surgical technique, outcome, and complications in 307 consecutive cases. Spine (Phila Pa 1976). 27:722–31. DOI: 10.1097/00007632-200204010-00009. PMID: 11923665.
14. Ditsworth DA. 1998; Endoscopic transforaminal lumbar discectomy and reconfiguration: a postero-lateral approach into the spinal canal. Surg Neurol. 49:588–97. discussion 597–8. DOI: 10.1016/S0090-3019(98)00004-4. PMID: 9637618.
15. Parke W. 1991; Anatomy of the spinal nerve and its surrounding structures. Semin Orthop. 6:65–71.
16. Hurday Y, Xu B, Guo L, Cao Y, Wan Y, Jiang H, Liu Y, Yang Q, Ma X. 2017; Radiographic measurement for transforaminal percutaneous endoscopic approach (PELD). Eur Spine J. 26:635–45. DOI: 10.1007/s00586-016-4454-z. PMID: 26922736.
17. Mirkovic SR, Schwartz DG, Glazier KD. 1995; Anatomic considerations in lumbar posterolateral percutaneous procedures. Spine (Phila Pa 1976). 20:1965–71. DOI: 10.1097/00007632-199509150-00001. PMID: 8578369.
18. Min JH, Kang SH, Lee JB, Cho TH, Suh JK, Rhyu IJ. 2005; Morphometric analysis of the working zone for endoscopic lumbar discectomy. J Spinal Disord Tech. 18:132–5. DOI: 10.1097/01.bsd.0000159034.97246.4f. PMID: 15800429.
19. Lertudomphonwanit T, Keorochana G, Kraiwattanapong C, Chanplakorn P, Leelapattana P, Wajanavisit W. 2016; Anatomic considerations of intervertebral disc perspective in lumbar posterolateral approach via Kambin's triangle: cadaveric study. Asian Spine J. 10:821–7. DOI: 10.4184/asj.2016.10.5.821. PMID: 27790308. PMCID: PMC5081315.
20. Arslan M, Cömert A, Açar Hİ, Ozdemir M, Elhan A, Tekdemir I, Tubbs RS, Uğur HÇ. 2012; Nerve root to lumbar disc relationships at the intervertebral foramen from a surgical viewpoint: an anatomical study. Clin Anat. 25:218–23. DOI: 10.1002/ca.21213. PMID: 21671286.
21. Kansu L, Aydın E, Akkaya H, Avcı S, Akalın N. 2017; Shrinkage of nasal mucosa and cartilage during formalin fixation. Balkan Med J. 34:458–63. DOI: 10.4274/balkanmedj.2015.1470. PMID: 28552840. PMCID: PMC5635634.
22. Tran H, Jan NJ, Hu D, Voorhees A, Schuman JS, Smith MA, Wollstein G, Sigal IA. 2017; Formalin fixation and cryosectioning cause only minimal changes in shape or size of ocular tissues. Sci Rep. 7:12065. DOI: 10.1038/s41598-017-12006-1. PMID: 28935889. PMCID: PMC5608899.
23. Chhabra A, Zhao L, Carrino JA, Trueblood E, Koceski S, Shteriev F, Lenkinski L, Sinclair CD, Andreisek G. 2013; MR neurography: advances. Radiol Res Pract. 2013:809568. DOI: 10.1155/2013/809568. PMID: 23589774. PMCID: PMC3622412.
24. Guan X, Gu X, Zhang L, Wu X, Zhang H, He S, Gu G, Fan G, Fu Q. 2015; Morphometric analysis of the working zone for posterolateral endoscopic lumbar discectomy based on magnetic resonance neurography. J Spinal Disord Tech. 28:E78–84. DOI: 10.1097/BSD.0000000000000145. PMID: 25093650.
25. Pairaiturkar PP, Sudame OS, Pophale CS. 2019; Evaluation of dimensions of Kambin's triangle to calculate maximum permissible cannula diameter for percutaneous endoscopic lumbar discectomy: a 3-dimensional magnetic resonance imaging based study. J Korean Neurosurg Soc. 62:414–21. DOI: 10.3340/jkns.2018.0091. PMID: 31079448. PMCID: PMC6616981.
26. He L, Feng H, Ma X, Chang Q, Sun L, Chang J, Zhang Y. 2024; Percutaneous endoscopic posterior lumbar interbody fusion for the treatment of degenerative lumbar diseases: a technical note and summary of the initial clinical outcomes. Br J Neurosurg. 38:573–8. DOI: 10.1080/02688697.2021.1929838. PMID: 34027759.
27. Kambin P. 1991; Arthroscopic microdiskectomy. Mt Sinai J Med. 58:159–64.
28. Schaffer JL, Kambin P. 1991; Percutaneous posterolateral lumbar discectomy and decompression with a 6.9-millimeter cannula. Analysis of operative failures and complications. J Bone Joint Surg Am. 73:822–31. DOI: 10.2106/00004623-199173060-00005. PMID: 1830052.
29. Ozer AF, Suzer T, Can H, Falsafi M, Aydin M, Sasani M, Oktenoglu T. 2017; Anatomic assessment of variations in Kambin's triangle: a surgical and cadaver study. World Neurosurg. 100:498–503. DOI: 10.1016/j.wneu.2017.01.057. PMID: 28132923.
30. Hoshide R, Feldman E, Taylor W. 2016; Cadaveric analysis of the Kambin's triangle. Cureus. 8:e475. DOI: 10.7759/cureus.475.
31. Al-Hadidi MT, Abu-Ghaida JH, Badran DH, Al-Hadidi AM, Ramadan HN, Massad DF. 2003; Magnetic resonance imaging of normal lumbar intervertebral foraminal height. Neurosciences (Riyadh). 8:165–70.
32. Civelek E, Solmaz I, Cansever T, Onal B, Kabatas S, Bolukbasi N, Sirin S, Kahraman S. 2012; Radiological analysis of the triangular working zone during transforaminal endoscopic lumbar discectomy. Asian Spine J. 6:98–104. DOI: 10.4184/asj.2012.6.2.98. PMID: 22708013. PMCID: PMC3372555.
33. Hoogland T, van den Brekel-Dijkstra K, Schubert M, Miklitz B. 2008; Endoscopic transforaminal discectomy for recurrent lumbar disc herniation: a prospective, cohort evaluation of 262 consecutive cases. Spine (Phila Pa 1976). 33:973–8. DOI: 10.1097/BRS.0b013e31816c8ade. PMID: 18427318.
34. Rohmani A, Shafie MS, Nor FM. 2021; Sex estimation using the human vertebra: a systematic review. Egypt J Forensic Sci. 11:25. DOI: 10.1186/s41935-021-00238-2.
35. Lewandowski J, Kocur P, Wendt M, Wiernicka M, Ogurkowska M, Straburzyńska-Lupa A, Goliwąs M, Cieślik K, Waszak M. 2021; Sexual dimorphism of lumbar lordosis and lumbar spine mobility during the period of progressive development. Anthropol Anz. 78:331–46. DOI: 10.1127/anthranz/2021/1355. PMID: 34160544.
36. Amores-Ampuero A, Viciano J. 2020; Sexual dimorphism from vertebrae: its potential use for sex estimation in an identified osteological sample. Australian J Forensic Sci. 54:546–58. DOI: 10.1080/00450618.2020.1840629.
37. Smith GA, Aspden RM, Porter RW. 1993; Measurement of vertebral foraminal dimensions using three-dimensional computerized tomography. Spine (Phila Pa 1976). 18:629–36. DOI: 10.1097/00007632-199304000-00016. PMID: 8484155.
38. Vanharanta H, Korpi J, Heliövaara M, Troup JD. 1985; Radiographic measurements of lumbar spinal canal size and their relation to back mobility. Spine (Phila Pa 1976). 10:461–6. DOI: 10.1097/00007632-198506000-00011. PMID: 2931835.
39. Cramer GD, Cantu JA, Dorsett RD, Greenstein JS, McGregor M, Howe JE, Glenn WV. 2003; Dimensions of the lumbar intervertebral foramina as determined from the sagittal plane magnetic resonance imaging scans of 95 normal subjects. J Manipulative Physiol Ther. 26:160–70. DOI: 10.1016/S0161-4754(02)54109-9. PMID: 12704308.
40. Quester R, Schröder R. 1997; The shrinkage of the human brain stem during formalin fixation and embedding in paraffin. J Neurosci Methods. 75:81–9. DOI: 10.1016/S0165-0270(97)00050-2. PMID: 9262148.
41. Can H, Gomleksiz C, Diren F, Civelek E, Kircelli A, Aydoseli AN, Sencer A. 2020; Anatomical features of neural foramen at T12â€"L1 level for endoscopic transforaminal approach of paramedian and foraminal disc herniations: an anatomical study on fresh human cadavers. Turk Neurosurg. 30:78–82. DOI: 10.5137/1019-5149.JTN.26646-19.4. PMID: 31736029.
Fig. 1
Schematic diagram of the Kambin’s triangle (triangular safe zone) on the sagittal plane. The hypotenuse is bordered medially by the associated spinal nerve, posteriorly by the lateral edge of the superior articular process of the subsequent inferior vertebra, and inferiorly by the rim of the vertebral plate. KT, Kambin’s triangle.
Fig. 2
The magnetic resonance image shows the measurements related to the left side safety working zone at L4–L5 on the coronal plane. Distance a: the distance from the superior endplate to the nerve root exiting from the dura. Distance b: the distance from the lateral aspect of the dura to the medial aspect of the nerve root along the superior endplate. Angle α: the angle between the exiting nerve root and the plane of the corresponding disc.
Fig. 3
Examples of the parameters that are calculated at the middle of the pedicle on the T1-weighted magnetic resonance imaging sagittal section. A, foramina height; B, middle foraminal diameter.
Fig. 4
T2-weighted magnetic resonance image showing the parameters measured on the transverse plane at the superior margin of the disc. Gs, foraminal width; Hs, nerve root-disc distance; Ii, nerve root-facet distance.
Fig. 5
(A) The severity of the correlation between the factors affecting alpha and (B) the model’s goodness of fit in prediction. GENDER=0, female; BMI, body mass index.
Fig. 6
(A) The intensity of the correlation between the factors affecting a and (B) the model’s goodness of fit in prediction. GENDER=0, female; BMI, body mass index.
Fig. 7
(A) The intensity of the correlation between the factors affecting b and (B) the model’s goodness of fit in prediction. GENDER=0, female; BMI, body mass index.
Fig. 8
(A) The intensity of the correlation between the factors affecting h and (B) the model’s goodness of fit in prediction. GENDER=0, female; BMI, body mass index.
Fig. 9
(A) The intensity of the correlation between the factors affecting w and (B) the model’s goodness of fit in prediction. GENDER=0, female; BMI, body mass index.
Fig. 10
(A) The intensity of the correlation between the factors affecting Gs and (B) the model’s goodness of fit in prediction. GENDER=0, female; BMI, body mass index. Gs, foraminal width.
Fig. 11
(A) The intensity of the correlation between the factors affecting Hs and (B) the model’s goodness of fit in prediction. GENDER=0, female; BMI, body mass index. Hs, nerve root-disc distance.
Table 1
Measurement of Kambin’s triangle angle on the coronal plane
Table 2
Comparison of mean value of distance ‘a’ from L1 to L5–S1 disc level
Table 3
Comparison of mean value of distance ‘b’ from L1 to L5–S1 disc level
Table 4
Comparison of mean value of foraminal height (h) (mm) on sagittal plane from L1 to L5–S1 disc level
Table 5
Comparison of mean value of foraminal width on sagittal plane (w) (mm) from L1 to L5–S1 disc level
Table 6
Transverse plane, foraminal width measurements (Gs) (mm) from L1 to L5–S1 disc level
Table 7
Transverse plane, nerve root-disc distance (Hs) (mm) measurements from L1 to L5–S1 disc level
Table 8
Transverse plane, nerve root-facet distance (Ii) (mm) measurements from L1 to L5–S1 disc level
Table 9
Multistage linear regression with mixed effect to predict radioanatomical indices
| Covariates/outcome | Coefficient | Standard error | t | Significant | 95% confidence interval | |
|---|---|---|---|---|---|---|
| Lower | Upper | |||||
| Model term/alpha | ||||||
| Intercept | 55.001 | 3.4137 | 16.112 | <0.001 | 48.298 | 61.704 |
| GENDER=0 | –0.494 | 0.3417 | –1.445 | 0.149 | –1.165 | 0.177 |
| Age (yr) | –0.018 | 0.0121 | –1.505 | 0.133 | –0.042 | 0.006 |
| BMI (kg/m2) | –0.107 | 0.0375 | –2.846 | 0.005a) | –0.180 | –0.033 |
| Var(Intercept) | 10.450 | - | - | - | - | - |
| Var(Index_side(Index_number)) | 1.471 | 0.822 | 1.790 | 0.073 | 0.492 | 4.397 |
| Model term/a | ||||||
| Intercept | 19.762 | 4.5768 | 4.318 | <0.001 | 10.775 | 28.749 |
| GENDER=0 | –1.838 | 0.2705 | –6.795 | <0.001a) | –2.369 | –1.307 |
| Age (yr) | 0.066 | 0.0096 | 6.832 | <0.001a) | 0.047 | 0.084 |
| BMI (kg/m2) | –0.131 | 0.0297 | –4.424 | <0.001a) | –0.189 | –0.073 |
| Var(Intercept) | 17.646 | - | - | - | - | - |
| Var(Index_side(Index_number)) | 26.366b) | 12.530 | 2.104 | 0.035 | 10.388 | 66.923 |
| Model term/b | ||||||
| Intercept | 13.054 | 3.3239 | 3.927 | <0.001 | 6.528 | 19.581 |
| GENDER=0 | –0.912 | 0.1915 | –4.764 | <0.001a) | –1.288 | –0.536 |
| Age (yr) | 0.072 | 0.0068 | 10.603 | <0.001a) | 0.059 | 0.085 |
| BMI (kg/m2) | –0.007 | 0.0210 | –0.325 | 0.745 | –0.048 | 0.034 |
| Var(Intercept) | 9.224 | - | - | - | - | - |
| Var(Index_side(Index_number)) | 14.917b) | 7.073 | 2.109 | 0.035 | 5.889 | 37.783 |
| Model term/h | ||||||
| Intercept | 20.377 | 1.8237 | 11.174 | <0.001 | 16.796 | 23.958 |
| GENDER=0 | –0.355 | 0.1569 | –2.264 | 0.024a) | –0.663 | –0.047 |
| Age (yr) | –0.032 | 0.0056 | –5.731 | <0.001a) | –0.043 | –0.021 |
| BMI (kg/m2) | –0.031 | 0.0172 | –1.796 | 0.073a) | –0.065 | 0.003 |
| Var(Intercept) | 2.914 | - | - | - | - | - |
| Var(Index_side(Index_number)) | 1.886 | 0.920 | 2.050 | 0.040 | 0.725 | 4.906 |
| Model term/w | ||||||
| Intercept | 9.122 | 0.8283 | 11.014 | <0.001 | 7.496 | 10.749 |
| GENDER=0 | –0.082 | 0.0847 | –0.967 | 0.334 | –0.248 | 0.084 |
| Age (yr) | –0.014 | 0.0030 | –4.502 | <0.001a) | –0.019 | –0.008 |
| BMI (kg/m2) | –0.007 | 0.0093 | –0.757 | 0.449 | –0.025 | 0.011 |
| Var(Intercept) | 0.616 | - | - | - | - | - |
| Var(Index_side(Index_number)) | 0.056 | 0.034 | 1.651 | 0.099 | 0.017 | 0.183 |
| Model term/Gs | ||||||
| Intercept | 5.841 | 0.8883 | 6.575 | <0.001 | 4.096 | 7.585 |
| GENDER=0 | –0.099 | 0.0855 | –1.162 | 0.246 | –0.267 | 0.069 |
| Age (yr) | –0.021 | 0.0030 | –7.043 | <0.001a) | –0.027 | –0.015 |
| BMI (kg/m2) | –0.012 | 0.0094 | –1.262 | 0.207 | –0.030 | 0.007 |
| Var(Intercept) | 0.701 | - | - | - | - | - |
| Var(Index_side(Index_number)) | 0.225 | 0.114 | 1.979 | 0.048 | 0.084 | 0.606 |
| Model term/Hs | ||||||
| Intercept | 4.068 | 0.5463 | 7.447 | <0.001 | 2.996 | 5.141 |
| GENDER=0 | 0.052 | 0.0555 | 0.940 | 0.348 | –0.057 | 0.161 |
| Age (yr) | <0.001 | 0.0020 | –0.253 | 0.800 | –0.004 | 0.003 |
| BMI (kg/m2) | –0.011 | 0.0061 | –1.824 | 0.069a) | –0.023 | 0.001 |
| Var(Intercept) | 0.268 | - | - | - | - | - |
| Var(Index_side(Index_number)) | 0.024 | 0.014 | 1.627 | 0.104 | 0.007 | 0.078 |
| Model term/Ii | ||||||
| Intercept | 4.175 | 0.7276 | 5.739 | <0.001 | 2.747 | 5.604 |
| GENDER=0 | –0.033 | 0.0737 | –0.453 | 0.651 | –0.178 | 0.111 |
| Age (yr) | –0.010 | 0.0026 | –3.662 | <0.001a) | –0.015 | –0.004 |
| BMI (kg/m2) | 0.007 | 0.0081 | 0.825 | 0.410 | –0.009 | 0.023 |
| Var(Intercept) | 0.477 | - | - | - | - | - |
| Var(Index_side(Index_number)) | 0.033 | 0.021 | 1.558 | 0.119 | 0.009 | 0.114 |
GENDER=0, female; BMI, body mass index; Var(Intercept), residue variance; Var(Index_side(Index_number)), variance of side nested within lumbar spine number random effects; Gs, foraminal width; Hs, nerve root-disc distance; Ii, nerve root-facet distance; -, not abvailable. a)Significant association at P<0.01; b)Variance of random effect more than variance of residue.


PDF
Citation
Print


XML Download