



 PDF
 ePub
 Citation
 Print


INTRODUCTION
Surgeons are increasingly challenged by opportunistic fungal infections. During the last four decades, the incidence of invasive opportunistic fungal infections has risen dramatically (1). Aspergillus species are ubiquitous molds that are easily isolated from air, soil, decaying vegetation, and dust. These species are the second-most common cause of opportunistic fungal infections, surpassed only by Candida species (2). Cutaneous aspergillosis is a rare form of a locally invasive disease. It generally enters through breaks in the skin, colonizing burns, surgical wounds, or intravenous catheter sites, and subsequently invades viable tissue. Human beings are constantly exposed to this organism, which results in frequent colonization. Cutaneous aspergillosis is most commonly seen in immunocompromised hosts; however, only rarely does Aspergillus behave as a pathogen in an immunocompetent host (2, 3).
Despite the advent of efficacious antimicrobial therapy, combined surgical therapy is still advocated. There could be various surgical therapeutic methods: incision and drainage of abscesses, fistulotomy, sinus tract excision, and more extensive debulking of infected tissue with skin graft or flap coverage are recommended. To the best of our knowledge, this is the first report of flap reconstruction of cutaneous aspergillosis. Therefore, we report our clinical experience with a review of the relevant literature (1, 4).
CASE REPORT
A 45-yr-old man presented with a painful ulcerative lesion on his right elbow. The patient had been treated for herpes zoster 4 yr before and erythematous 1-cm sized painful nodule was noted on his upper arm in the following years. His past medical history was not specific and he had worked as a carpenter for 20 yr. The nodular lesion developed into ulcerative lesion pregressively and finally became a dry, black, escharous lesion with a maximal diameter of 6 cm (Fig. 1). The surrounding skin was erythematous. Neither purulence nor odor was noted, and no localized axillary or generalized lymphadenopathy was observed. Laboratory studies revealed unspecific results, except a mildly elevated white blood cell count. The patient did not exhibit any sensory or motor deficits in his upper extremities, although movement resulted in intermittent pain.
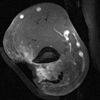
Three-dimensional (3-D) upper extremity computed tomographic (CT) angiography of the lesion revealed a skin defect at the posterolateral aspect of the distal humerus and a low attenuated lesion 3 cm in size that was located intramuscularly and showed rim enhancement. A candidate recipient artery, a 1-2 mm-sized branch of the brachial artery, was marked. Magnetic resonance imaging (MRI) examination showed a chronic inflammatory change of the skin at the subcutaneous fat defect portion and infectious myositis at the triceps muscle (Fig. 2). The possibility of squamous cell carcinoma could not be ruled out. Diagnostic skin punch biopsy demonstrated chronic active inflammation with ulceration and necrosis with regenerating epithelia, but failed to show any microorganism on direct microscopy or in culture.
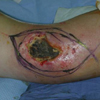
We planned surgical resection of the necrotic skin ulcer and free flap coverage. The necrotic and infected central tissue extending into the subcutaneous fat was removed, and a 2-3 cm rim of non-necrotic, erythematous skin was also removed as the surgical margin (Fig. 3). The lateral side of the triceps muscle and periosteum was also partially excised. No bony involvement was seen on the gross view but elbow joint external capsule was exposed. The wound bed was severely scarred owing to chronic inflammation. We dissected the profunda brachii artery and the vein between the biceps and triceps brachii muscles as a recipient vessel. After identification of the perforator using Doppler sound, a 13×8 cm-sized ipsilateral thoracodorsal perforator flap was designed and elevated. After flap transfer, we performed arterial microanastomosis first between the radial collateral artery and thoracodorsal artery. Finally, we did venous anastomosis between each of vena commitantes.
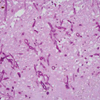
One week postoperatively, permanent pathology with Gomori methenamine silver (GMS) and periodic acid-Schiff (PAS) staining confirmed chronic active inflammation and extensive necrosis with numerous fungal hyphae showing septation and branching consistent with Aspergillus species (Fig. 4, 5). Tissue cultures grew A. fumigatus. After surgery, the patient was started on amphotericin B (20 mg/day) IV for 5 days and switched to oral itraconazole (200 mg q 12 hr) medication. The wound went on to heal satisfactorily, and there has been no evidence of recurrent disease at 2 yr of follow-up (Fig. 6).
DISCUSSION
All Aspergillus species are molds, which together with yeasts are classified as fungi. Aspergillosis is the second-most frequent opportunistic infection, surpassed only by candidiasis (1, 3, 4). There are more than 1,000 species of Aspergillus, but A. fumigatus is the most common cause of colonization and invasive aspergillosis (2, 3). A. fumigatus rarely behaves as a pathogen in an immunocompetent host; however, in an immunocompromised host, it may be invasive and may take a fulminant course. Cutaneous aspergillosis may be primary or secondary to systemic dissemination. It presents as erythematous papules or plaques that evolve into necrotic skin lesions, often at sites of skin trauma associated with intravenous catheters and placement of adhesive tape or monitor leads, or at sites of surgical or other traumas (5, 6). If hyphae are somehow able to develop, functioning neutrophils remove them efficiently. If these host defenses fail, infection may develop.
The prompt recognition and appropriate treatment of cutaneous fungal disease is critical to the prevention of adverse outcomes, but aspergillosis poses some unique diagnostic and therapeutic challenges. Skeletal aspergillosis usually conflicts with neoplastic or inflammatory diseases. Radiographic studies may be helpful, but not confirmatory. Aspergillosis may initially present to the clinician as a painful and locally destructive lesion. The typical lesion is an erythematous (or violaceous), edematous, indurated papule or nodule that progresses to a blue-black necrotic ulcer with a black eschar due to regular invasion into blood vessels, causing local thrombosis and hemorrhage (2-5). Tissue biopsy with special stains and tissue culture are the preferred methods for the diagnosis of aspergillosis. Fungal hyphae can be seen in hematoxylineosin-stained sections, but staining with periodic acid-Schiff or Gomori methenamine silver highlights their morphological characteristics, as in our case (2-4).
Treatment of cutaneous aspergillosis includes a combination of surgical debridement and multi-drug antifungal chemotherapy. Amphotericin B, often in combination with flucytosine, is considered the first-line therapy. Then a switch to itraconazole (or voriconazole) oral medication for several months is a recent trend of drug therapy. Itraconazole has some disadvantage of gastrointestinal trouble and unpredictable outcome. If patients do not respond to oral itraconazole therapy, serum itraconazole levels must be checked to ensure therapeutic dosages, and cultures checked for sensitivity to itraconazole (2-5).
Despite the advent of efficacious antimicrobial therapy, combined surgical therapy is still advocated (5-7). Surgical treatment ranges from simple excision to radical debridrment. Simple, reliable coverage should be the goal for debilitated patients with multisystem dysfunction (coagulation factors, steroids, immunosuppression, anemia, malnutrition, etc.). Skin grafting, healing by secondary intention, and local flaps are the safest, most reliable choices in this compromised population (8-10). Our patient was relatively healthy, and the wound demanded free flap coverage as a treatment choice in the aspects of defect size and depth. Our case is unique in the cutaneous fungal infections, and suggests that free flap coverage could be a useful addition to the therapeutic arsenal in select cases of extensive cutaneous fungal infections.




 XML Download