



 PDF
 ePub
 Citation
 Print


References
1. Saxena R. Practical hepatic pathology: a diagnostic approach. Philadelphia, PA: Elsevier;2011. p. 473–488.
2. Agrawal S, Agarwal S, Arnason T, Saini S, Belghiti J. Management of hepatocellular adenoma: recent advances. Clin Gastroenterol Hepatol. 2015; 13:1221–1230.

3. Dhingra S, Fiel MI. Update on the new classification of hepatic adenomas: clinical, molecular, and pathologic characteristics. Arch Pathol Lab Med. 2014; 138:1090–1097.
4. Han JK, Eun HW, Kim SH. Imaging findings of hepatic adenoma. Korean J Hepatol. 2008; 14:405–410.
5. Ichikawa T, Federle MP, Grazioli L, Nalesnik M. Hepatocellular adenoma: multiphasic CT and histopathologic findings in 25 patients. Radiology. 2000; 214:861–868.
6. Grazioli L, Morana G, Kirchin MA, Schneider G. Accurate differentiation of focal nodular hyperplasia from hepatic adenoma at gadobenate dimeglumine-enhanced MR imaging: prospective study. Radiology. 2005; 236:166–177.
7. van Aalten SM, Thomeer MG, Terkivatan T, et al. Hepatocellular adenomas: correlation of MR imaging findings with pathologic subtype classification. Radiology. 2011; 261:172–181.
8. Bioulac-Sage P, Laumonier H, Couchy G, et al. Hepatocellular adenoma management and phenotypic classification: the Bordeaux experience. Hepatology. 2009; 50:481–489.
9. Farges O, Dokmak S. Malignant transformation of liver adenoma: an analysis of the literature. Dig Surg. 2010; 27:32–38.
10. Ahn SY, Park SY, Kweon YO, Tak WY, Bae HI, Cho SH. Successful treatment of multiple hepatocellular adenomas with percutaneous radiofrequency ablation. World J Gastroenterol. 2013; 19:7480–7486.
11. Nasser F, Affonso BB, Galastri FL, Odisio BC, Garcia RG. Minimally invasive treatment of hepatic adenoma in special cases. Einstein (Sao Paulo). 2013; 11:524–527.
Fig. 1.
Abdominopelvic CT. In the hepatovenous phase, a 3.2-cm sized hypovascular mass is seen in S5/6 of the liver.
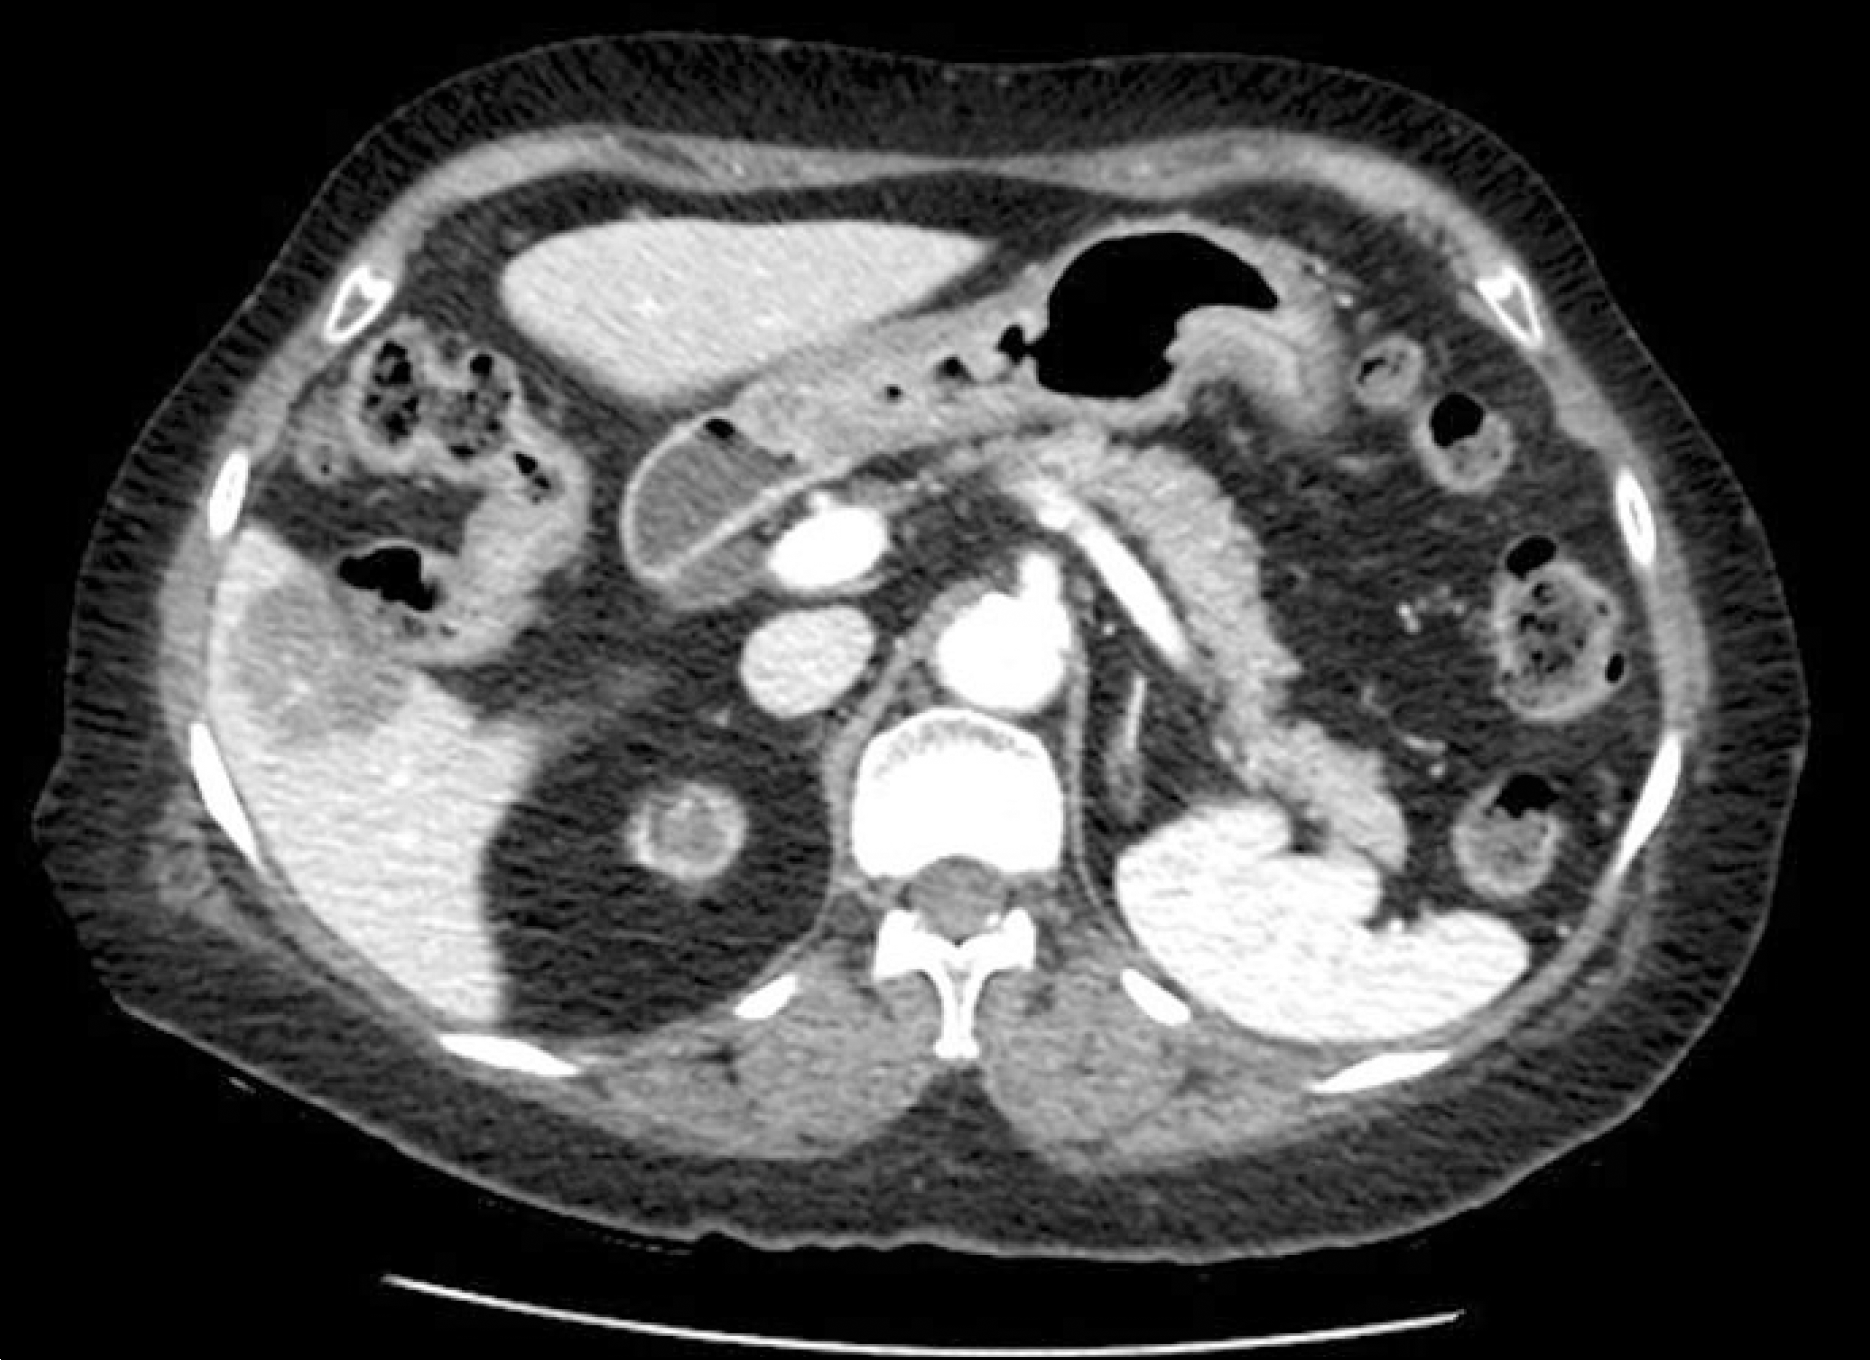
Fig. 2.
MRI findings. A 3.2-cm sized mass in S5 of the liver shows heterogeneously increased signal on T2-weighted image (A) and delayed enhancement on 15 minute delayed phase (B). Multiple small hypovascular noncystic lesions are also found in the liver (C).
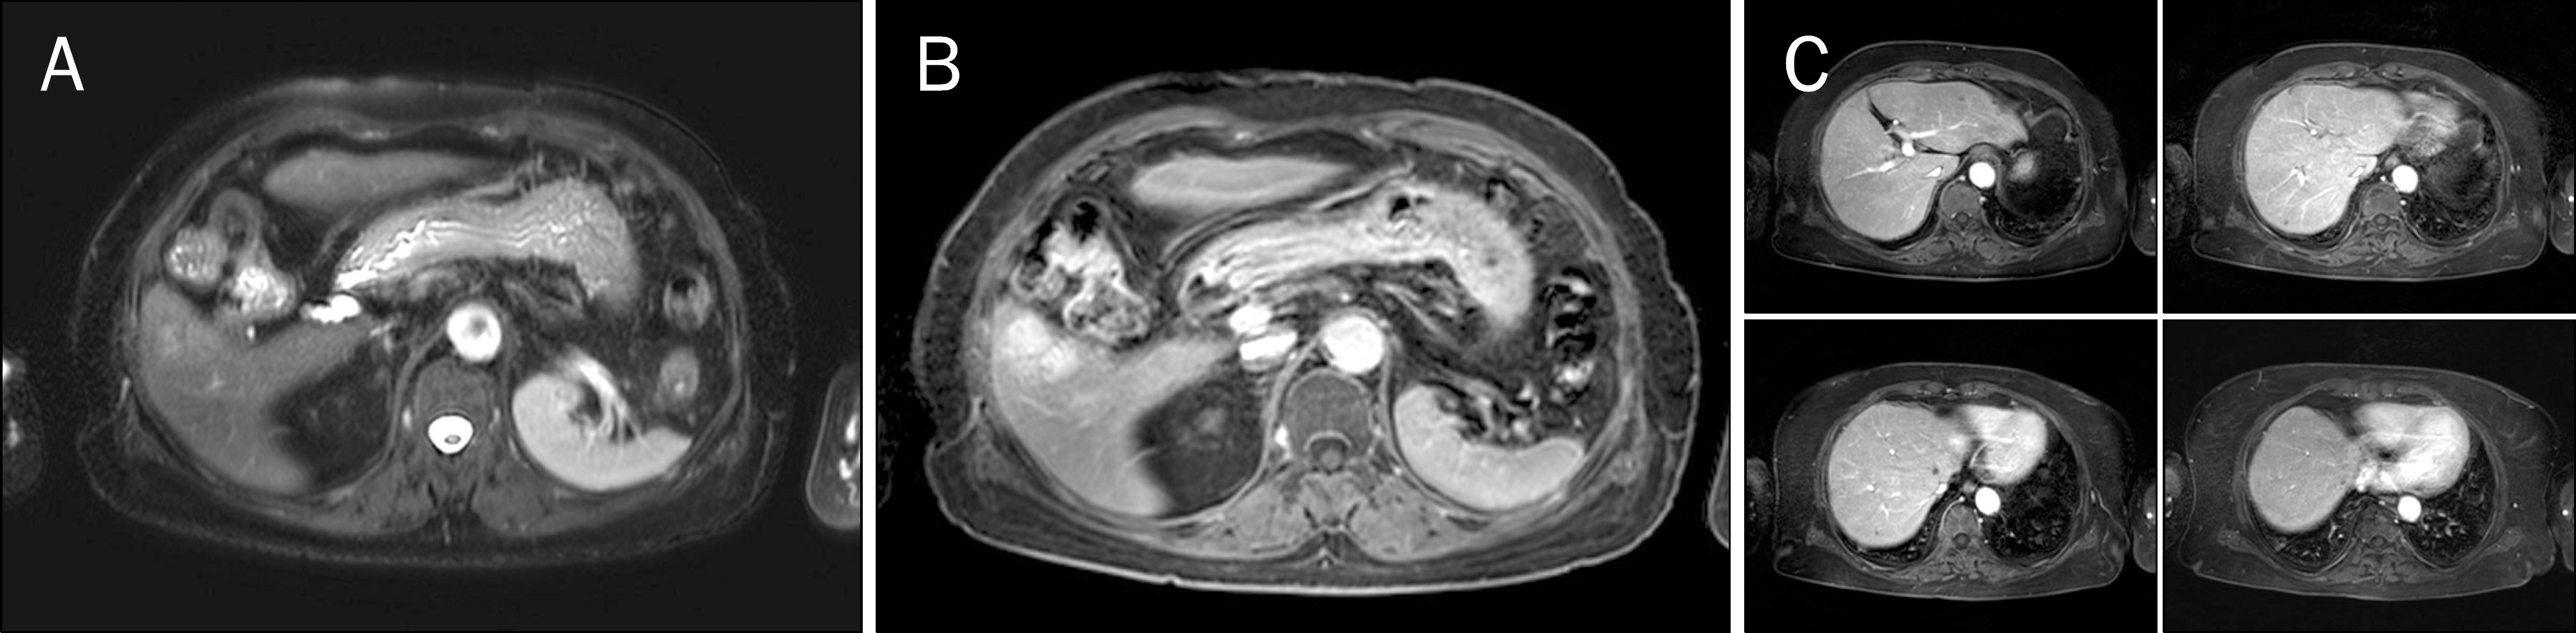
Fig. 3.
Pathologic findings of an initial biopsy specimen. (A) Sinusoidal dilatation and attenuated hepatic cords are seen (H&E stain, ×100).(B) Sinusoidal capillarization in the lesion is evident upon CD34 immunohistochemical staining (CD34 stain, ×40). (C) An inflammatory protein, CRP is positive (CRP stain, ×100). (D) -catenin shows an intact membranous expression (-catenin stain, ×100).

Fig. 4.
Follow-up MRI. The hepatic mass in S5/6 of the liver has enlarged from 3.1 to 4.1 cm (A, B), and the number and sizes of small hypovascular lesions in both hepatic lobes have increased (C).
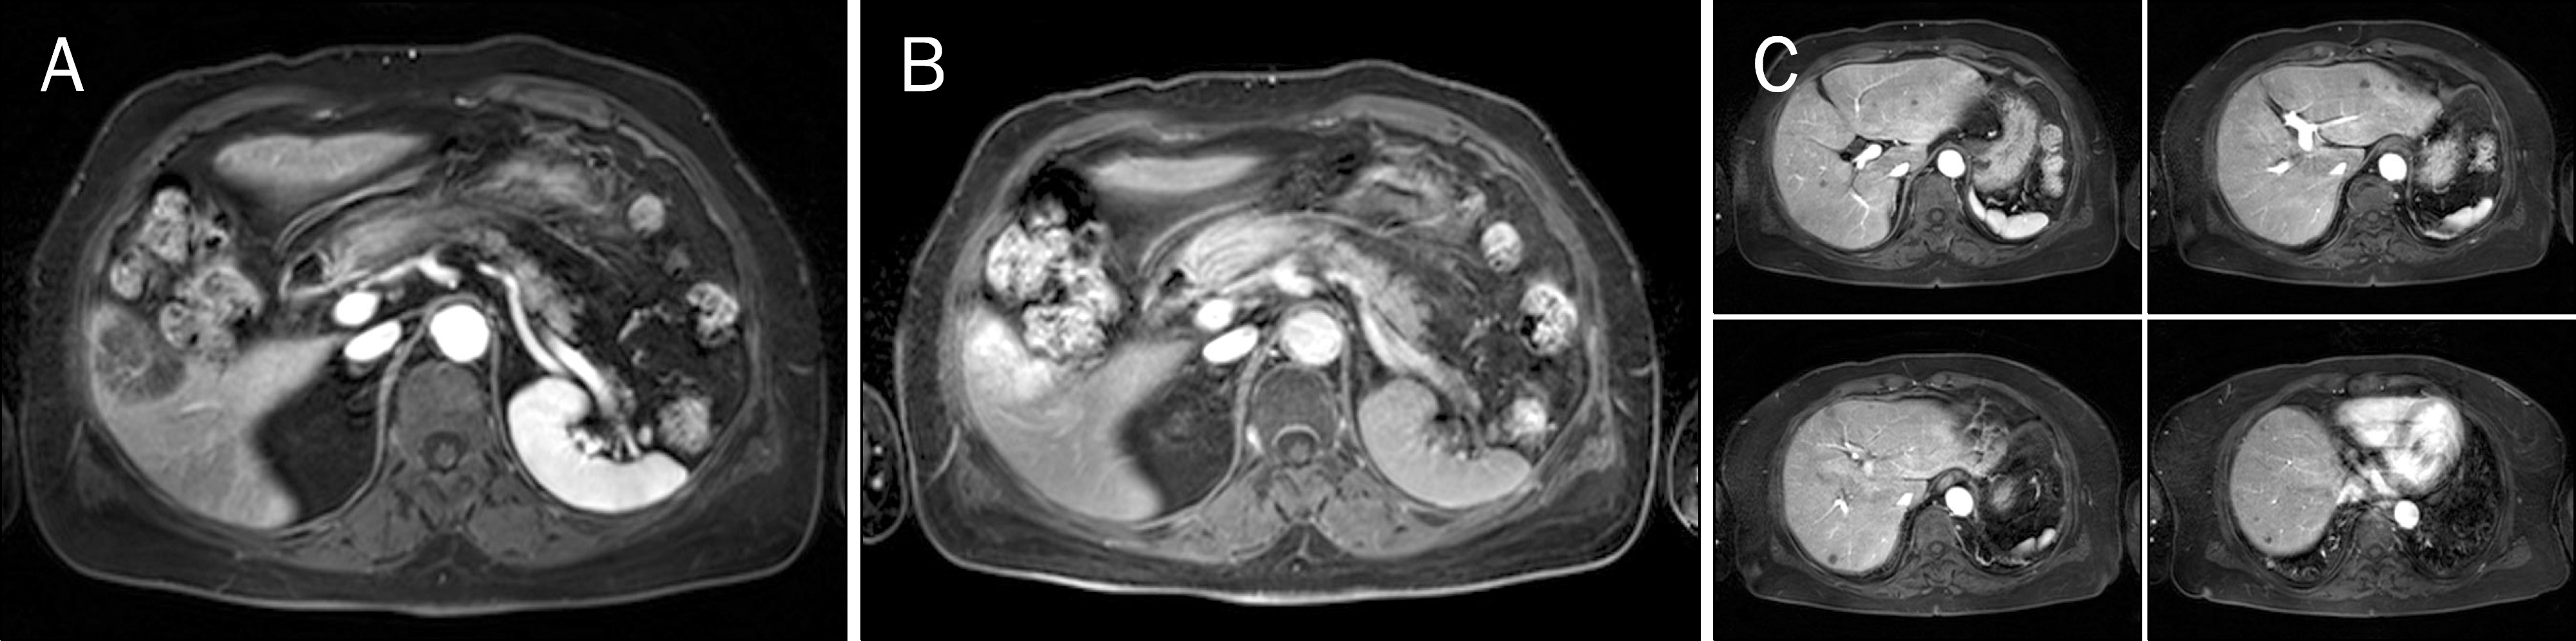
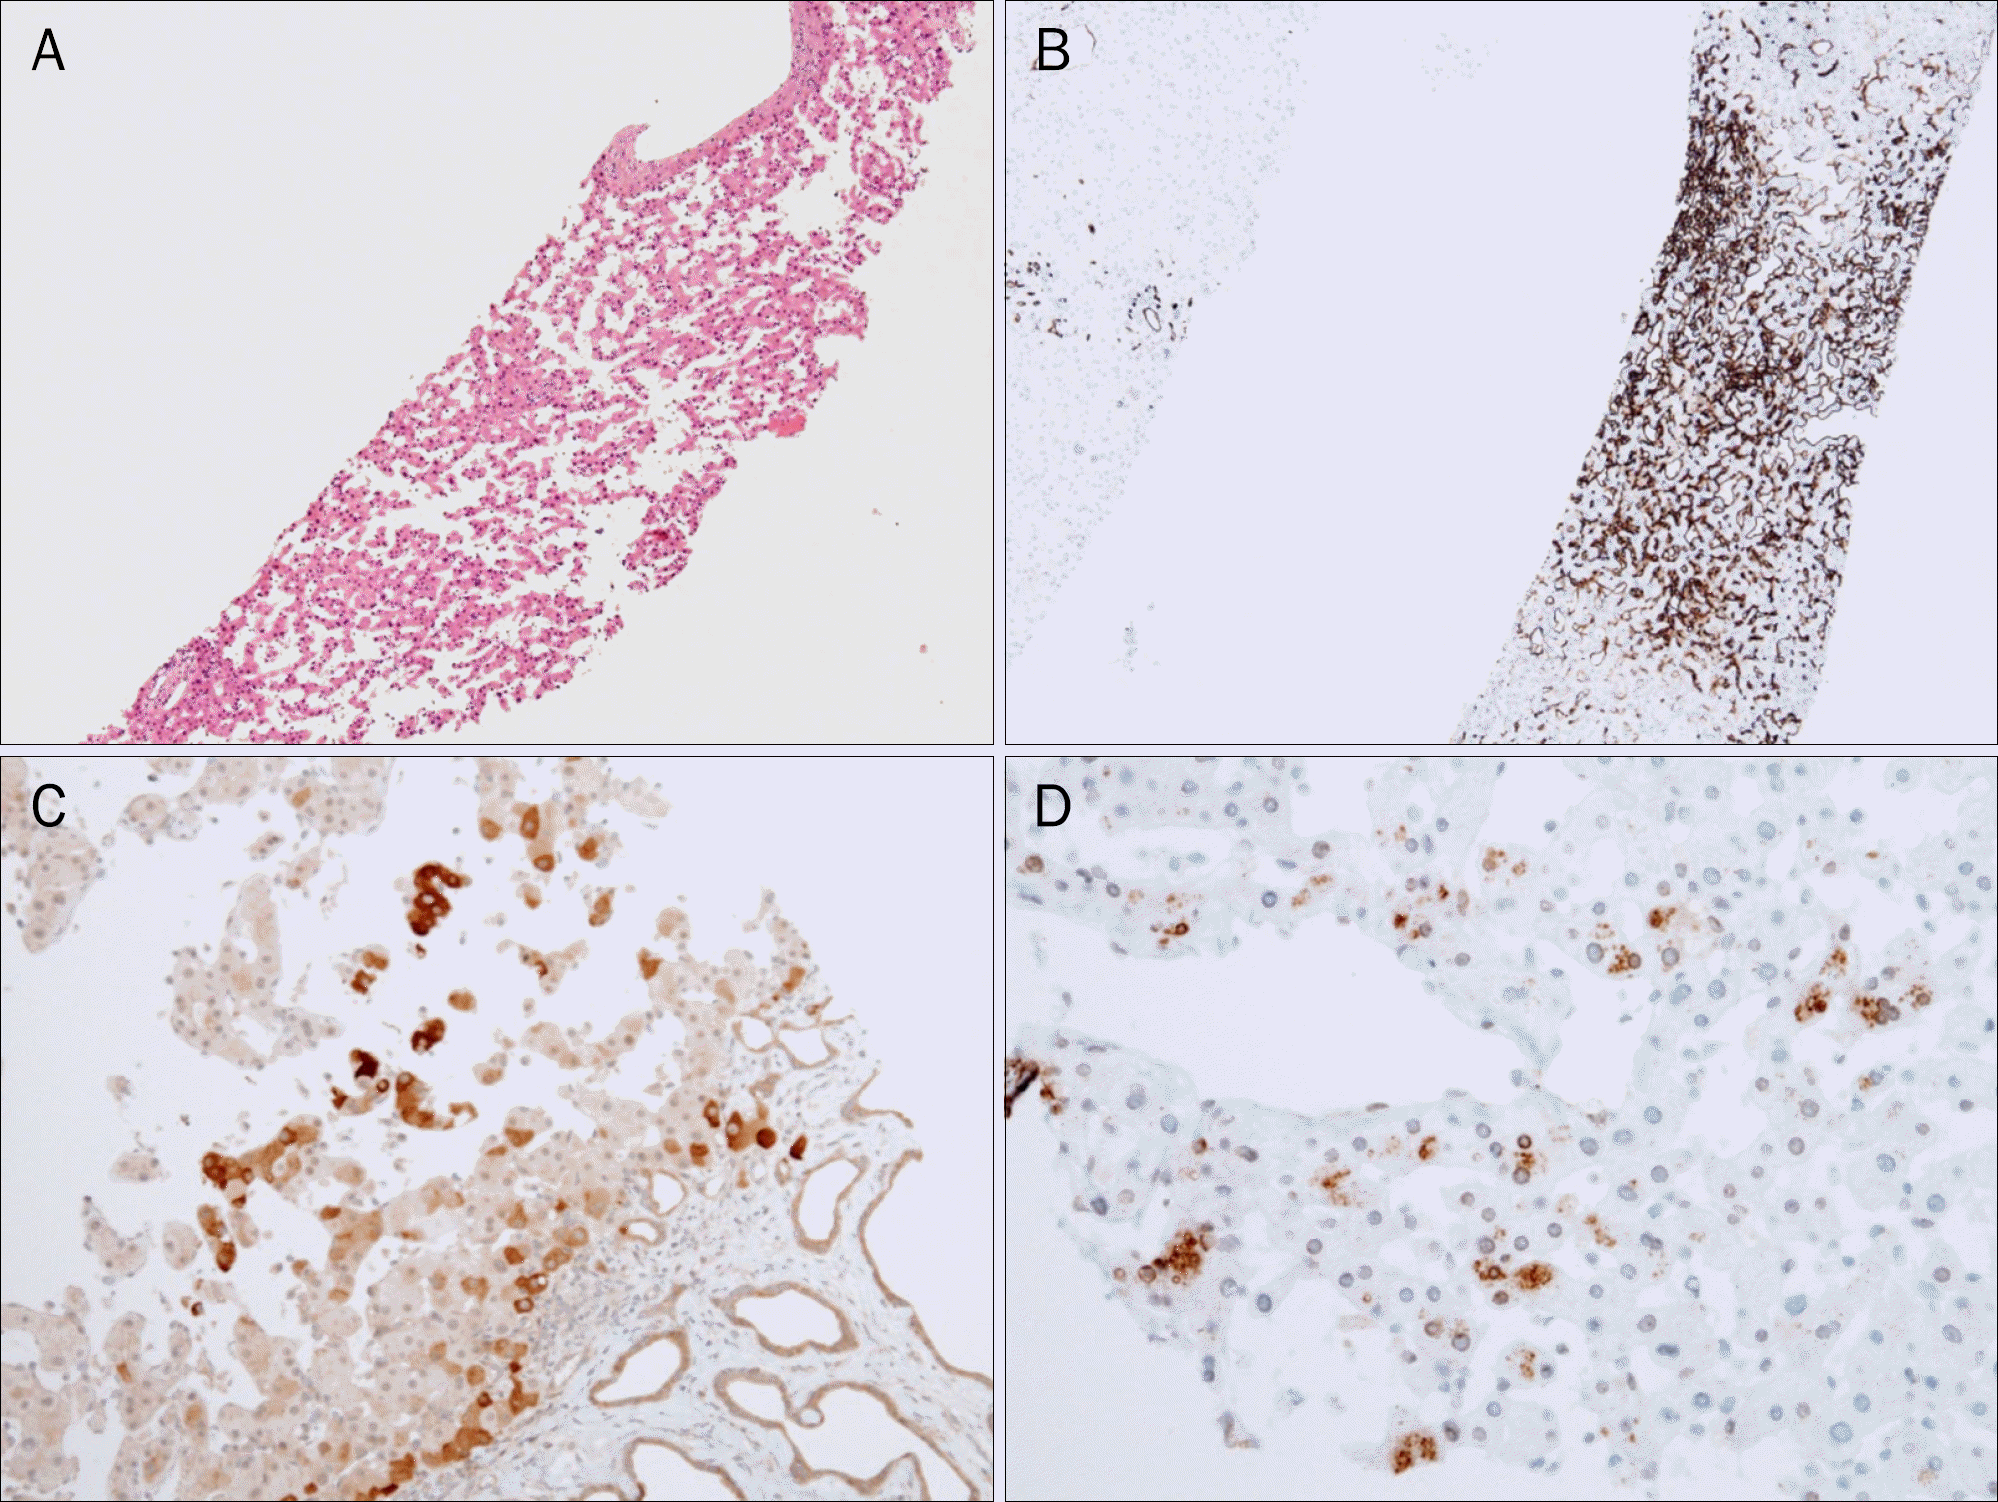
Fig. 5.
Pathologic findings of a follow-up biopsy specimen. (A) Similar to that of the initial biopsy findings, sinusoidal dilatation and sinusoidal capillarization are noted (H&E stain, ×40). Sinusoidal capillarization (B; CD34 stain, ×40), CRP (C; CRP stain, ×100), amyloid (D; amyloid A stain,×200) are positive in the tumor cells.
 XML Download