



 PDF
 ePub
 Citation
 Print


Abstract
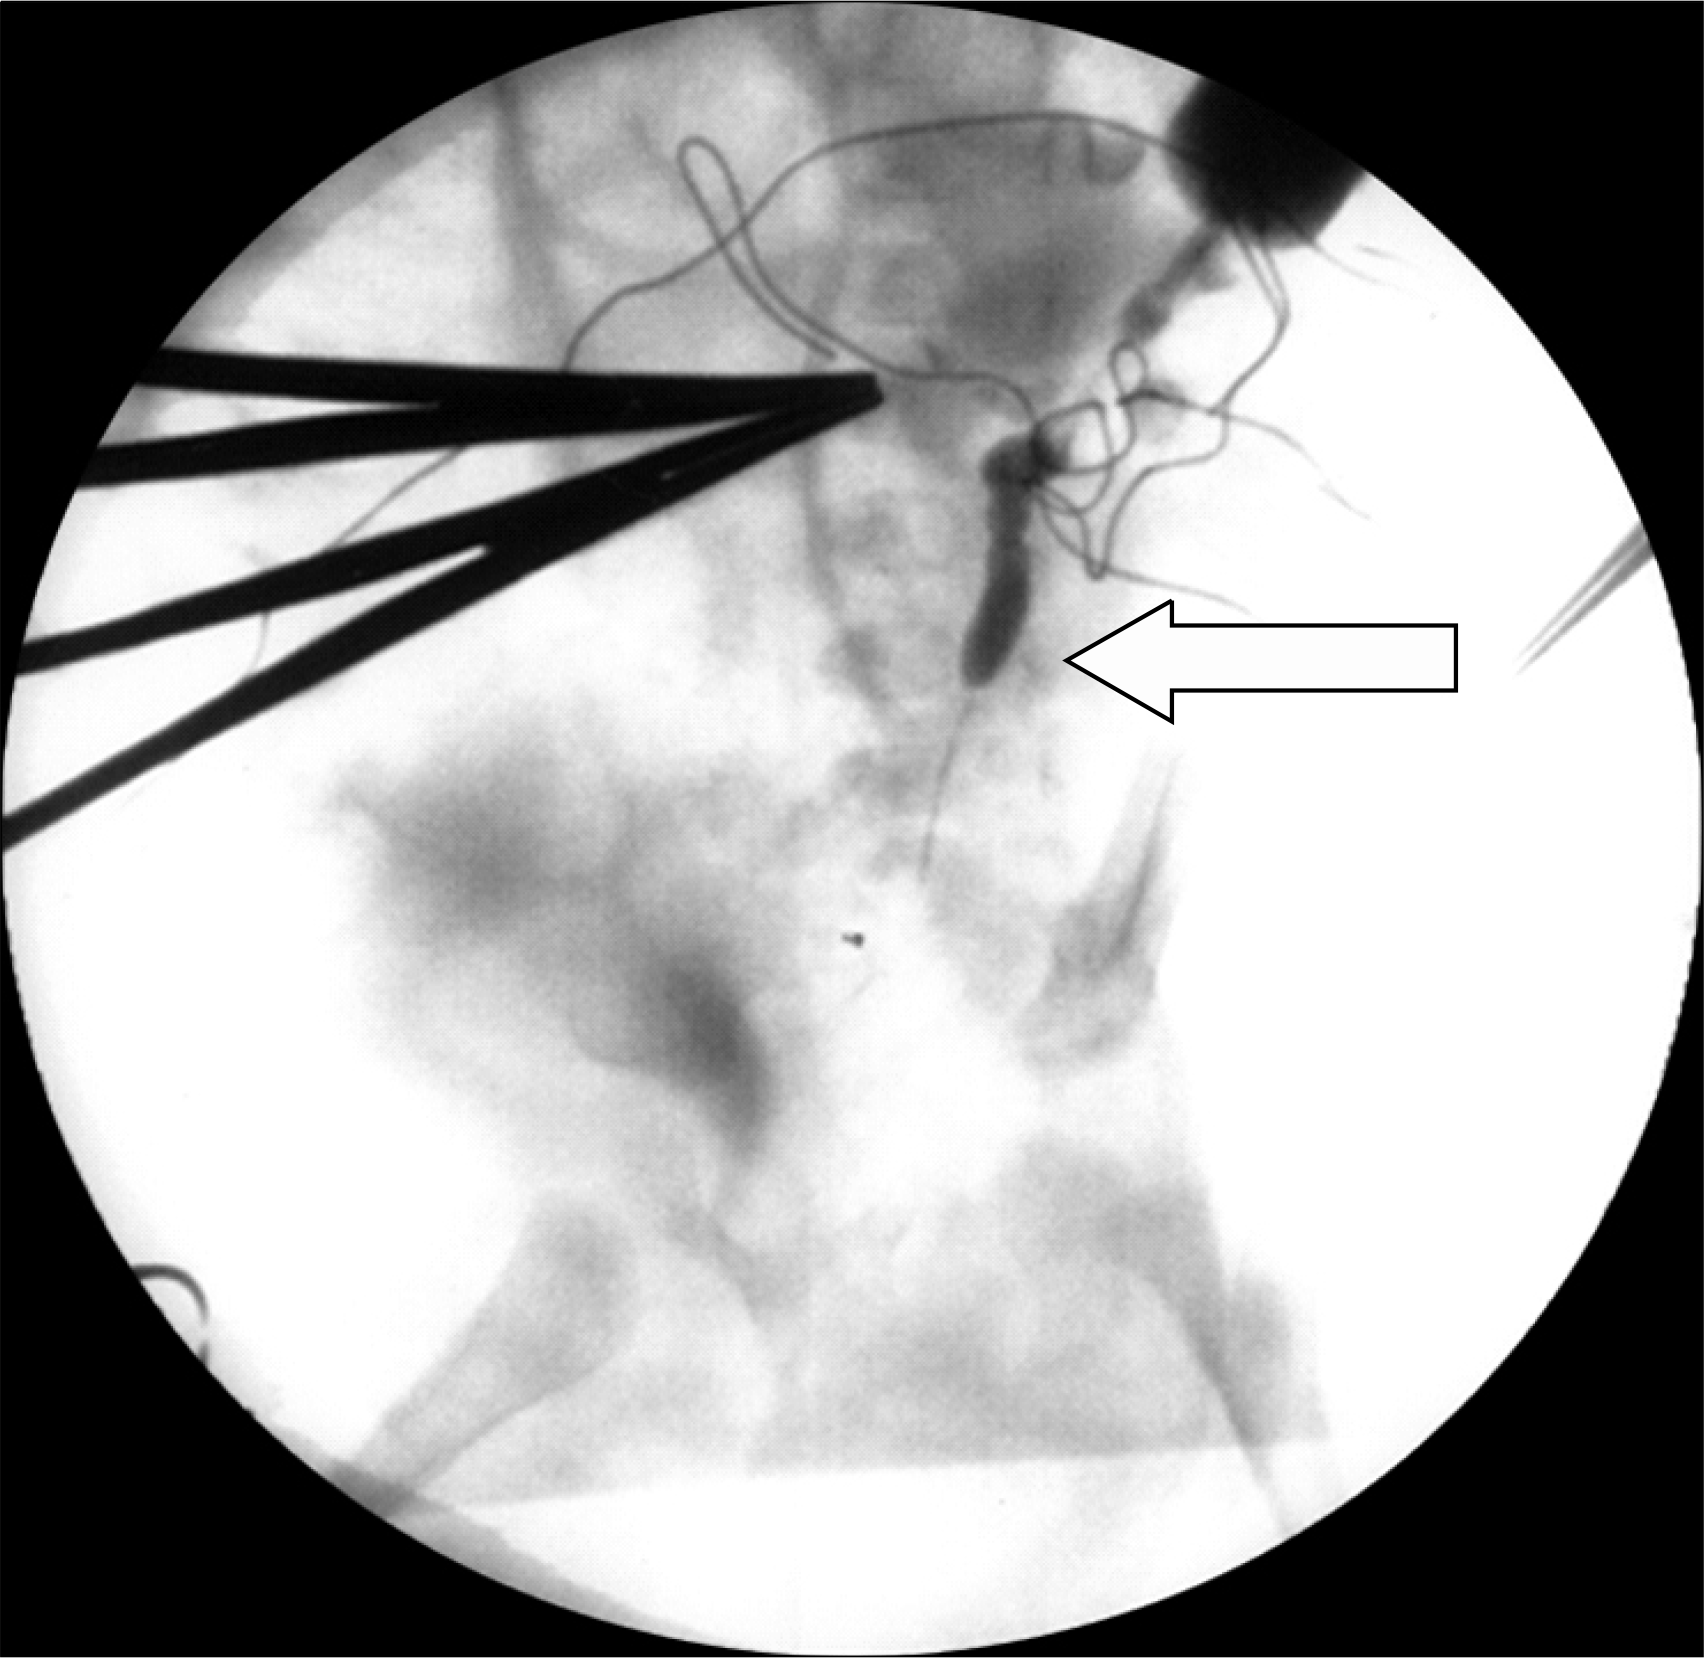
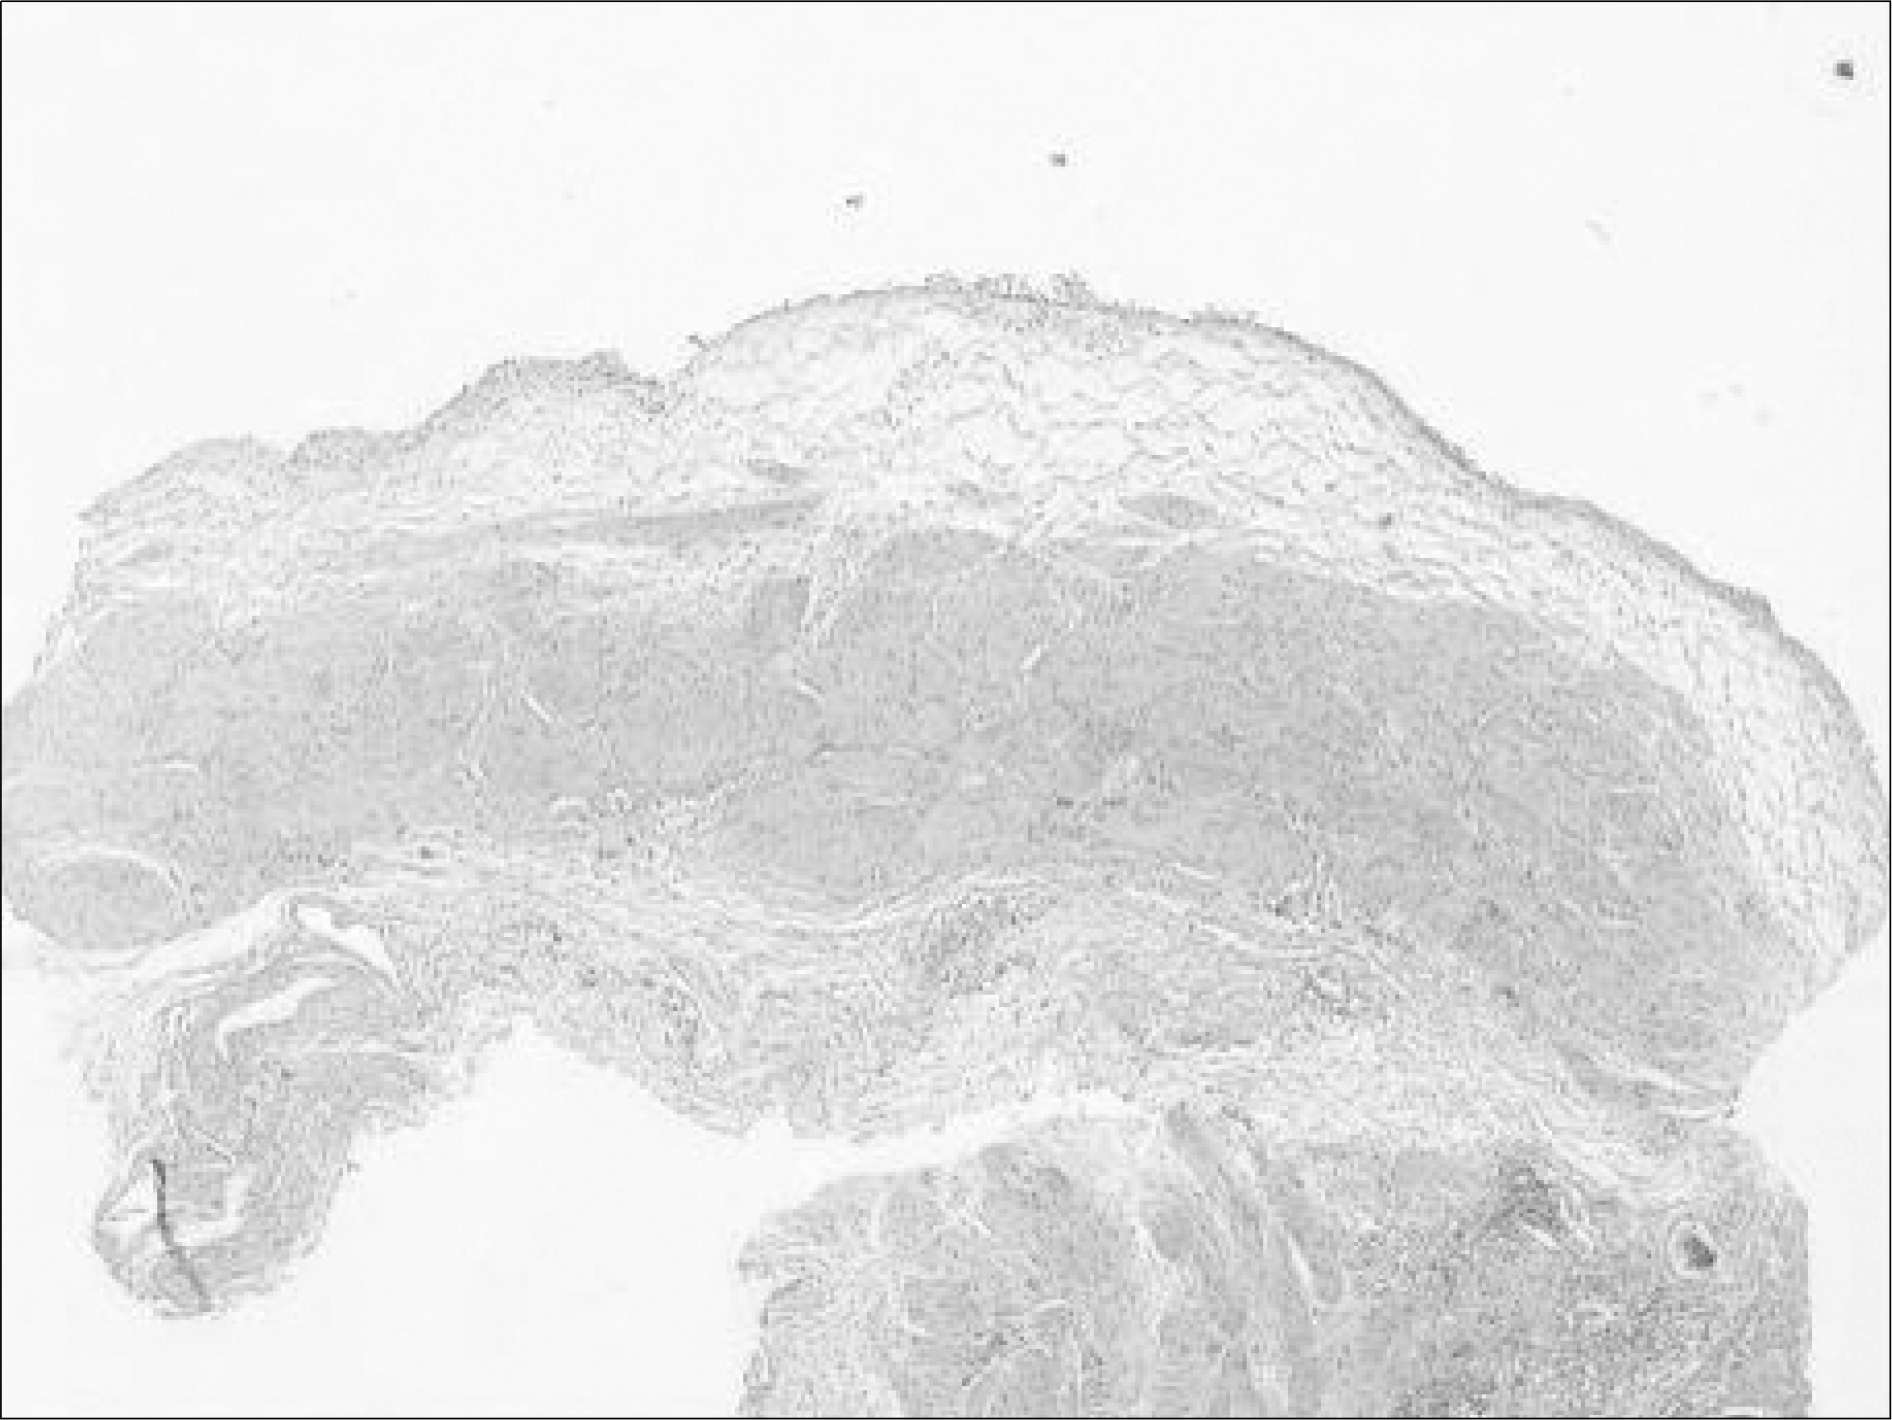
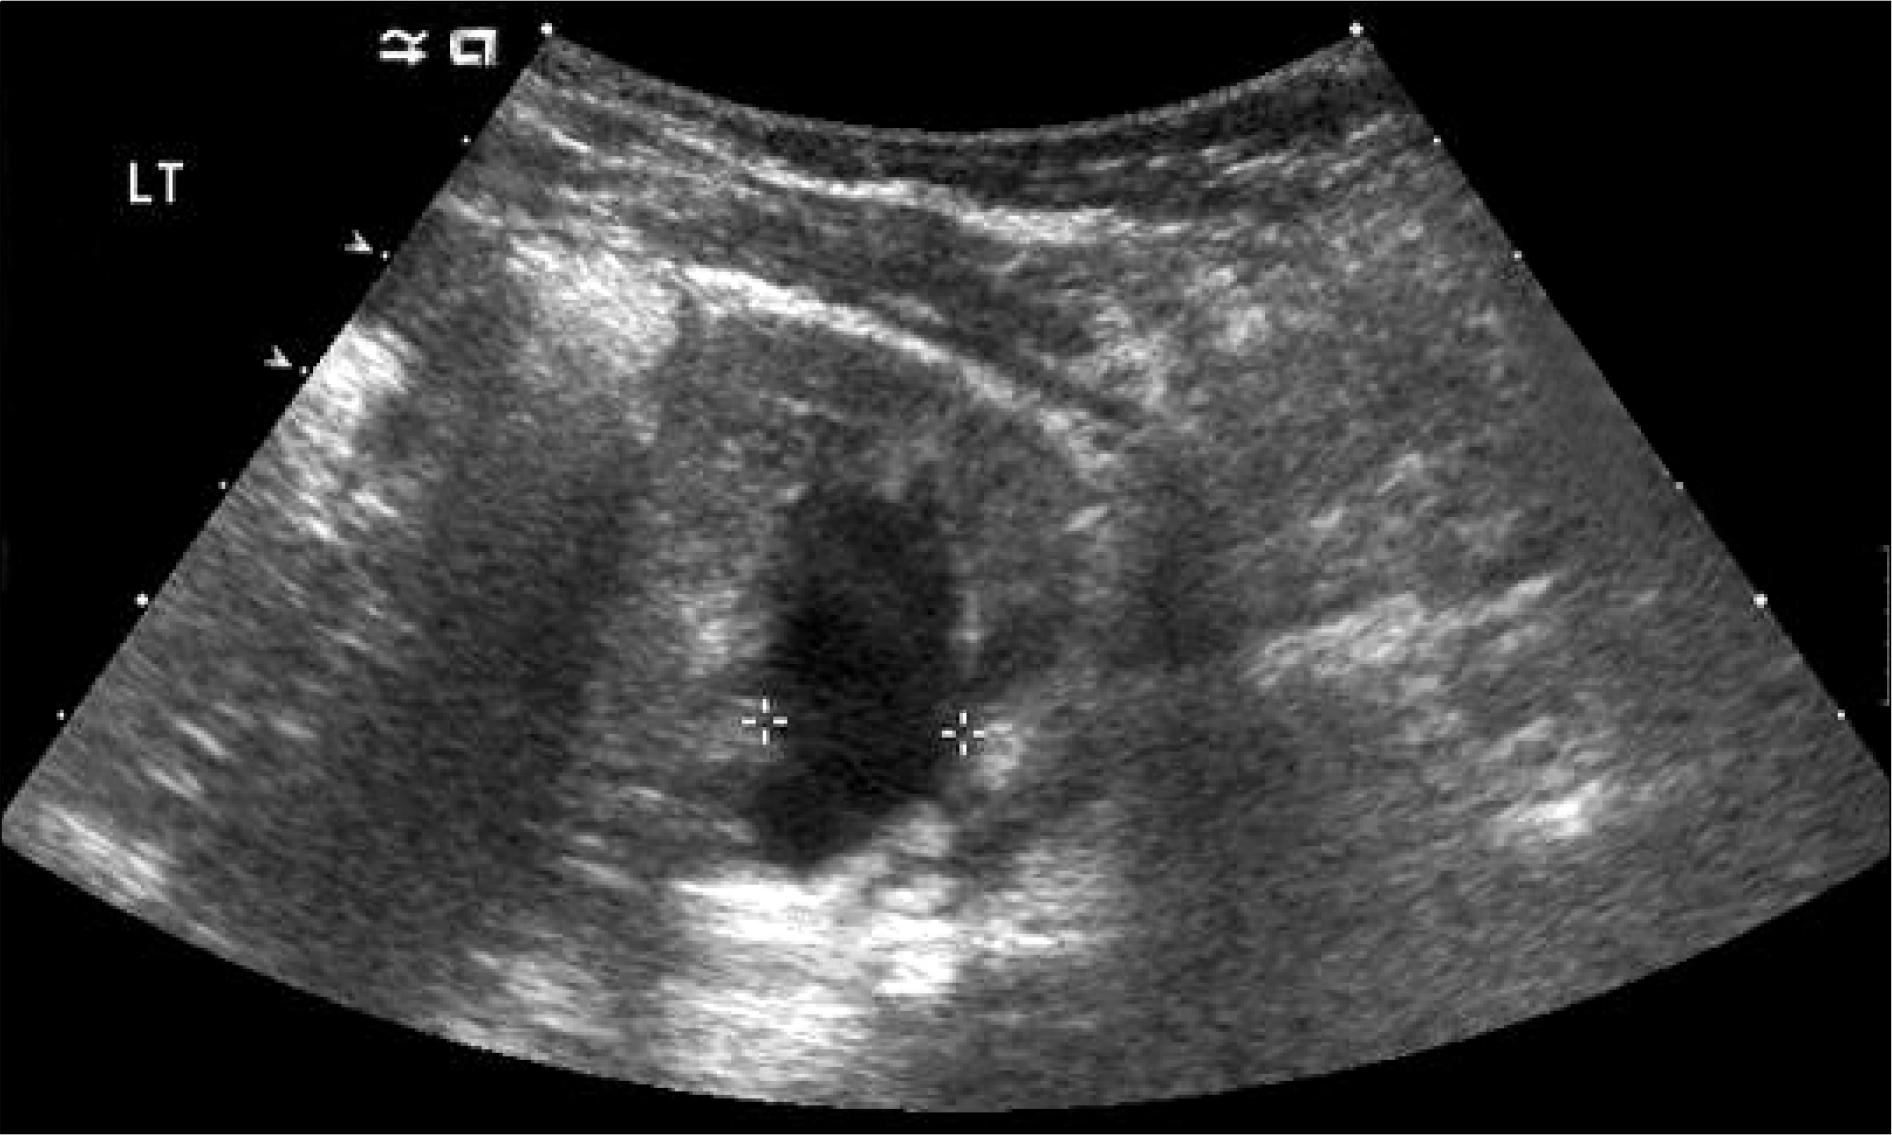
Hydronephrosis is the most common abnormal finding of genitourinary tract detected by fetal ultrasonography. The causes of majority are attributed to ureteropelvic junction (UPJ) obstruction. The remaining are secondary to vesicoureteral reflux, megaureter, or posterior urethral valves. Congenital midureteral stricture is an unusual cause of hydronephrosis. We report a case in a one month old male baby with hydronephrosis (grade V, 20mm in AP diameter). He was diagnosed as a ureteropelvic junction obstruction. A mid ureteral stricture was identified with intraoperative anterograde pyelography. After removal of severely strictured ureter, the dilated proximal end was anastomosed to the spatulated distal ureter by microscope. Pathologic finding was subepithelial fibrosis and segmental inner smooth muscle attenuation. Ureteral stent was removed 2 months after surgery. Degree of hydronephrosis was markedly reduced on the follow up ultrasonography (14mm in AP diameter) 6 months after surgery.
REFERENCES
1. Hwang AH, McAleer IM, Shapiro E, Miller OF, Krous HF, Kaplan GW. Congenital mid ureteral stricture. J Urol. 2005; 174:1999–2002.
2. Brugnara M, Cecchetto M, Manfredi R, Zuffante M, Fanos V, Pietrobelli A, et al. Prenatal diagnosis of a rare form of congenital midureteral stricture: a case of report and literature revisited. BMC Urol. 2007; 7:8.

3. Miyakawa A, Baba S, Tazaki H. Congenital ureteral valves: report of 2 cases. Hinyokika Kiyo. 1994; 40:65–9.
4. Prieto JC, Castellan M, Gosalbez R, Labbie A, Perez-Brayfield M. Severe congenital midureteral dilatation. J Pediatr Surg. 2007; 42:257–8.
5. Campbell MF. Clinical considerations of the anatomy, physiology, embryology, and anomalies of the urogenital tract. Pediatric urology. New York: MacMillan Co.;1937. p. 188. 273, 287-9.
6. Kim EK, Song TB. A study on fetal urinary tract anomaly: antenatal ultrasonographic diagnosis and postnatal follow-up. J Obstet Gynaecol Res. 1996; 22:569–73.
7. Wall B, Wachter E. Congenital ureteral valve: its role as a primary obstructive lesion: classification of the literature and report of an authentic case. J Urol. 1952; 68:684–90.
8. Rabinowitz R, Kingston TE, Wesselhoeft C, Caldamone AA. Ureteral valves in children. Urology. 1998; 51(5A Suppl):7–11.
9. Docimo SG, Lebowitz RL, Retik AB, Colodny AH, Bauer SB, Mandell J. Congenital midureteral obstruction. Urol Radiol. 1989; 11:156–60.
10. Smith BG, Metwalli AR, Leach L, Cheng FY, Kropp BP. Congenital midureteral stricture in children diagnosed with antenatal hydronephrosis. J Urol. 2004; 64:1014–9.
Fig. 1.
Preoperative renal ultrasonography. Severe hydronephrosis is noted in the left kidney, measuring 20mm in AP diameter.
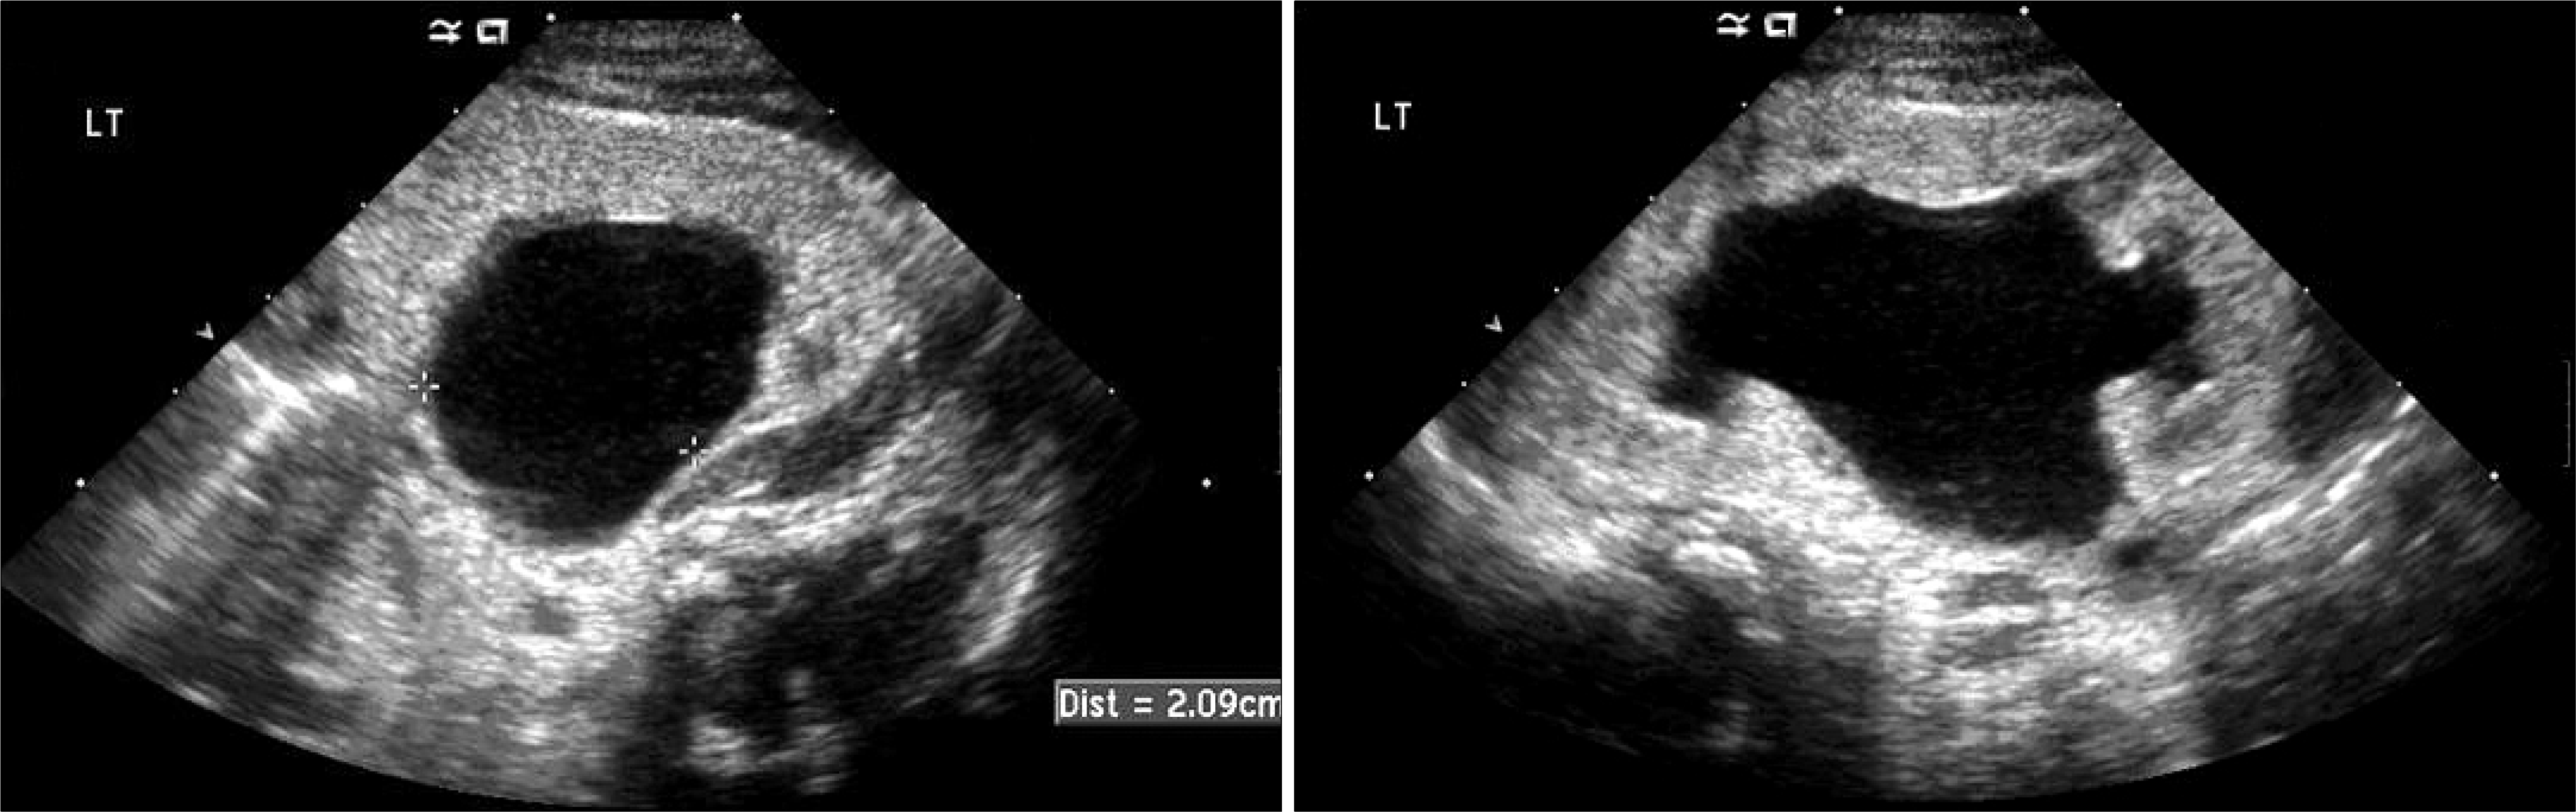
Fig. 2.
Preoperative diuretic renogram. Severe hydronephrosis of left kidney with poor reaction to diuretics.

 XML Download